Wednesday, October 23, 2013

Obamacare 2016: Happy Yet?

From Bradley Allen, MD in the opinion section of the Wall Street Journal this morning:
"The forecast shortage of doctors has become a real problem. It started in 2014 when the ACA cut $716 billion from Medicare to accommodate 30 million newly "insured" people through an expansion of Medicaid. More important, the predicted shortage of 42,000 primary-care physicians and that of specialists (such as heart surgeons) was vastly underestimated. It didn't take into account the ACA's effect on doctors retiring early, refusing new patients or going into concierge medicine. These estimates also ignored the millions of immigrants who would be seeking a physician after having been granted legal status.

It is surprising that the doctor shortage was not better anticipated: After all, when Massachusetts mandated health insurance in 2006, the wait to see a physician in some specialties increased considerably, the shortage of primary-care physicians escalated and more doctors stopped accepting new patients. In 2013, the Massachusetts Medical Society noted waiting times from 50 days to 128 days in some areas for new patients to see an internist, for instance.

But doctor shortages are only the beginning.

Even before the ACA cut $716 billion from its budget, Medicare only reimbursed hospitals and doctors for 70%-85% of their costs. Once this cut further reduced reimbursements, and the ACA added stacks of paperwork, more doctors refused to accept Medicare: It just didn't cover expenses.

Then there is the ACA's Medicare (government) board that dictates and rations care, and the board has begun to cut reimbursements. Some physicians now refuse even to take patients over 50 years old, not wanting to be burdened with them when they reach Medicare age. Seniors aren't happy."

Medicaid in 2016 has similar problems. A third of physicians refused to accept new Medicaid patients in 2013, and with Medicaid's expansion and government cuts, the numbers of doctors who don't take Medicaid skyrocketed. The uninsured poor now have insurance, but they can't find a doctor, so essentially the ACA was of no help.

The loss of private practice is another big problem. Because of regulations and other government disincentives to self employment, doctors began working for hospitals in the early 2000s, leaving less than half in private practice by 2013. The ACA rapidly accelerated this trend, so that now very few private practices remain."
Read the whole thing (subscription required, sorry).  Not surprisingly, it's not pretty.

-Wes

Saturday, October 19, 2013

Back to One

It was a comment posted by "Cat, MD" on my prior post regarding my assessment of where the nation stood "week two" following the launch of the government's health insurance exchange website that caught my eye. To me, she(?) asked what might be the one of the more important questions posed on this blog that warrants consideration by every medical student and practicing doctor currently:
Dr. Wes,

You state that law and medicine do not mix, but it seems as if medical care will be driven by national politics for the indefinite future. The ACA and laws like it will directly affect how physicians can practice.

So what role should physicians try to play in this? The prospect of letting attorneys and accountants dictate medical practice unnerves me. But at the same time, few people go to medical school to become politicians. As a medical student, I feel that physicians need to be more involved in legislating, but how?
Perhaps this would be as good a time as any to step back and contemplate this incredibly challenging question. After all, more and more difficulties with our new law are appearing as its real nuts and bolts are revealed. Yet it is always easy to criticize the myriad of events that are unfolding: the botched Healthcare.gov website, the creation of new donut holes of health care coverage, or the real life problems with the restrictive health care system model we're creating. What can doctors possibly do to help resolve these challenges?

Like a difficult case that stumps the best of doctors, perhaps doctors should go back to one.

The idea is not mine but that of the late psychologist and disruptive thinker, Sheldon B. Kopp. When a doctor has a difficult case sitting before them and they have run out of ideas about how to help that patient, he recommends the doctor go back to one. What do you know how to do well? What can you contribute to this patient. What have you tried that did not work?

Back to one.

From Dr. Kopp's book, "If You Meet the Buddha on the Road, Kill Him: The Pilgrimage Of Psychotherapy Patients:"
“Crises marked by anxiety, doubt, and despair have always been those periods of personal unrest that occur at the times when a man is sufficiently unsettled to have an opportunity for personal growth. We must always see our own feelings of uneasiness as being our chance for "making the growth choice rather than the fear choice.”
We have tried Red and Blue solutions for health care reform and should be asking ourselves how they are working out. What has worked? What hasn't? What can each of us bring to the health care table? What needs to be done? Is a centralized control of health care our best solution, or might there be something else?

Of course, none of this is easy. It is not easy to take risks. It is not easy to think we might not just be able to sit back and ignore the difficulties that arise when biased third-parties control the show. But when we begin by going back to one, there is an opportunity for meaningful change that benefits doctors and patients alike.

For today's doctors, Dr. Kopp offers a useful visual:
“There is the image of the man who imagines himself to be a prisoner in a cell. He stands at one end of this small, dark, barren room, on his toes, with arms stretched upward, hands grasping for support onto a small, barred window, the room's only apparent source of light. If he holds on tight, straining toward the window, turning his head just so, he can see a bit of bright sunlight barely visible between the uppermost bars. This light is his only hope. He will not risk losing it. And so he continues to staring toward that bit of light, holding tightly to the bars. So committed is his effort not to lose sight of that glimmer of life-giving light, that it never occurs to him to let go and explore the darkness of the rest of the cell. So it is that he never discovers that the door at the other end of the cell is open, that he is free. He has always been free to walk out into the brightness of the day, if only he would let go. (192)”
If only we would let go.

To start, I believe there are a few prerequisites young and older doctors alike from either side of the political aisle should consider to help bring meaningful change to the health care reform discussion:

Be a Good Doctor: Nothing will improve your credibility as a spokesperson on behalf of your patients if you keep their interests first. This whole reform efforts is, after all, about them.

Get Involved: If you don't vote, you can't complain about who is elected. In the same way, if you don't get involved in voicing your concerns (and this is important) attempting to offer new, helpful solutions to problems faced by your patients, how will things ever improve for them?

Connect: None of us are politicians. None of us are lawyers (well, a few might hold dual degrees...). But doctors should be asking themselves, how have the politicians handled things to date? Maybe it's time to rethink our strategy for reform. Maybe Washington's solutions aren't our patient's best solutions. But is there a different way, an alternate strategy?

The vast majority of doctors are on the front line of caring for patients. Most are incredibly busy. And the majority are a devoted bunch with authority when it comes to patient care (believe it or not). We can offer solutions. Some are likely to fall on deaf ears, but some may not. But if we don't speak up and consistently advocate for our patients' medical needs over basic or mandated business concerns, our patients will suffer and we will be sidelined.

Some have suggested that social media might be a place where doctors' voices can be heard. Perhaps. But while doctors can voice our thoughts and ideas on social media, I am increasingly convinced that this is not where real change will occur. We need to bring our thoughts and ideas back home to our communities. Doctors need to take back medicine by going back to one and dig deep to offer small solutions one at a time locally, at home, not on some large bureaucratic national stage that is driven by special interests.

Cat, MD's question is the nugget: "... but how?" "Back to One" is just one idea. There are others. But maybe the best way to start changing health care for the better is to start asking the right questions and offering our own solutions for ourselves and our patients.

-Wes

Friday, October 18, 2013

Saying Goodbye to Drug Samples

Soon, doctors won't be handing patients drug samples from time to time, pharmacists will.  

Doctors were told that makes a difference.  It will soon be a national trend, they were told.  Instead of handing a patient a sample, just type in an order for a sample to the EMR and the pharmacist will make sure they get it.

Doctors were told that the Joint Commission has certain standards that must be met by health care organizations and hospitals when drug samples are given to patients.  After all, doctors were told by at least one of their own that drug company representatives bias the way doctors think and prescribe.  Doctors must also disclose gifts they receive from drug companies that exceed $10, according to the recently activated Physician Payment Sunshine Act.  Doctors were told drug samples might qualify as gifts.  It just looks bad, they were told.

Doctors were not told that their hospital system runs the pharmacy now.

Think about that.  Think about the unintended consequence when yet another small, kind, visible gesture that a doctor can make to his patient is yanked from his control.  Think about the fact that decreasing pharmaceutical sales representatives might decrease pharmaceutical sales of more expensive medications, but might also have the unintended consequence of decreasing access to new and important information to physicians and as one study pointed out, result in doctors who didn't see drug representatives prescribing less effective and potentially more dangerous drugs to their patients longer than those who do.

But at least the sample order will be there in the electronic medical record to track.  Hospitals will be in regulatory compliance and pass their Joint Commission inspections with flying colors.  And no doubt the pharmacist will do a better job of teaching patients at the drug counter when people are lined up in public four-deep to get their prescriptions. Surely the hospital's pharmacist will be completely aware of the patient's entire medical history and offer the correct number of tracked sample medications without any conflict of interest involved.   

And doctors will sleep better at night knowing their physician payment database record remains unblemished.

Yeah, no worries.  None all all.  It's all for the better good.

Really.

-Wes

Thursday, October 17, 2013

Accountable Care Act Week Two: An Honest Assessment, Part II

Bob Doherty, MD gives his assessment of the Accountable Care Act's second week over at the American College of Physician's blog today. It's a worthwhile read and I encourage my of my three readers to head over there to see what he has to say. Remarkably, I agree with some of his assessment, especially his perspective that the miserable launch of the ACA's healthcare.gov website is not a reason to call the law a complete "failure."

But as things would have it, the ACP blog does not permit the "html" tag in his blog comments (I understand why: it helps limit blog spam), but I wanted to reference a few important links so I'm placing my different "honest" assessment of our law's second week here. So Bob, please excuse my comment being left here.
Bob -

Politics and medicine don't mix, yet today the two combined are our reality. As such, a brief comment about your post.

First on what we agree upon: tech problems on healthcare.gov are not a reason to declare the ACA a “failure.” No doubt the day will come after they pour in many tens of millions of dollars more to fix the website that things will be humming along famously one day.

But many are aware that the ACA as it was written is no longer the ACA, so as such, it has failed before it's website was launched. But if we ignore this fact, the ACA now is a patchwork of political favors and waivers that favors the politically connected and architects of the law and it is likely to continue to be such. We are also finding that the law is very expensive for many Americans, yet does little to address the expanding cost burdens that health care imposes on America’s economy, especially when one evaluates the law on the basis of health care cost sustainability. To me, this is the ACA’s Achilles’ heel and why it will ultimately be morphed into yet another "law," not because of some poorly-designed website. You see, it is anything but “Affordable” and even more importantly, certainly not “sustainable.” But we should acknowledge that for many Americans saddled with the prospect of bankrupsy from burgeoning health care costs, the law will offer relief and this is a good thing.

Still, after the debut of the exchanges 1 October 2013, out-of-pocket costs of the new health care “plans” put forth by the insurance industry became known and were nicely outlined by Peter Frost in the Chicago Tribune recently. People will soon be feeling the effects of these additional costs first-hand that have been created in large part by the regulatory requirements of the law and its giant bureaucratic overhead. In fact, I have already begun hearing from patients that the deductibles for many of them are so high that many are worried they won’t meet their deductibles in an average health care year before the next year arrives. So what have they gained from this law, just a sense of altruism for their fellow man?

Personally, I think this is why the ACA as it exists will fail: Americans’ realized out-of-pocket health care costs. And when it does, Big Box medicine will have to accommodate new, innovative health care payment strategies that actually create visible value to those who pay into the system, rather than just guaranteeing the rising stock price of insurance and pharmaceutical companies.

But physicians like us are also to blame for the law’s ultimate failure. Caught between the law’s political promise of "health care coverage for all" now, versus creating more sustainable health care delivery system for the long run, our political lobbying groups (the AMA, ACP, ACC and others) sided with the political expediency of approving the law’s construct as it was presented. And so now, we have no choice but to continue to ride along on our newly revised Healthcare Hindenburg whether doctors really like it or not.

Just my two cents.
-Wes

Monday, October 14, 2013

Sid Says Goodbye

Sid Schwab, MD, a surgeon with a remarkable skill as a writer and long-time author of Surgeonsblog (a favorite of mine in my early years as a blogger) says goodbye to the blog-o-sphere in true Sid-style.

-Wes

Thursday, October 10, 2013

You Can't Say You Weren't Warned

He looked ahead, seeing his feet on the hearth. There was smoke rising from one of the three logs, and he marveled at the small flicker of flame that stretched up and ignited the smoke that swirled above the log, dancing briefly somewhat joyously, then gone again, smoke returning.

 "You can't say you weren't warned," she said.

He sat, reflecting on her words. So much years of work, so much effort, breadwinner, worker, eager participant in so many others' life-and-death moments. That was his job, right?  It was his aphrodisiac, his salve, his calling for so long. Always being there for others, on call with pager on, nurses and Emergency Rooms calling.  But now, after the sun has long set in a quiet house with his wife and blind, loving cocker spaniel next to him, he reflected: "Where did the time go?"

"You can't say you weren't warned."

With that, the door opened.  The young man entered, unshaven, hurried and preoccupied, but seemed happy.  So much was happening, albeit it was his own separate calling, full of its own challenges and pressures.  He sprung to his feet to greet the young man, remembering when he had been in a similar place at a much earlier time: anxious, uncertain, excited, like when he directed his the first real code - so much responsibility.

 "Happy birthday, Dad," the young man said.

They hugged, shared a story together, then a piece of cake. Before he knew it, "I wish I could stay longer, but I have to go.  I've still got a ton to do."

"I understand. You'll do fine. Thanks for coming over.  Good luck."  And after grabbing the remaining piece of cake to bring to his roommate, the young man left as quickly as he had come.  His wife, exhausted after a long day herself, headed to bed and left him to close up for the night.

He went to the front door, placed his hand on the lock and stood for a moment.  The porch light shone dimly on the front walkway as it had done for so many years, a guide for the inevitable late night arrival that would always enter later.

Until now.

The house stood eerily silent, a stark reminder of all that has happened while he was busy doing other things.  He turned the lock, switched off the unnecessary porch light, then headed to bed as her words echoed:

"You can't say you weren't warned."

-Wes


Daily Caller: 800 Number for HealthCare.gov - An Accident?

You can't make this stuff up: look what the 800 number for Heathcare.gov's information hotline spells. Goodness!

This can't be an accident. After all, it shows what can be found when you actually read the keypad...

-Wes

Wednesday, October 09, 2013

Case Study: A Case of Recurrent Ventricular Tachycardia

The following is a case study intended for folks who look at defibrillator recordings.  If you find it interesting, great.  If you have no clue what is shown here, don't feel bad, just move on to another blog post.  I just thought I'd put this up as an unknown for those interested in phenomena encountered in a busy device clinic.
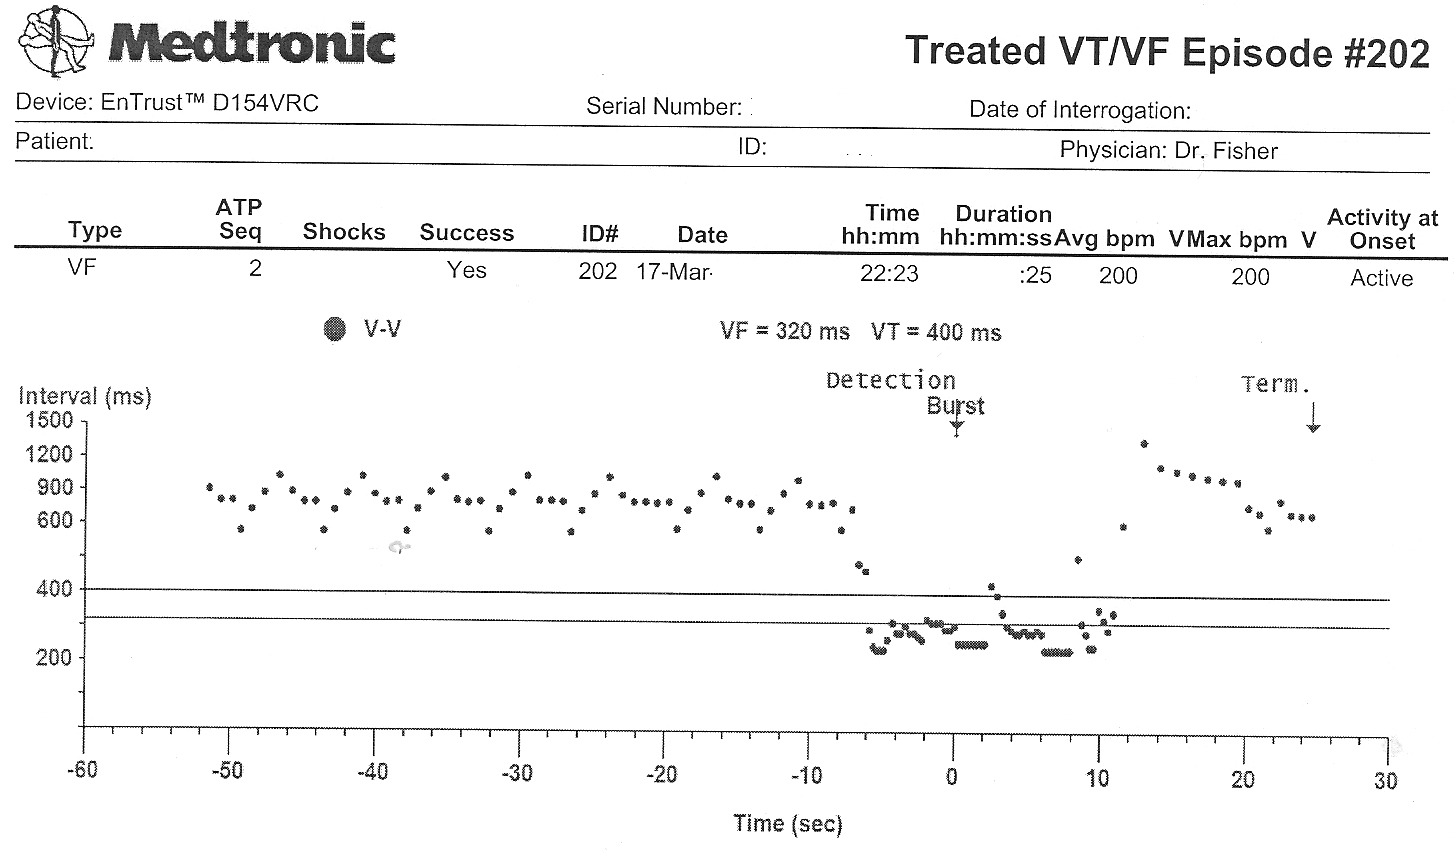
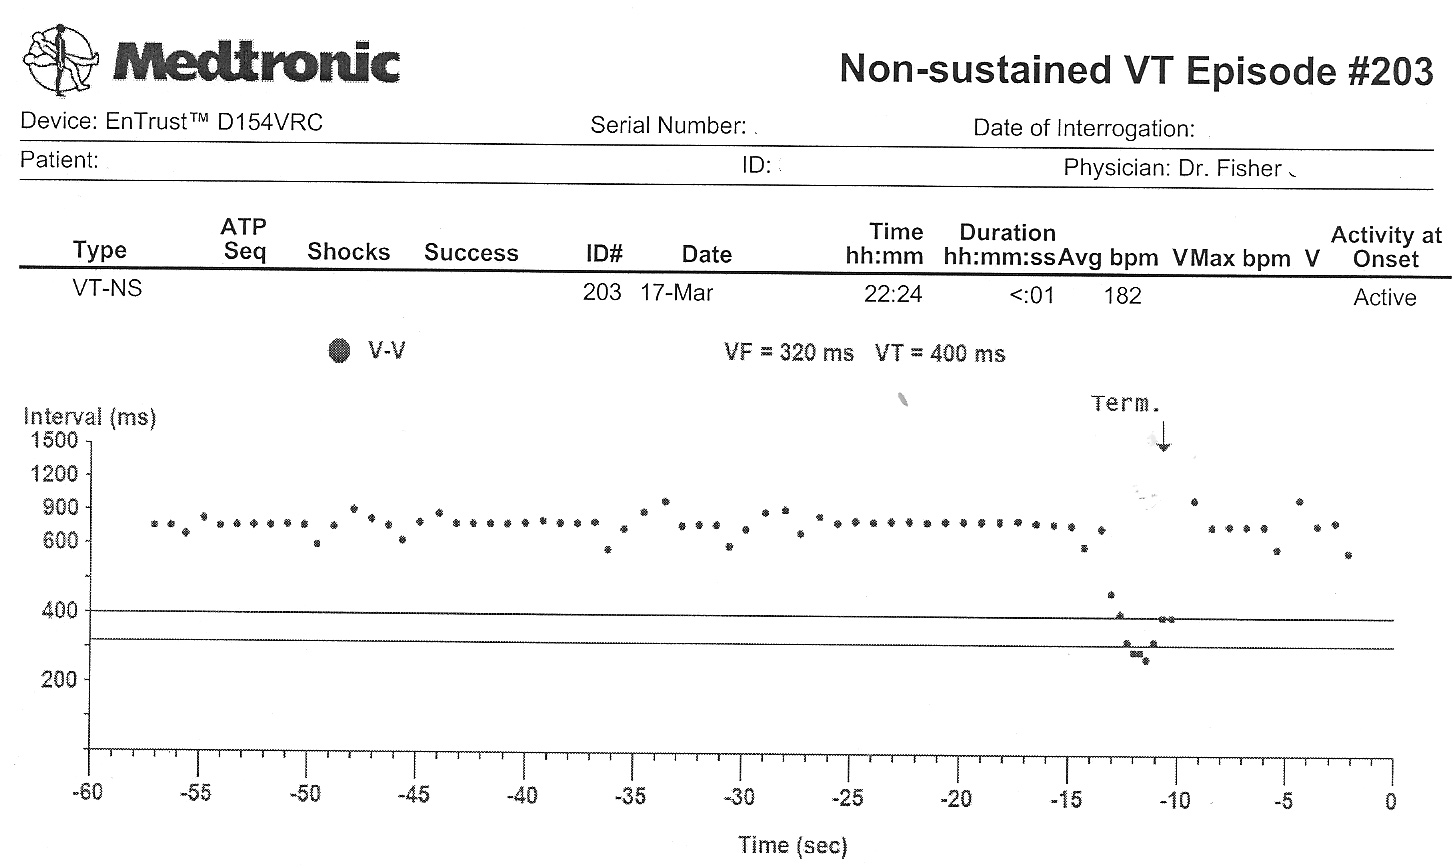
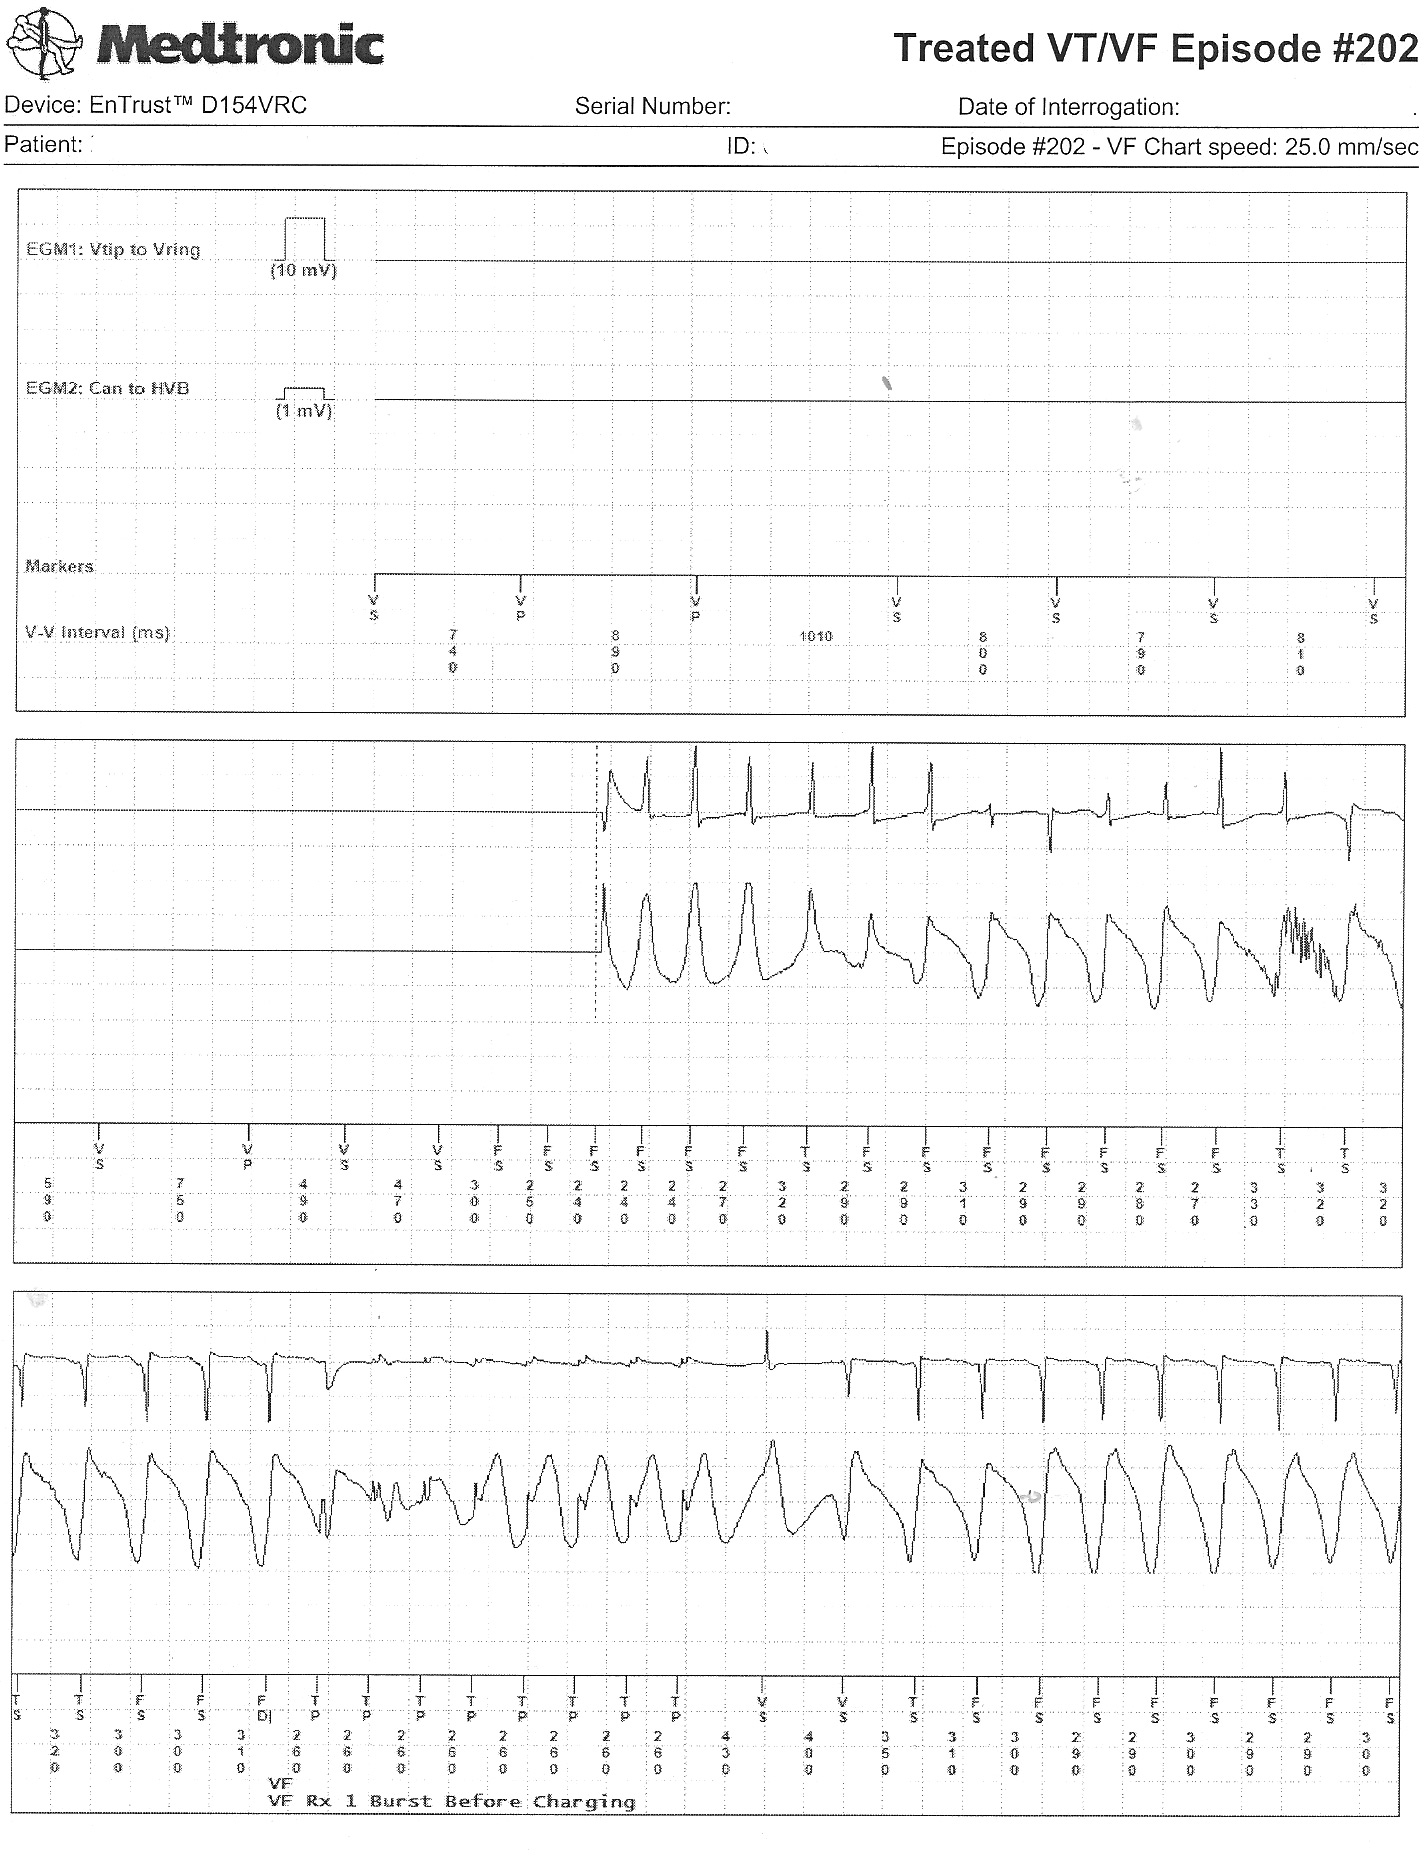
It was a case seen in our clinic: a nice man in his 50's had received a single chamber ICD for recurrent ventricular tachycardia and ventricular fibrillation and called because he had received several shocks from this device.  Interrogation of the device showed normal sensing, lead impedance and capture threshold.  Interrogation of his device demonstrated multiple VT therapies and untreated events recorded by his device. 

An example of several of the recorded interval plots (Event 202 and 203) as well has one example of the electrograms (and therapies delivered) recorded during episode 202 are shown below.  56 similar events were recorded since his last device interrogation, all with a similar pattern:


Episode 202 RR Interval Plot (Click to enlarge) 
Event 203 RR Interval Plot

Event 202's Recorded Electrograms and Intervals (Click image to enlarge)
 
Any thoughts about why this man might be having VT?

-Wes

Tuesday, October 08, 2013

What Board Recertification Is Failing to Teach Doctors

I continue to study for my third ABIM re-certifications in both cardiovascular disease and cardiac electrophysiology. In preparation for the examinations, I purchased the review materials offered by the American College of Cardiology called ACCSAP-8 and took the surprisingly expensive Cardiac Electrophysiology Board Review course held in Chicago recently. I find I have little time to study all of this material while delivering patient care, so I've been getting up at 4:30-5:00 am each day when by brain is rested to review the material. Needless to say, the material is so plentiful and dense that I feel like I'm reading through the Encyclopedia Britanica.

After studying for these boards for the third time, I have come to the realization that there's a million ways the ABIM could write test questions to pimp those of us required to re-take these exams. I can only hope that the few items I've learned as a consequence of answering the accompanying questions at the end of each section of the materials gets me by in a test whose curve is set by some statistical method that no one really understands. But what if I don't pass, God forbid? What would it mean for me professionally? While doctors are reassurred they can re-take the examination (for a fee, of course), does the ABIM's "scarlet letter" affect my ability to practice medicine? Should doctors be educated on the implications of non-certification and what it might mean to a doctor professionally rather than just touting the benefits of this process? Since the implications of not passing re-certification boards may have large financial and emotional implications to physicians, what ethical and legal responsibility does the ABIM and American Board of Medical Specialties hold to their members? I really don't know.

But my point in this post is not to re-hash my concerns about the non-objective and money-making nature of this recertification process, but rather to identify other problematic areas that the ABIM and professional societies like the American College of Cardiology and Heart Rhythm Society are missing in this re-certification process.

First of all, cardiology practice has changed. Cardiology specialists and subspecialists are now increasingly employees of huge health care systems as a result of the health care reform efforts underway. Increasingly, our subspecialties of cardiovascular medicine and cardiac electrophysiology are divided and continue to diverge clincially as knowledge and discovery expands at an unprecedented pace in both fields. As a result of these realities, there is little need any longer for electropysiologists to understand the nuanced differences between various glycoprotein GIIa/IIIb inhibitors, for instance. EPs just need to know that all of these drugs make patients' pacemaker pockets bleed more after surgery. Likewise, do electrophysiologists really need to know the differences between multi-detector CT and SPECT scanning protocols for the diagnostic evaluation of coronary disease in our new subspecialized world of medicine that remains far too litiginous? Electrophysiologists would be foolhardy to recommend a particular scan or the proper antiplatelet agent after a drug-eluting stent given these realities. Instead, doctors of varying skill areas need each other more than ever to provide quality care, not try to harbor every factoid in textbooks between our earlobes. To think any EP or cardiologist should (or could) know the ropes of the other specialty is unrealistic. As such, I continue to wonder why the added expense of cardiovascular medicine board recertification must be added on top of electrophysiology board recertification for tomorrow's doctors, especially in this era of Uptodate and Google. No matter that your view is of these arduous re-certification processes, we need to leverage technology to improve patient care and physician knowledge rather than pretend we don't need it. Force-feeding busy clnical doctors with more facts than they can ever hope to recall is frustrating, unnecessarily time-consuming, and may even have the unintended consequence of detracting from actual patient care delivery.

Secondly, ABIM re-certification test-writers fail to teach doctors how new CMS coding and billing requirements can adversely affect their colleagues and patients. For instance, no where is this more evident than the confusion that surrounds classification of patients coming to a hospital for "observation" or "inpatient" admission. As any skilled clinical doctor understands, what is billed and paid to the patient, doctor and hospital system rests heavily on this definition. Does the ABIM teach doctors this? No. Yet the financial and quality of care implications of this definition to both patients and doctors are very significant depending on how a patient stay in the hospital is defined by payers. (If you don't know this, dear doctor, you should.)

Thirdly, clinical physicians can even teach the more academic ABIM members a thing or two. For instance, maybe doctors who actually care for patients could insist that ABIM members teach doctors how to use vascular ultrasound devices to improve the safety of vascular access for our patients. Why isn't such a skill taught by our board reviewers who claim they are interested in improved patient outcomes? Might it be because it requires each of us to actually touch and care for a patient, something we get pretty good at after thirty years of providing care? Requiring academic discussions of obscure genetic disorders might make for good test fodder, but such obscure instruction completely misses important aspects of physician competency and patient safety.

This is not to say that all academic learning in medicine is without utility. On the contrary, learning by physicians will always remain an essential aspect of caring for our patients. I know that the many excellent doctors that have written modules for board certification preparation purposes have made every effort to make the re-certification process as meaningful as possible for doctors. But we should acknowledge that all doctors already have to "prove" that we participate in learning when we have to submit "certified" CME certificates to maintain licensure. Every doctor in America constantly has to "prove" we don't hurt people to our quality assurance committees and to the legal community. To force additional expensive and unproven training that is out of touch in so many ways with the way medical care is being delivered now may be having significant unintended negative consequences, too. We should start asking if the ABIM could be causing more harm than good as doctors become increasingly frustrated by the many bureaucratic and administrative hoops that increasingly detract from patient care.

After all, it's the lack of time left in the day to care for our patients that's most likely to harm them, not whether we pass a test or not.

-Wes

Monday, October 07, 2013

When the Best Stuff Ends Up on Twitter

Keeping a blog, I feel like a dinosaur, but I do it because it's a place I can return to to find a thought.

I think, I write, I put some thoughts down in this space. The piece is published here and then "fed" to Twitter and to an "RSS feed" for wider distribution. People then come here and read the piece. People like the thought. Others hate it. So what do they do? They "retweet with comment" on Twitter (or Facebook) and their view evaporates in seconds to another social media space.

It's an interesting phenomenon, and perhaps one brought on by multiple social media outlets and voluminous comment "spam-bots" that have led folks like me to have to implement difficult "Captcha" screens to limit the garbage that can appear in the comments section of blogs. (Some IT spam marketing experts have discovered how to break Captcha screens, too).

Oh sure, I could put a live stream of Twitter comments on my sidebar, but as the Twitter feed scrolls on with time, the insightful (and often helpful) thoughts are lost into the void of the inter-webs. The conversation dies quickly and many people who read the post later miss those thoughts.

Does anyone know an easy way to automatically add Twitter "re-tweets with comments" that occur on Twitter to the comments of an individual blog post? This might help solve this conundrum.

In the meantime, consider taking a second to leave your comments here for others to read so your brilliant thoughts don't evaporate in seconds into the Internet ether.

After all, your thoughts matter in "social" media, remember?

-Wes

Friday, October 04, 2013

How to Solve the Doctor Burn-out Problem

A piece recently appeared in the New York Times entitled "Who Will Heal the Doctors?" The piece is written by Donald Borstein and I encourage all to read it. Mr. Bornstein offers a solution to the doctor burnout problem in health care, a course called The Healers Art, now being promoted in US medical schools that uses "mindfulness" as his means of creating compassionate, caring doctors as a way forward.

I should say at the outset, that I do not disagree with the concept that doctors should not be more attuned to the circumstances for which they are being trained. But the overall argument that such "mindfulness" practices can repair his so called "McDonaldization of Medicine" is somewhat disingenuous concept. It skirts the very real challenges doctors have today when caring for patients and the many layers of bureaucracy and paperwork, both electronic and manual, along with the hidden costs that their patients are subject to as a result of doctor orders entered on a computer as they try to follow certain care "standards."   Blind-siding one's patients doesn't make for the best of relations.  Still, as bad as these realities are, they are probably not the reason most doctors are turning away from medicine.  I think there's another issue that is even bigger.

I believe the overriding reason doctors leave medicine is because there is a  growing hostile dependency patients have toward their doctors. 

I have mentioned this concept of hostile dependency before.  The theme is like an adolescent who realizes his parents have feet of clay.  In adolescence, he comes out of his childhood bubble and realizes his parents have failures and limitations because they are human beings.  This results in the adolescent feeling unsafe, unprotected and vulnerable.  Since this is not a pleasant feeling, narcissistic rage is triggered toward the people he needs and depends on the most.  Yet (and this is important) none of this occurs at a conscious level.  Most of us understand this behavior simply as "adolescent rebellion," not understanding the powerful issues at play.  So when we spotlight doctor burnout, or, say, the lack of patient safety in hospitals without acknowledging the realities health care workers face like looming staffing shortages and pay cuts, we risk fanning the flames of narcissistic rage against the very caregivers whom we depend on the most - the very caregivers who are striving to do more with less, check boxes while still looking in the patient's eyes, meet productivity ratios, all while working in a highly litigious environment. 

A comment from "Victor Edwards" posted after Mr. Bornstein's article demonstrates this growing hostile dependency toward doctors perfectly:
Doctors? I no longer afford that kind of respect: I call them "medical services providers." They and their families and the medical cabal created this mess when they got control of med schools so that the wealth of a nation would remain in the hands of a few medical elites and their families. The very notion that doctors are smarter, more productive, more anything than others is ludicrous. They are among the worst sluff-offs of our society, yet the richest at the same time. It is an unreal world they have created themselves and they are now watching the natural outcome of such a false system.
How do we fix this attitude toward doctors?  Who would want to work in an environment where patients perceive their doctors so?

Yet this is what we're creating with our increasingly consolidated "McDonaldization" of medicine.  Given where things are heading, I'm not sure this will be an easy fix as doctors are shoved farther away from the patients.  But let me be perfectly clear: if you want to keep doctors from getting burned out quickly  in medicine, it is this growing hostile dependency that patients have toward their doctors that must be addressed head-on.

-Wes


Tuesday, October 01, 2013

Ten Crackers

Graham crackers.

For years they have been an on-call snack staple for young doctors in training throughout the United States.  These little morsels have probably saved more lives than defibrillators after hours, especially if they are topped with a hefty dollop of peanut butter.

Admittedly, these flat brown crispy tastees don't contain much nutritional value.  They are probably a dentist's nightmare.  But after many late hours on call well after the dining hall closes, you'd be surprised how good these little devils taste, especially when they can be enjoyed in a quiet reflective moment alone or with a colleague in the nutrition room.  Graham crackers have a way of bringing you back to earth after you've dealt with a code, had to pronounce someone dead, or worked through a difficult family interaction in the wee hours of the morning.

But times are tough for hospitals now: censuses are down (as are revenues) as the uncertain effects of health care reform descend. Consequently, it makes sense for hospitals to trim budgets where they can.  After all, if its between graham crackers or nurses, I'm sure we'd all agree that graham crackers should be trimmed before nursing staff.

But I wonder if supplying an entire ward of fifty patients with only 10 of these little packets a day makes sense for physician and nursing morale.  Doctors and nurses, already dealing with reduced incomes and threatened with even more to come, are finding it harder and harder to find the tiny perks that make the late nights and long weekends tolerable.  Finding none of these hidden snack treasures on a ward after working 15 hours straight certainly isn't the end of the world, but when people are tired and hungry, it's noticed more than any highly-paid administrative decision-maker who's tucked neatly in bed could ever imagine.

Good leaders listen.

Good leaders know the value of small gestures.

But it's only the best of leaders that appreciate the importance of an ample supply of graham crackers.

-Wes

Welcome to the New Health Care

As seen a Boston Logan airport this weekend:

Welcome to the New Health Care (Click to enlarge)
As of 10:15 pm on 30 Sep 2013, the official Illinois insurance exchange website with its reported 165 options for health care coverage called GetCoveredIllinois.gov  (and run by the Federal government) has yet to launch.

I wish I could have critiqued the site and the health plan offerings with their out-of-pocket costs for the Big Day.

But it was not to be.

The great irony in all of this is that really, nothing is new.  Everything, it seems, remains cloaked in secrecy.

Oh sure there are things called "exchanges" now.  And millions upon millions of dollars will be spent on internet, social media, TV, print, and radio advertising touting the law.  There will be counselors there to help people make an "informed" choice.  But there's still a new complicated, unreadable law that promises much, but delivers, well, we're still not really sure.  There have been so many promises, but no one knows (yet) what we've given up in return for the monstrous bureaucracy, new payments, and massive consolidation of doctors offices and hospital systems that this law has already created.  Oh sure, the least risky adult population under 26 can stay on insurance, but now millions of young people who make $20,000 per year will be signing up for something that costs one tenth of their salary annually ($163 / month x 12) and have no idea in the world what they're getting (really) for their money.  Oh, sure, they get well doctor visits, but what does Insurance Company B have over Insurance Company C, or company Z?  Why do people have to add a zip code on their websites - have some areas gotten political favors in exchange for lower costs when others don't?

No one has a clue.

And that will total out of pocket costs really be in terms of "co-pays" and "co-insurance" kick in?  What happens when an insurance company refuses to pay for a service because it wasn't the service they chose for people covered in their plans?

No one has a clue.

And how long will people have to wait for an appointment after 1 January 2014 for their Medicaid care, in a system that already can't pay its bills?  If my clinic's any indication: today, this minute, it's already a two and a half month wait for a routine follow-up appointment.

You see, there are only so many of us, and millions more patients on their way to Great Expectations now.  But as the new law has been taking shape, there has been downsizing, trimming of staff, more work for those who remain, and lots of doctors and nurses dropping out, moving on, or retiring early because they've been given sweet deals, or really had no choice.  Many are already frustrated, burned out, or getting to the point (sadly) that they really don't care any more as more an more administrators are hired to tell health care workers how to work without doing the real work themselves.

So things will have to change under they weight of it all and they will.

But for now, it's all "new," so enjoy.

-Wes

Wednesday, September 25, 2013

When Doctors' Names are Bought and Sold

Recently, an envelope arrived for me containing an advertisement from Mercedes-Benz:

Mercedes Benz Offer (Click to enlarge)
The advertisement was co-branding with the American Medical Association, leading me to suspect the obvious: my name was sold.

Why does this bother me so?  After all, the AMA advocates for physicians, don't they?  Surely they need the money to do all their important policy papers and lobbying activities on Capital Hill, right?

But read the advertisement.  It says: "Mercedes-Benz and the AMA have entered into an agreement to provide members in good standing an incentive of up to $4000 on the purchase or lease of select new 2013 or 2014 Mercedes-Benz Models."

So, is there a kickback for the AMA as well?  That is, for every referral that the AMA gets credit for, they make even more money?  How much?  And what about the Physician Payment Sunshine Act now in play?  Will doctors that claim the credit be on the hook for public disclosure?  Why am I, an AMA non-member, receiving this notice?  Are they counting me in their statistics of supporters when AMA policies are developed?

Perhaps.


I understand the simplistic logic behind the AMA's move to sell my name. But policy makers should be aware of this practice and how the AMA may be using doctors' names in their database to reinforce their positions.  The AMA also sells my name to drug companies who track my every prescription, and the results of this practice since the new novel oral anticoagulants have been released has been even more dramatic.

You see I am an early adopter and an influential thought-leader to drug companies who scour the internet for physician feedback.  Well, it's time to give some to make a point.

The next time a drug rep for Xarelto (rivaroxaban) follows me to the parking garage arguing why their drug is better than Eliquis (apixaban), consider the consequences.  But why did this unfortunate episode happen?  It happened because my personal information could be tapped by pharmaceutical companies courtesy of the AMA's Physician Masterfile, so my prescription practices are carefully followed.  When I use a competitor's drug instead of someone else's, the drug lunches suddenly appear and the persuasions begin.  You can almost hear the pharma managers in the back room: "Get over there, show the guy how rivaroxaban's better!  We had sicker patients!  We're a better company!  He's easily swayed! Buy 'em a better meal but be sure to have him sign in for his lunch!  Go!  Go!" 

What a mess.  All because my name is for sale to anyone who wants to cough up a pretty penny to the AMA. 

-Wes

Monday, September 23, 2013

Reviewing the 2013 EP Board Review Course

This past week I sat for my third board review course in anticipation of my upcoming third EP board recertification. It was a well attended event of about 150-160 electrophysiologists, some from as far away as Alaska. That, I suppose, is one of the attractions of having this course in a city like Chicago: it's a major central airport hub and has plenty to see and do for those hearty and financially solvent enough to spend the evenings out at a nice restaurant or club. For me, a native of the Chicago area, I was lucky enough to stay in my own home and just had to brave the traffic and $35-a-day parking fees. Others from out of town bore a much larger expense in terms of lost days from work, hotel and transportation fees. The meeting was held at the Marriott Renaissance Hotel on 1 Wacker Drive in Chicago, just a few blocks from Michigan Avenue's shopping district downtown - not the cheapest hotel in Chicago, nor the most expensive. Perhaps it was held there for the comfort of the rooms, the size of the lecture hall, or a need to provide a central Chicago location, but given the amount of time we spent in the lecture room and the social life of most serious electrophysiologists I know, I wondered why it wasn't held somewhere less expensive. After all, cost remains a huge concern (if not overriding one) for doctors attending these courses.

The course began Thursday afternoon at 1pm and went until 8:30 pm Thursday, 7:45am-5:30 pm Friday and Saturday, and concluded Sunday with a rushed morning review of pacing principles from 07:45 am to 12:30pm. (Completing the course on time was critical for those who had to catch planes home on Sunday)

I paid the extra money for attending a maintenance of certification test session before the main session began to earn a few points. This clearly was not worth the extra money in my view, as it was just an extra Workshop that included a bunch of typical board-style questions with the answers in the back of the book. My recommendation would be to save your money and take the online versions that come with one's recertification fee. It just seemed to be another cash cow for the ABIM and HRS.

The course materials were printed, and the majority of doctors polled (75%) preferred their materials this way, despite the Heart Rhythm Society (HRS) clearly leaning to providing the material electronically on a thumb drive. They also offered (with a $1300 discount if you attended the session) the full lectures (with audio and slides) to members who wanted to cough up even more money so they could review the materials at another time. (I passed).

The main course was taught by established names in EP and the Heart Rhythm Society: Ken Ellenbogen, N.A. Mark Estes, David Haines, Fred Morady, William Stevenson, among others. These are guys that taught me, they've been doing it a while, and they're good at what they do. As such, the lectures were paired down to the essential principles and generally well-organized with good audiovisuals and sound, but were peppered the same pimp items that you'll still have to memorize despite our new era of Google. I suppose having these things pass your cortex once so the recognition of these syndromes might be realized in one's practice, but in this era of Google whether memorization is really necessary is another matter.

But did I learn anything? Okay, I have to admit I did. New things I learned included a few pearls about Early Repolarization Syndrome (and is probably fair game for boards), the genetics of plenty of obscure diseases, and about how many ways a doctor can get pimped on a cleverly written examination. Given these realizations, I hope my chances for passing my board certification were improved as a result of attending this course. We'll see.

It was kind of sad (yet psychologically affirming) to see Sonny Jackman, an icon of accessory pathway ablation and EP, in the audience with me. It was particularly entertaining when he had to hop up and explain a tracing to the audience on behalf of the lecturer (truly a highlight). But I also wondered why Dr. Jackman was there. Sadly, I knew the answer: he's no different than the rest of us now and understands that it won't be long before the bureaucratic machine called medicine will require passing an irrelavent test to practice medicine.

It was this last issue that was most relevant and prescient. Mark Estes (someone who has sat on the test-writing committee in the past) tried to explain how the ABIM decides how many recertifying doctors ultimately pass their examination. "This is a sensitive and unpopular issue for EPs in practice," he said quietly. You could see people agreeing. But as he explained how the ABIM determines how many recertifying EPs pass the recertification exam he admitted, "I really have no idea how they decide." He continued, "But when we look at the trend line for the percent passing from prior years, you can see that last year's percentage was down a bit." He then showed the trend line.

Think about that. No one has an idea what consitutes the criteria for a "passing" grade for recertification, yet here we are spending too much money on a process that has little to no proven patient care benefit in terms of quality care. This non-transparent scoring criteria adds to the problems with recertification in my view, since it would not be difficult to think that granting of a passing grade for re-certification could be used against certain subspecialites for any number of obscure reasons (eg., the desire to downsize the specialty, political differences, etc.) One only has to consider how the IRS was used against non-profit political organizations to get my paranoid drift in the era of medical cost conservation here. Perhaps this is a bit overdramatic, but it makes you wonder, doesn't it?

So I'm back in the salt mine of everyday practice now. Hopefully the course helped and will prove itself valuable for me in the future. Honestly, every effort was made to make the sessions tolerable and informative, I just wish I understood why the re-certifiers needed to be there. But I'm trying to cope with the reality of the times and I just hope the ABIM won't decide not to pass me for what I've said here.

-Wes

Saturday, September 21, 2013

Shadow Puppet: An App That Lets iPhone Pictures Tell a Story

They say a picture is worth that thousand words, but nowhere is this more true than with a new, free, iPhone app called Shadow Puppet that lets you turn selected photographs on your iPhone into a narrated video storyline.

I saw this app reviewed over at Techcrunch and immediately saw its potential as a teaching aid.  The app allows you to pick a series of iPhone photos from your camera roll, order them, and then record a narrative about your pictures.  What is unique is that you can zoom or move between photos as you tell your story, annotating them by touching areas on the photo that you are discussing as it records the video.  (Very cool).

Here's my very first video I made with the app describing the new Zio XT patch monitor that records 14-days of a patient's heart rhythm that we've been using in our clinic.  Simply made, these video clips are easily shared via email, Facebook or Twitter.  For this particular video, I still had to edit portions of the patient's report on Photoshop, then sent the images to my iPhone but, still, that was easily done.

Want to teach a fellow how to implant a pacemaker?  Take some photos and show them!  Have an EKG that has a finding that you're not sure about?  Snap a picture (without patient identifying information, of course) , annotate it with your question and send it to your EP!  Simple, elegant, and who knows, maybe even life-saving.

-Wes

Friday, September 20, 2013

For Medicine: Go Slow

Three years ago, in the midst of all that was happening with health care reform, I thought about if I'd ever recommend medicine to my daughter.  I thought and thought about that issue and looked deep inside myself for reasons one might still choose this profession, then penned "The Top Ten Reasons to Be a Doctor."  It is, by far, the most popular post on this blog, having been read by more people than any other I've written.

But little did I think my youngest might heed this advice.  Unknown to me, she left for college as an environmental studies/economics major, to abruptly decide one week later after some soul-searching of her own to consider a pre-med curriculum.  I couldn't help but feel a rush of pride, but also a huge amount of concern, for no one can tell anyone else what this path is like until it's been traveled.  One thing I know: it she wants it, she's very capable of doing it.

And as part of her growing enthusiasm for this field and (I suspect) recent rewarding experiences she had as a lifeguard at our public beach this past summer, she's even thinking about training to become an EMT while studying at college.

My first thought, of course, was "Heck ya!  Dive in! You'll love that!  What a great skill to have!"  But after a night of rest and reconsideration, I have another piece of advice for her.

Go slow.

You see there's a little secret every doctor lives with throughout their career and never talk about: their closet.  We've all got one and we use it sparingly, and you don't want to fill it up too soon because it has to last your entire medical career.

You see, your closet is where you store life's experiences that are so horrible, so painful, so shocking, that you can never tell anyone (except, perhaps, another doctor) about them.  It is the place where you put the images you see that you'd really rather never talk about.  Ever.  Really: the gross stuff: the gross images, the gross sounds, and the gross smells.  Things so bad I can't even write them here.  That stuff.   And I know EMTs, like doctors, have a closet of their own.

You'll be surprised how dark that closet is and how fast it can fill.

But you also need to know that the closet exists, it is real, and how to clean that closet when considering the path toward becoming a doctor.  This is probably one of the most important skills outside of medicine that a doctor can muster.  So, I'll ask that my daughter to reconsider the EMT class for now and do something entirely, crazily, stupidly different and fun. (Whether she'll do this or not remains to be seen.)  For this is how we have to learn to clean a bit of our closet, or at the very least, make it a little bigger.  Use this precious time before all of the isolation of studying and commitment that medicine requires to expand yourself.  Learn to play badminton, to paint, to play a guitar, to debate, to sing, to ballroom dance, to fly or just to love and appreciate what's out there.  What ever.  The point is this: learn to do other things besides medicine that will engage your brain, hold you firm, and make you happy.  Because medicine's a long haul: a lifelong haul that never keeps adding to that secret closet.

As a student of medicine, your job, throughout all that lies ahead, is it to make sure you always have the renewable resources to get outside medicine so life stays rich and medicine remains, net sum, rewarding. Because as as rewarding as medicine can be at first, it can wear you down unless you always know how to properly size (and maybe even start to empty) a bit of that secret closet that doctors all share.

-Wes

"Emptying the Closet"
Oil on Canvass, 36" x 24"


Thursday, September 19, 2013

Review: The Strategy That Will Fix Healthcare

Two days ago, I was directed to a piece entitled "The Strategy That Will Fix Healthcare" from the October issue of Harvard Business Review by a reader of this blog who knew I had an interest how we can get our heads around the enormity of lowering costs in health care. The piece was written by Michael E. Porter and Thomas H. Lee. Mr. Porter is a Bishop Lawrence University Professor at Harvard University based at Harvard Business School. Dr. Thomas H. Lee is the chief medical officer at Press Ganey and the former network president of Partners HealthCare and has been a professor at Harvard Medical School and Harvard School of Public Health, as well as an associate editor of the New England Journal of Medicine in his former life. Needless to say, they are perfect fodder for the Harvard Business Review.

In their article, the authors speak of their "fundamentally new strategy" that, "at its core is maximizing value for patients: that is, achieving the best outcomes at the lowest cost."

Boy, who wouldn't want that?

In their piece, they then propose six steps to "fix" healthcare:
  • 1: Organize into Integrated Practice Units (IPUs)
  • 2: Measure Outcomes and Costs for Every Patient
  • 3: Move to Bundled Payments for Care Cycles
  • 4: Integrate Care Delivery Systems
  • 5: Expand Geographic Reach
  • 6: Build an Enabling Information Technology Platform
But where, exactly, are the author's going? Is their prescription really a "fundamentally new strategy?"

As nicely written as the article is, I don't think so.

To me, their "Integrated Practice Units" sound strikingly similar to the "Pit Crew model" previously promoted by others. Measuring Outcomes and Costs, while it sounds nice, is enormously difficult as "outcomes" that benefit business might not be "outcomes" that benefit patients and costs (both direct and indirect) are rarely, if ever, disclosed publicly.  "Integrated Care Delivery Systems" with their high through-puts sounds an awful lot like someone else's Cheesecake Factory analogy. And bundled payments are hardly "new," having already been implemented in some health care markets.   When put this way, the authors'  "new strategies" sound like a  rehash of plenty of Harvard "old school."

Here's A Real Idea to Ponder

If these authors were really about value to patients, they need to think like patients.  Here's an example:

Some time ago, I inquired from one of the major medical device companies if they would sell a defibrillator directly to a patient.  That's right: direct-to-consumer with no middle man.  They could name their price for he had the cash to buy it. That's because he is self-insured business owner. Being a business man, he wanted to purchase the device himself and then shop the implant between centers to get a deal in a way not too dissimilar from the way one man recently shopped his hernia repair.

But what I was told was surprising.

I was told they could not sell the defibrillator directly to a patient because "we cannot ship directly to patients due to regulatory requirements around product tracing abilities."

What the...?

Seriously? Our regulatory environment prevents such a deal? Where's patient "value" there? Why do medical device companies sell  "only to doctors and hospitals" and not to patients themselves? Where is the patient "value" opportunity there?

But to Porter and Lee, this form of "value" is ignored.  They're business guys.  In their pro-business environment, "value" is defined as lower overhead, lower expenses, and more volume.  And thanks to prices that are artificially held high by the government's (Medicare) payment rates, they can continue to mark-up prices to cover other expenses which may not be of value to the patient, like lobby facades. After all, they have large indirect costs to support. Insurers, too, must assure their cut for profits as they negotiate what they'll pay for device implants.  And still more layers of bureaucracy exists with complicated coding, billing and collection that also has limited "value" to patients, especially in the case of a patient who is willing to pay cash.

We should ask ourselves if these intermediaries are the reason we are where we are in the meltdown of health care costs.

I think this more transparent model (or a variation of it) will become more common in the years ahead as patients are forced to foot more of their medical care bill.  Certainly, it won't be for everyone.  But as we continue down this health care reform path, patients will turn a keen eye to health care out-of-pocket costs.   To assure value for themselves, patients will demand THEY pay for the device, THEY chose their provider  or treatment facility, THEY decide who receives funds for care delivery, and THEY have access to their medical and device data.

THAT is the novel health care cost model that's coming that will be disruptive, not an overly simplified six-step business school "fix."  Businesses involved in all aspects of health care that provide patient-care materials, be they drugs or devices, would be wise to be an early adopter of the patient-empowerment movement. 

After all, most patients (I believe) will eventually demand real medical value for themselves, not business.

-Wes

Sunday, September 15, 2013

When We Conflate Health Care With Medical Care

From Marilyn M. Singleton, M.D., J.D.:

“Politics is the art of looking for trouble, finding it everywhere, diagnosing it incorrectly, and applying all the wrong remedies.” -Groucho Marx

The politics of selling the Affordable Care Act (ACA) focuses on promising health and wellness. Somehow, having “coverage” is supposed to get you to a primary care doctor, who will keep you healthy. And if he doesn’t, he will be held accountable by not being paid.

The fact is that “healthcare reform” is not going to cure America’s health problems.

Physicians, think tanks, and politicians are pointing out a myriad of problems with ACA. But most of them miss the main point, which starts with calling it “healthcare reform.” The term, and the conversation about it, conflates health care and medical care. But they are not the same thing. Individuals are in charge of their own health care. Physicians provide medical care to those who become sick.

(Read the rest, especially the comments)
As I and others see the problems with "wellness initiatives" promoted by politicians and the insurance industry as cornerstones of our efforts to cut costs in our medical system, we should consider if institutional financial incentives will thwart any effort to achieve cost savings as physician productivity quotas are increasingly turned to as the driving force de rigueur for hospital profitability. Unfortunately, physicians are losing their ability to be stretched much further, especially as they struggle to keep up with the mushrooming number of inefficient certification and data-entry requirements, flooded e-mail in-boxes, and coding requirements necessary to continue practicing medicine in our new "reform" era. Then add the increasingly frequent hassles doctors are experiencing with their patients' insurance claim denials that go on for months. Medical care suffers as a result. Even our frontline force for quality medical care, nurses, are being stretched thin as many of their ranks are either let go or recruited as cleaning crews on top of their other patient care responsibilities.

Meanwhile, the insurance companies are recording record profits as Americans pay more and more into our system.

But, hey, thanks to the Electronic Medical Record and health care "reform" it sure is easy to order another colonoscopy in the name of "wellness" and "health care," right?

-Wes

Thursday, September 05, 2013

When Media Doctors Play Doctor

After George W. Bush's recent controvertial stent placement, news organizations were hot to jump on the media buzz created by a former President's health issues. Perhaps the funniest moment of all came from Fox News' proported medical "A-team" member, Marc Siegel, MD.

Dr. Siegel is an internist by trade, and when internists are handed a cardiac stent to open on TV, the ensuing moments were something to behold:


The special moments begin a 2 minutes into the video where Dr. Siegel attempts to open the stent packaging (even resorting to using his teeth 22 seconds later). After failing, he hands the package back to the anchorwoman who hands the challenging packaging to her TV crew to open.

Once the package contents are returned to Dr. Siegel, he remains baffled and displays the stents flush port to the TV audience as the stent.

Sorry, but it rarely gets better than this on TV...

-Wes

Tuesday, September 03, 2013

Left to My Own Devices: A New EP Blog is Born

Good scientific writing is hard to find, but sometimes good writers find scientific writing. 

Such is the case with Edward J. Schloss, MD, a cardiac electrophysiologist from Cincinnati, Ohio who entered the social media space via Twitter (@EJSMD) several years ago and began writing a series of articulate and remarkably prescient guest posts for Cardiobrief.org about St. Jude's Durata defibrillator lead's structural similarities to the Riata ST lead (see here, here and here) , among others.  As he hesitated to enter the blog-o-sphere personally, he also posted on fellow EP colleague John Mandrola's blog as well.

Now, with a bit of trepidation, Dr. Schloss begins his foray into the blog-o-phere with a great review of  the utility of cardiac resynchronization in patient with narrow-QRS-complex cardiomyopathy on his new blog, Left to My Own Devices.

Go now.  Welcome Dr. Schloss.  Then bookmark his blog's webpage and add it to your feed reader. 

You'll be glad you did.

-Wes

Monday, August 26, 2013

On Sabbatical

I will be sparsely interacting with the internet as I take my last child off to college this week.  It's a strange time - one where the home becomes more quiet as a moment ends for the parent yet heralds and exciting beginning for their child.  Others have recently articulated this strange time well, so I leave you with the words of a much better writer, Michael Gerson of the Washington Post:
"Eventually, the cosmologists assure us, our sun and all suns will consume their fuel, violently explode and then become cold and dark. Matter itself will evaporate into the void and the universe will become desolate for the rest of time. ... (Read the rest)
-Wes

Saturday, August 24, 2013

The Cloudy Aspects of the Physician Payment Sunshine Act

Another seemingly harmless bureaucratic initiative aimed at physicians sunk its taproot deep in the daily workings of medicine this month. The Physician Payment Sunshine Act promises transparency in all industry dealings with physicians by shedding "light" on the issue of payments to physicians from pharmaceutical companies and medical device manufacturers. In turn, it will save the system money, since all those freebies bestowed upon physicians when the corporate world came knocking can now be accounted for and physicians will be shamed into proper behavior.

Meanwhile, back at the drug company headquarters, some poor schnook gets to type all the names of the nurses and technicians that enjoyed their meal from the echo lab, cath lab, stress testing lab and were asked to place their name on a sign-in list so it can be entered on a multi-million dollar database designed to feed the government Big Data Bosom in the sky.  Busy doctors dart in, grab a bite, and go.

No need for them to sign-in.

You see, it's a bad marketing strategy to ask a doctor to sign a form as you peddle your product. And since no one is monitoring the accuracy of the sign-in sheets, as they have a few names to justify their effort and expense, well, they've done their part.

Why is this expensive data collection charade taking place? How much does it cost us? Does it change pharmaceutical tactics for marketing to doctors?   Of course not.  Yet there remain central planners who remain convinced (I mean, convinced!) that such monitoring works. It's a classic wish: just like the government's new HospitalCompare website, which promises to collect data on readmission, pneumonia, infection and death rates (with more to come) in the hopes that people will make "smart choices" about their health care. Do people really make their choice of health care facility based on such poorly-collected data placed on a website? I don't think so. Most people never think about their health until they have to arrive in an Emergency Room blindsided by an unexpected health crisis. They are not checking websites about payments to doctors - especially websites set up by the government. They want access to their local health care system and prompt, quality care. Yet were we are once again using Big Data filled with Bad Data as an ill-conceived and expensive social engineering exercise.  And this cost is passed on to health care consumers. In short, it's another perfect storm of wasted resources in the practice of medicine.

"But Dr. Wes, how can you say such a thing? Can't you see this Sunshine Act developed by Congress as part of the Affordable Care Act will disclose all of those greedy physicians who want to suck the health care system dry of all of that money? Aren't there benefits to the public transparency of these payments?"

The irony of this whole law is that Big Pharma and Big Medical Device Company already reports the money they give doctors to the government via the IRS in the form of a 1099-Misc. (Recall that the IRS is now firmly a part of our new health care law).  But instead of looking deep within the bureaucratic governmental morass for solutions to physician payments from industry, a new knee-jerk law was enacted to parade before the press to show how sincere the medical device companies and pharmaceutical companies are about the need for such transparency. Meanwhile, it's business as usual as backroom pricing of drugs and devices continues.

War room strategists have known this policy tactic for years: it's called diversion:  collect data on every $20 dollar physician lunch handout as our new breed of physician-employers (aka "Accountable Care Organizations) negotiate sweet deals with their insurance pals, prices of hospital system charge masters edge ever higher, drug prices and device charges continue to exceed tens of thousands of dollars thanks to Medicare payments, and insurance companies offer "health plans" rather than "insurance" to their policy holders.  And let's not even talk about the favors our Congressmen and Congresswomen are afforded.

But then again, better to put doctors in the limelight rather than speak honestly of the pricing games taking place behind American's backs, right?

-Wes

Wednesday, August 21, 2013

Why Do I Try So Hard?

It's always the same: It's the fifth hour of the procedure. As your ankles ache and the perspiration drips beneath your lead, you stand there wondering why you try so hard to fix this arrhythmia. You realize this is not cost effective. You're tying up the lab. The staff and anesthesiologist are getting restless. The music drones on. You feel you're not getting anywhere. "Then again, maybe if I just try this...," you think. And you try this and it fails. Meanwhile, the fluoroscopy clock ticks, your fight continues.

Then you remember the story: the syncope, the wife, the kids, the vocation. They're depending on you. Not a tech, not an anesthesiologist, not a nurse, not an administrator. You. So you keep going, just a bit longer.

And then, sometimes, miraculously, you win. It's all worth it. You've completely changed that person's life. You are the hero. You are the superstar.

But just as often, you have to quit. Your feet are too sore, the radiation dose too high, and the hour too late to safely continue. You have to face the family, the disappointed looks, the doubt about whether you were the right person to do this procedure, and the sad look on your patient's face when you break the news.

And you find yourself asking once again:

Why do I try so hard?

Why?

-Wes

Friday, August 16, 2013

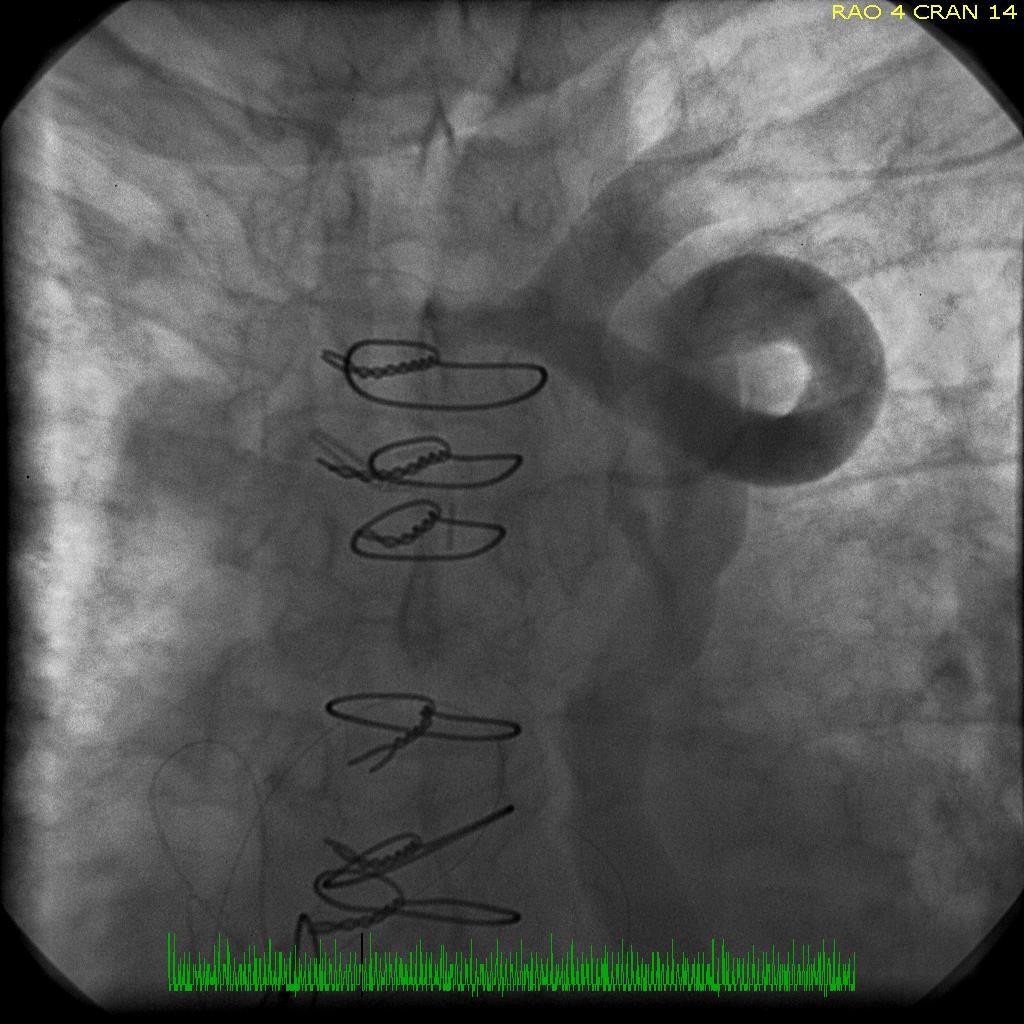
When Placing a Pacemaker, You Know You're on the Wrong Side When

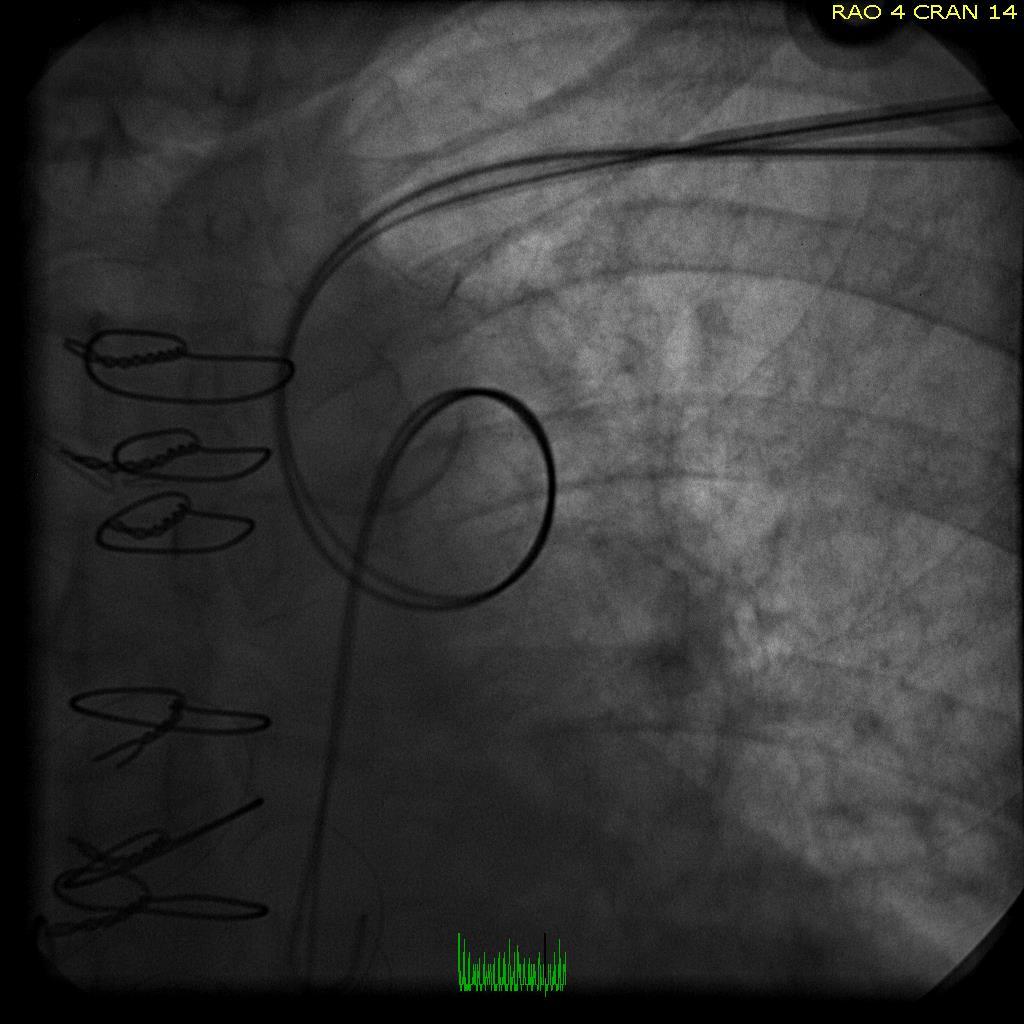
... your wires look like this: 

AP fluoroscopic view

... and the venogram looks like this: 

Results of a left subclavian venogram

-Wes

Wednesday, August 14, 2013

Heart Check Indeed: American Heart Association and Campbell Soup Company Sued

From Bloomberg:
Campbell Soup Company and the American Heart Association (AHA) were sued by a consumer who claimed the AHA fraudulently certifies the company’s products as healthy.

The association labels more than 30 of Campbell’s Healthy Request soups as “heart-healthy” even though a can has at least six times as much sodium as the organization recommends, according to a complaint filed yesterday by Kerry O’Shea in federal court in Camden, New Jersey. Those soups display the AHA’s “Heart-Check Mark” logo, which the organization licenses, according to the complaint.

Campbell, the world’s largest soup maker, and the heart association “falsely represent” that products with the logo have cardiovascular benefits lacking in other soups, according to the complaint.
Oh the irony, eh?

Who's next?  The Heart Truth® campaign, NHLBI, and the Coca Cola Company? 

- Wes

Tuesday, August 13, 2013

EKG Du Jour 32: The Misfiring Pacemaker

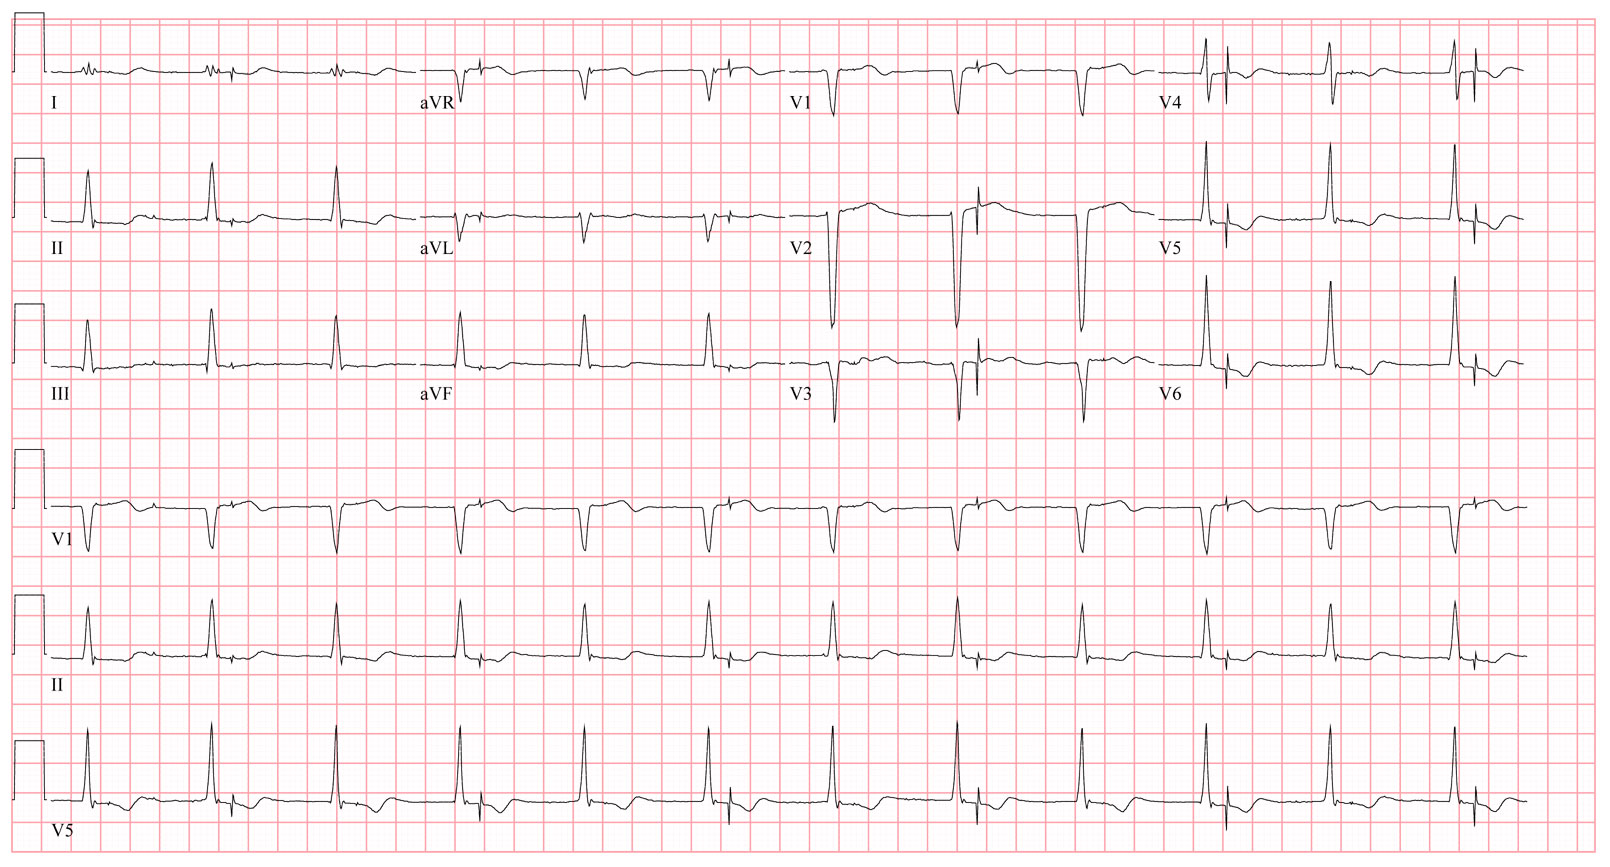
A dual chamber pacemaker was implanted the prior day by a local surgeon in the operating room.  The next morning, an EKG is obtained that showed the following:

Click to enlarge
You checked the CXR and all leads appeared to be in the proper location. 

Does the patient have to go back to the operating room?  Why or why not?

-Wes

Friday, August 09, 2013

Marketing Shared Patient Appointments

As health care reform kicks in to high gear, a new innovation in health care delivery is being touted at Cleveland Clinic: shared patient appointments. On the surface, this idea seems so efficient and social as patients with similar medical problems sit around in a group therapy session that masquerades as health care. After all, with the large influx of new patients to our health care system underway and the limited health care personnel resources available, the push for such a model was inevitable.

But many Americans are also noticing another disturbing trend: higher insurance premiums to offset the cost of those who do not have sufficient resources to pay for their care.  While the reality of our higher health care costs demand that the added costs be paid by someone, I suspect most of those who will be paying higher premiums didn't think they'd have to "share" their physician appointments with others. 

But here we are.

For large health care systems, shared patient appointments offer the promise of high revenue streams with low overhead costs.  As such, there is no downside to promoting such a model:
Since 2005, the percentage of practices offering group visits has doubled, from 6% to 13% in 2010. With major provisions of the Affordable Care Act due to be implemented by next year, such group visits are also becoming attractive cost savers — patients who learn more about ways to prevent more serious disease can avoid expensive treatments. (ed's note: Sales pitch - there are no data that group appointments "prevent" more serious disease or "avoid" expensive treatments)

“It’s a different way of speaking about health that is more about friends around a circle learning together than talking with an authority figure in a white coat,” says Dr. Jeff Cain, president of the American Academy of Family Physicians, in describing shared medical appointments. Think of them as a blend between group therapy and support groups. The net effect is the same – a sense of comfort, support and even motivation that comes from sharing similar experiences. (ed's note: Easy for him to say.  Any proof?)
Looking at this, how could anyone argue?  It seems like such a helpful premise.  But patients subjected to such a system have to agree one very important issue: surrendering their privacy:

But they do require divulging and discussing private medical information in front of strangers (albeit ones who have signed waivers not to talk about other patients’ medical histories outside of the visit).
We should ask ourselves: how will assurances of patient privacy in such a setting be enforced?  If another patient discusses a participant's health care needs and concerns outside of such a meeting, will that person be reprimanded?  If so, how?  And what extent must HIPAA privacy laws be waved as a result of this model?  
 
These are only a few of the concerns for patients.  We should also ask what the outcomes are for such a model?  What value to patient's get for their health care dollar if another member of the group is more vocal and insists on speaking while others have to remain mute?  Will they be guaranteed an opportunity to have their question(s) addressed?  And how will patient's be selected for participation in these groups?  Will diagnosis codes be used?  If so, what happens (psychologically) to a group of early diabetics who are placed in a group with a diabetic with more extensive disease?  Might there be negative repercussions when a young diabetic sits with a diabetic amputee or renal patient?  
 
Efficient health care delivery models are needed going forward, but attempts at social re-engineering that can alienate some patients in favor of others and stands to profit a system rather than the individual demands careful evaluation before marketing such a model as gospel to our health care system.

-Wes


Saturday, August 03, 2013

A Case of Fraud

He was a slender-framed man, mid- to late-sixties, with a kind of ridden-hard-put-away-wet complexion.  It was clear the years had not always been good to him, but being the kind soul that he was, he had plenty of friends.  It was a beautiful summer day to spend with friends for a barbecue, but he arrived feeling puzzled why he collapsed at home earlier in the day.

He stopped at the keg and poured himself a beer in a red solo cup, and as he approached his friends with a smile, he did it again, this time which such gusto that his beer went flying and the thud he made when he hit the ground made everyone gasp.  He laid motionless for a moment face down on the ground while his friends rushed to his aid.  An ambulance was summoned as others rolled him over onto his back.  He began to move - slowly at first - then more purposefully.  As sirens approached, he asked his friends, "What just happened?'

A bit later, he arrived in the Emergency Room, awake, alert, pleasant, and seemed - on the surface at least - fine.  His vital signs were normal - perfect, in fact.  About the only things immediately noticeable was his thin frame, his coffee-stained teeth, and a clump of grass in his hair that the nurse kindly removed.  He was placed in the gurney, an IV was started, blood was drawn, and EKG was performed as a few "hellos" and "what happeneds" were exchanged, then off to the CT scanner he went to rule out an intracranial process.  It was normal and his EKG showed a first-degree AV block and incomplete left bundle branch block without evidence of acute injury or prior heart attack.

He returned from the CT scanner and was examined a bit more closely.  A loud, blowing, holosystolic murmur was heard by the medical student.  In fact, it was loud enough to create a "thrill" - a palpable vibration on the thin man's chest.  The medical student seemed pleased with himself, then ordered his first echo which revealed a relatively weak heart with a few chamber walls that didn't move so well, and a very leaky heart valve.  He was admitted, placed on telemetry, and seen by a cardiology consultant.  Closer inspection of the echo revealed a dilated left ventricle with a posterior wall motion defect and a central jet of mitral regurgitation large enough to fill the left atrium with a mosaic of color that extended to the pulmonary veins.  It was clear he'd need surgery, so a diagnostic catheterization was performed.  It showed three-vessel coronary artery disease and confirmed severe mitral regurgitation.  His medications were adjusted and surgery consulted.  A date for surgery was arranged at the neighboring hospital the following week and all seemed well.

But he had different plans.

As he settled down for dinner, he felt suddenly flushed, lightheaded, and broke out in a sweat.  With that, the telemetry alarm sounded and soon the room was full of people, crash carts, and hysteria.  His dinner table was shoved aside and he was laid flat as his chest was made bare.  He didn't know what all the excitement was about, but heard the words "He's fibrillating!" and then felt the cool metal discs covered with cold goo applied to his chest.  "What are you do...?" and with that, he felt his chest and arms jerk violently just before he passed out.  "Shit, he's still fibrillating!" someone shouted.  So they charged again and shocked him, this time to sinus rhythm.  The anesthesiologists who had arrived on the scene of the arrest took no chances: he was intubated and expeditiously transferred to the ICU.

Upon arrival to the ICU, the patient was clearly recovering well and quickly extubated the next day.  Beta blockers were administered additional anti-anginal and anticoagulants given.    Once stabilized, he was transferred to the surgical hospital and underwent urgent bypass surgery with mitral valve replacement.  At the time, the surgeon could see considerable endocardial scar.

His recovery was uncomplicated, but four days after his surgery, he still required external pacing.  Cardiac electrophysiology was consulted to consider an ICD placement, given his history of sinus node dysfunction, cardiac arrest, diminished LV function, and the visible presence of endocardial scar during surgery.

The electrophysiologist reviewed the case and noted that the patient's original in-house arrhythmia at the time of his "arrest" was actually an organized, rapid ventricular tachycardia that was then shocked into ventricular fibrillation by an asynchronous defibrillation attempt.  An echocardiogram performed post-operatively showed a very low EF of 23%, but a good repair of his valve and he appeared to be progressing quite nicely in his cardiac rehabilitation.  Still, it was felt he was at high risk for another arrhythmic event, so a wearable defibrillator as ordered as they waited out his conduction system a bit longer to see if it would recover function.   It never did.

So 10 days later after the sinus node failed to recover, the electrophysiologist had a choice: implant a pacemaker, or implant a defibrillator?   It shouldn't be a difficult decision in this case, should it?

But the electrophysiologist knew he'd be committing fraud if he implanted a defibrillator and billed Medicare for the device and procedure.  That's because Medicare's 2005 National Coverage Decision requires doctors to wait 90 days and then "reassessing" the patient's heart function later before implanting a defibrillator once the heart is revascularized surgically.

But he wondered about the extra risk of infection created by two surgeries (one for a pacemaker and one later to upgrade the device to an implantable defibrillator) instead of one.   He wondered if anyone ever considered the frequent venous occlusions that preclude later upgrade of pacemakers to defibrillators via the same side as the original pacemaker implant.   Even if he implanted a defibrillator lead at the same time he implanted the original pacemaker, wouldn't he be committing fraud if a more expensive defibrillator lead were billed to Medicare instead of a pacemaker lead?   And what about the added cost, inconvenience, and poor compliance rates of patients issued wearable defibrillators as they wait out the 90-day waiting period for an ICD?  Finally, what are the ethics of asking his patient to sign a form that obligates the patient to pay for his defibrillator if Medicare fails to do so when the actual costs involved to implant a defibrillator are closely held institutional secrets?

So he wrote his note.  He documented his rationale thoroughly.

Then proceeded to commit fraud.

-Wes

Refs: 

Fogel RI, et al. The Ultimate Dilemma: The Disconnect Between the Guidelines, the Appropriate Use Criteria, and Reimbursement Coverage Decisions JACC, 2013;() doi:10.1016/j.jacc.2013.07.016.

Dr. Wes: When the Feds Come Knocking

Thursday, August 01, 2013

Images of Change: Clicking is Caring


 “The secret of the care of the patient is in caring for the patient.” - F. Peabody

Submitted as part of Image of Change: A Health Care Evolution Photo Contest. Feel free to submit yours (Instructions at the link).  -Wes

Images of Change: Going Private

The Loss of Roommates, courtesy D. Graf
"I spent several days, in 2012, as a patient at two different hospitals in my pre-ablation period. I had roommates at both locations and each of them was named George. The rooms I was in are no longer shared bed facilities, they are now private. This is a profound change in health care. I learned much from both Georges and was able to listen in as their doctors and nurses filled them in about their conditions. I overheard specific information about their prescription drugs, their recommended diets and their health summary. (George I and II were able to see and hear my health are team, too). I also saw their relatives and friends come and go and felt able to ascertain which ones were there to encourage their loved one and which ones were going through the visitation motions. I heard some visitors talk about wanting to be granted Power of Attorney privileges and others asking about location of car and house keys. I also saw true friendship and empathy from some of the visitors. During the quiet times, mainly in the late nights after visitation, we would talk, compare notes about our healthcare providers, review the quality of hospital food, ask about each others work and hobby interests and generally bond. I haven't kept in contact with either George since we were hospital roommates, but it felt good to be together in a shared experience. The end of shared hospital rooms is, from a patient perspective, a major change in health care policy."

Submitted as part of Image of Change: A Health Care Evolution Photo Contest. Feel free to submit yours (Instructions at the link).  -Wes