Saturday, July 30, 2016

When Patients Tweet Their Own Heart Attack

I was called at 04:30AM for a patient with tachycardia in the hospital and as I logged into my EMR from home, I saw this on Twitter:


In under two hours, there were 15 retweets, 44 "likes," and 19 comments that appeared on Twitter (so far), most wishing the patient the best, looking forward to pictures of the angiogram, etc.

This is the lovely world of social media, but it also demonstrates his very real limitations of the medium when potential life-and-death health care issues arise.

Not a single person on Twitter with its myriad of participants rushed to Dr. Rogers' aid, called an ambulance (tho' I suppose this depends on who's "following" Dr. Rogers on Twitter), started an IV, placed him on oxygen, gave him an aspirin, grabbed that EKG, prepped the cath lab, opened Dr. Rogers' coronary artery, spoke to his family, or held his hand. Social media reassurance, prayers, and good wishes can only go so far.

This is not too say there is not value in those prayers and good wishes. But we should remember that medicine and medical issues are real life, not digital.

And we should never forget the limitations of all of the digital technology in the world when it comes to delivering hands-on medical care to our fellow man, woman, or child. That requires those much-less-interesting real people, real workers, and real professionals (all on call 24/7/365) to help Mr. Rogers through his ordeal.

God speed, Dr. Rogers. I'm sure you're in the best of hands.

-Wes

Wednesday, July 27, 2016

Moving Forward With Ending MOC

Legislative action at the level of state medical societies to end requirements for participation in the unproven American Board of Medical Specialties (ABMS) /American Board of Internal Medicine (ABIM) Maintenance of Certification (MOC) program is moving ahead swiftly nationwide. Draft proposals for language for resolutions to end MOC at both state and federal levels can be found here (state - Word file - Enter your state name/medical society name at asterisks as appropriate) and here (federal - pdf file draft copy). BOTH are important.

I would encourage all working physicians to adapt these proposals presented by Ellen McKnight, MD of the Florida Medical Association and present them to your state medical society/association so they may be  adopted whole or in part.

Together, working physicians can end this unnecessary requirement imposed unilaterally by members of the ABMS, ABIM, and collaborators within the Accreditation Council of Graduate Medical Education (ACGME) and Accreditation Council of Continuing Medical Education (ACCME).

Wes Fisher, MD

Thursday, July 21, 2016

The Untold Story of Three ABIM-Sanctioned Physicians

He was a bright medical resident in his third year of internal medicine residency - industrious, committed, a team player. He never thought of himself as special. He had studied hard and achieved much in his short 30 years. Not only was he nearing the end of his residency training in Philadelphia, he was married and had his first child about to be born July 19, 2007. Like most first-time wage earners, his $42,000-a-year resident salary didn't go too far as a result.

As a US medicine resident in his third year of training, he would soon be sitting for his Internal Medicine Board examination in the Fall, a requirement to assure his later employability. So he began the process of registration with the American Board of Internal Medicine (ABIM). He read the requirements and the ABIM "Agreement of Conditions" statement on the their website at the time:
Before electronically signing your application, you will be asked to read the following statement:

"By this application to the American Board of Internal Medicine (the "ABIM"), I agree to be bound by the terms, conditions, and rules set forth in the ABIM's Policies and Procedures for Certification and in this Web site, as they may be amended from time to time. I understand that by applying, I am entering into a contract with the American Board of Internal Medicine to provide certain health care operations services, including practice assessment and evaluations. The ABIM HIPAA Business Associate Agreement is a part of this contract.

I agree to indemnify, release, and hold harmless the ABIM, its employees, officers, directors, members, agents, and those furnishing information about me to the ABIM from any claims, liability, or damage by reason of any of their acts or omissions, done in good faith, in connection with this application, information furnished to the ABIM, the evaluation of my qualifications, and examinations. I agree that the ABIM may use my examination performance, training program evaluations, self-evaluations of knowledge and practice performance, and other information for research purposes, including collaboration with other research investigators and scientific publications. In such research, the Board will not identify specific individuals, hospitals, or practice associations. All practice performance data is HIPAA compliant.

I hereby declare under penalty of perjury that the information given in my application is true and correct to the best of my knowledge and beliefs.

I agree to be legally bound by the foregoing."
This statement represented the entirety of his "informed" consent for the ABIM's "research" - and from the looks of things, he was "legally bound" to comply. On the web page this  "Copyrighted Materials" clause was included as well:
Copyrighted Materials

The Board's examinations are confidential and copyrighted under the Federal Copyright Act. Candidates agree not to copy, reproduce, reconstruct by dictation or other means, or disclose examination content in any manner. Board Self-Evaluation Process (SEP) modules are also copyrighted works. Candidates agree not to copy, reproduce, or make any adaptations of the modules in any manner; or to assist someone else in the infringement of this or any Board-copyrighted work.

Professionally and financially unable to do otherwise, he completed his application and paid his $1,135 registration fee for the examination.

A short time later, he turned to his program director to inquire which board review course he should attend. He was recommended to attend the "Arora Board Review" course led by Dr. Rajender Arora MD. Others had gone there and given it good reviews. His Pennsylvania residency program thought highly enough of the Accreditation Council of Graduate Medical Education (ACGME) sanctioned course that they paid his $1000 registration fee. He decided to attend the board review course offered in June 2007 just before his scheduled board examination in August 2007.

The Board Review Course

Five hundred economically vulnerable residents were in attendance at the Arora Board Review course in June 2007.  The young doctor thought the course was taught well and helped him gain confidence for the exam questions he might encounter. Dr. Arora was a dynamic teacher and the examples and commentary he provided were helpful at teasing out the critical concepts for the examination. At the end of the course, it was mentioned that if he'd like, he could help "pay-it-forward" to his fellow colleagues by sending Dr. Arora information about the topics and questions he could recall that he encountered on his Board examination.

He studied hard for his examination for the next several months, rising early and staying up late and foregoing other social obligations. He reviewed his texts, journal articles, and board review materials. Then the day came for his examination.

He arrived at the test center, checked in, had his biometric palm scan recorded, deposited his wallet, car keys and mobile phone in a locker, was later searched, and finally admitted into the PearsonVue examination computer room. There beside him were others, pounding on their keyboards taking examinations for other trades. He sat and got comfortable. On his computer screen was a big ABIM logo with his name below and a set of instructions. Just before the timed test began, he read a document that threatened him if he shared content of the test. He had the choice: either click "I Decline" and be escorted out of the examination center and thereby waste his test preparation and potentially sacrifice his career as a physician or click the "I Accept" button to start his examination. He accepted and took his test, yet never received a copy of the agreement that he had just electronically "signed."

He thought he did well on his certifying examination. He remembered the general concepts of the questions and while he couldn't remember all of the questions and distractors, he was eager to share what he remembered of the test with the person who helped him prepare, Dr. Arora. After all, others likely did the same for him. He decided to communicate with Dr. Arora via e-mail to thank him for his help and share with him what he could recall as a way to "pay it forward" to others as requested.

Time passed. In late October, 2007 he received notification that he had passed his boards and felt relieved that he had at least secured himself the potential for gainful employment as a "Board certified"  internal medicine physician. He had no intention of repeating that ordeal, at least not in the immediate future. As life would have it, his medical passion had evolved to physical medicine and rehabilitation. His second child was born November 10, 2009 and because residency slots were tough to obtain, he moonlighted to bridge the gap before his second residency in his chosen field began.

On June 8, 2010, he received a sanction letter from the ABIM. In that letter the young doctor learned that the ABIM had suspended his certification for three years because they alleged that he had shared question content from memory with Dr. Arora in violation of the ABIM's "Pledge of Honesty." His board certification status was immediately revoked without due process.

His mind spun. "How in the world?... What happened?" His life, quite frankly, had gone from idyllic to uncertain in an instant. He couldn't sleep. He was humiliated and had to tell his wife. But one thing he was sure of: he didn't want to have to take the test again. Four years of medical school. Three years of residency. Night call. Sleepless nights. Finally, realizing the magnitude of what had happened to him and the possible lifelong ramifications, he retained a lawyer.

He spoke with his lawyer - someone he'd worked with earlier. She was sympathetic. So calls were made to the ABIM's lawyers. At first, ABIM lawyers were unyielding: it was a three-year sanction and then he had to retake the examination.

A short time later, his lawyer called him to tell him about this article that had appeared in the Wall Street Journal June 9, 2010. He was not the only one; there were 138 others. His penalty could have been worse, he was told. At least he wasn't formally sued but his privileges to practice medicine were temporarily suspended at one of his hospitals from 2010 through part of 2011 and compromised his ability to moonlight to pay for his children's daycare.

"I can't take that test again. I just started my residency!" he thought. After pleading with ABIM, the sanction was reduced from three years to one on July 28, 2010, but he appealed this decision since the financial and professional implications of even a one-year sanction were devastating.

Months later after more letters and were exchanged a plea "deal" was struck with the ABIM April 5, 2011 - the ABIM agreed to settle with the doctor for a $5000 fine along with 20 hours of community service in a medical-related charity and proof of completion of an ethics course.

What choice did he have but to agree to those terms?

Cancelled Check Paid to ABIM to Reinstate Board Certification*
(Click to enlarge)
Finally on 1 Sep 2011, the young physician's Board certification was reinstated but the scars linger. From now on, he must always explain that he was "sanctioned" by the ABIM when completing a hospital credentials' packet or being licensed by his state. Needless to say, he no longer practices in a hospital setting.

Commentary: In retrospect what this young doctor didn't realize at the time was that the Arora Board Review course was secretly recorded as part of an ABIM-sanctioned "investigation," apparently without law enforcement  oversight.  On the basis of that recording and evidence gathered by a undisclosed ABIM employee that secretly attended the review course, this "evidence" was presented before a federal judge by Christine Cassel, MD, Ms. Rebecca Baranowski, and A. Benjamin Mannes (the ABIM's currently employed "Director of Investigations" who carries two felony convictions (for impersonating a police officer and carrying an unregistered firearm) and has unfettered access to the ABIM diplomat's files and personal information). On the basis of that information, the ABIM was granted a writ to seize under seal after providing $10,000 in collateral so Federal Marshals could secretly invade Dr. Arora's residence with ABIM attorneys accompanying them. According to court documents, the ABIM obtained images of Dr. Arora's computers, hard drives, and 36 boxes of course materials. To the best of my knowledge and belief and on the basis of this ABIM "letter of concern," only after obtaining those computers did the ABIM discover the emails of who attended the Arora Board Review Course course and had communicated electronically with Dr. Arora.  The earlier communications with Dr. Arora were thought to be private and occurred without financial renumeration to either party of any kind. As such, it appears the raid was little more than a fishing expedition for physicians' emails and addresses who attended the board review course. It appears to me that because the young doctor's email to Dr. Arora was found on one of those computers, and he represented a vulnerable target, he was immediately sanctioned without due process. Dr. Arora, on the other hand, worked a separate settlement deal with the ABIM that has never been made public.

Same Course, Different Doctors, Different Sanctions

Another Arora Board Review sanctioned physician-attendee had a different penalty imposed.  Not only was this physician sanctioned for three years initially, this physician was later forced to sign an agreement with the ABIM that he had committed an ethical violation, had his upcoming subspecialty medical board examination cancelled, and was required to re-take his internal medicine certification examination. But this was not his most difficult problem.

After learning of the ABIM's sanction, his state licensure board also required the physician pass a "maintenance of certification" examination, take an ethics course with an "unconditional pass," do 50 hours of community service, pay a $1000 fine, and provide peer review references before state would re-issue this state license to practice medicine. His online credential verification still documents his sanction today. All of these actions did not include the legal expenses the physician incurred to defend himself with two separate state licensure boards (WA and TX) and the ABIM itself.

Ongoing Litigation

Some nine years after the June 2007 Arora Board Course, the ABIM has still not finished sanctioning physicians. Jaime Salas Rushford, MD, a Puerto Rican physician who attended the same Arora Board Review course, learned of his sanction by the ABIM on 8 May 2012. In his sanction letter, his certification was revoked indefinitely. Shortly thereafter, Salas Rushford also learned that he had been sued by the ABIM as well. What the ABIM had not anticipated was that Dr. Salas Rushford's parents are lawyers. They filed a counter-suit (begins on page 32). The case has been ongoing four years later and full details of the ABIM's operations and tactics are being systematically uncovered in documents on Dr. Salas Rushford's website, doctorsjustice.com. Millions of dollars in legal fees paid by physician diplomats continue to flow to the ABIM's legal team. Unfortunately for all US physicians, this story is far from over and will likely become, as described by the Pennsylvania Medical Society in their recent vote of no confidence (more here), "the most expensive medical mistake in the history of medical education."

Epilog

Given what we now know about the ABIM's long-standing tenuous financial condition, the "research" the ABIM performed and funded from these vulnerable diplomat's exam fees without true informed consent, the undisclosed lobbying that ABIM participated in as a non-profit outside of federal regulations, the years of fraudulent tax filings, the funneling of $55 million of ABIM diplomat fees to fund the ABIM Foundation that performed additional "research" and purchased a luxury condominiums for its use, it is hard to imagine the ABIM has physicians' or our patients' best interests in mind. Furthermore, the American Board of Medical Specialties' (ABMS) (who overseas all of the ABMS member boards, including the ABIM) earlier Senate testimony that claimed they are expanding "new kinds of (undisclosed) partnerships with public payers, private payers, and particular patients and consumer groups who represent them to get a deeper appreciation for the kinds of information they seek and their expectations for care..." with numerous undisclosed revenue streams, there is only one question to ask of these unaccountable cartel-like physician credentialing "non-profit" organizations now.

Did the ABIM act in the public's best interest by sanctioning the many vulnerable resident physicians who attended the Arora Board Review course or did they engage in extortion for the ABIM/ABMS's financial benefit as a result of the ABIM's financial largess using police-state tactics?

-Wes

“The arc of the moral universe is long, but it bends towards justice.”

― Martin Luther King Jr.

*The redacted canceled check and redacted documents above were all used with the ABIM diplomats' permission.

Wednesday, July 13, 2016

ABMS vs The Poor

The chilling reality of what is happening to patients when the ABMS changes the definition of what is required to be Board certified and ties it to Medicaid payments:
CMS officials disagree, saying in so many words that it's "unfortunate," but these Tennessee doctors skipped over the details on who, and what services, qualified for the additional pay.

First, CMS rules specified that Medicaid providers had to be board certified in internal medicine, family medicine or pediatrics. These doctors weren't, in part because in rural areas, hospitals often don't require board certification and, for older doctors, it wasn't a mandate after training.

Second, for doctors without board certification, their status as primary care providers could be documented if 60% of the codes they submitted in their claims were for a select set of primary care evaluation and management (E&M) or vaccination services, not specialty services.
So for those doubters out there that thought this "physician" Maintenance of Certification (MOC) discussion was a "physician issue" and did not pertain to patient care delivery, think again.

-Wes

Reference:

MedPageToday: Medicaid Boom Turns to Bust for Tennessee Docs - Lack of certification triggers payback requirement

Sunday, July 10, 2016

Too Little Too Late: The ABIM Foundation Sells Its Condo

It was a story that broke on this blog nearly two years ago when the American Board of Internal Medicine (ABIM) Foundation was putting their luxury condominium, complete with a chauffeur-driven Mercedes S-Class town car that was purchased with physician certification and re-certification fees, up for sale.

Over 550 days later, we find the notorious ABIM Foundation condominium was finally sold on 6/21/2016 for $1,650,000 representing an up-front cash loss of $650,000.

But let's not forget the other associated fees required to sell a condo:

Real estate commission (6%): ($99,000)
Transfer Tax as buyer (2%) (2007): $46,000
Transfer Tax as seller (2%) (2016): $33,000
Title insurance: $10,000
Other fees: deed preparation, attorney fees, recording fees, etc. $10,000.
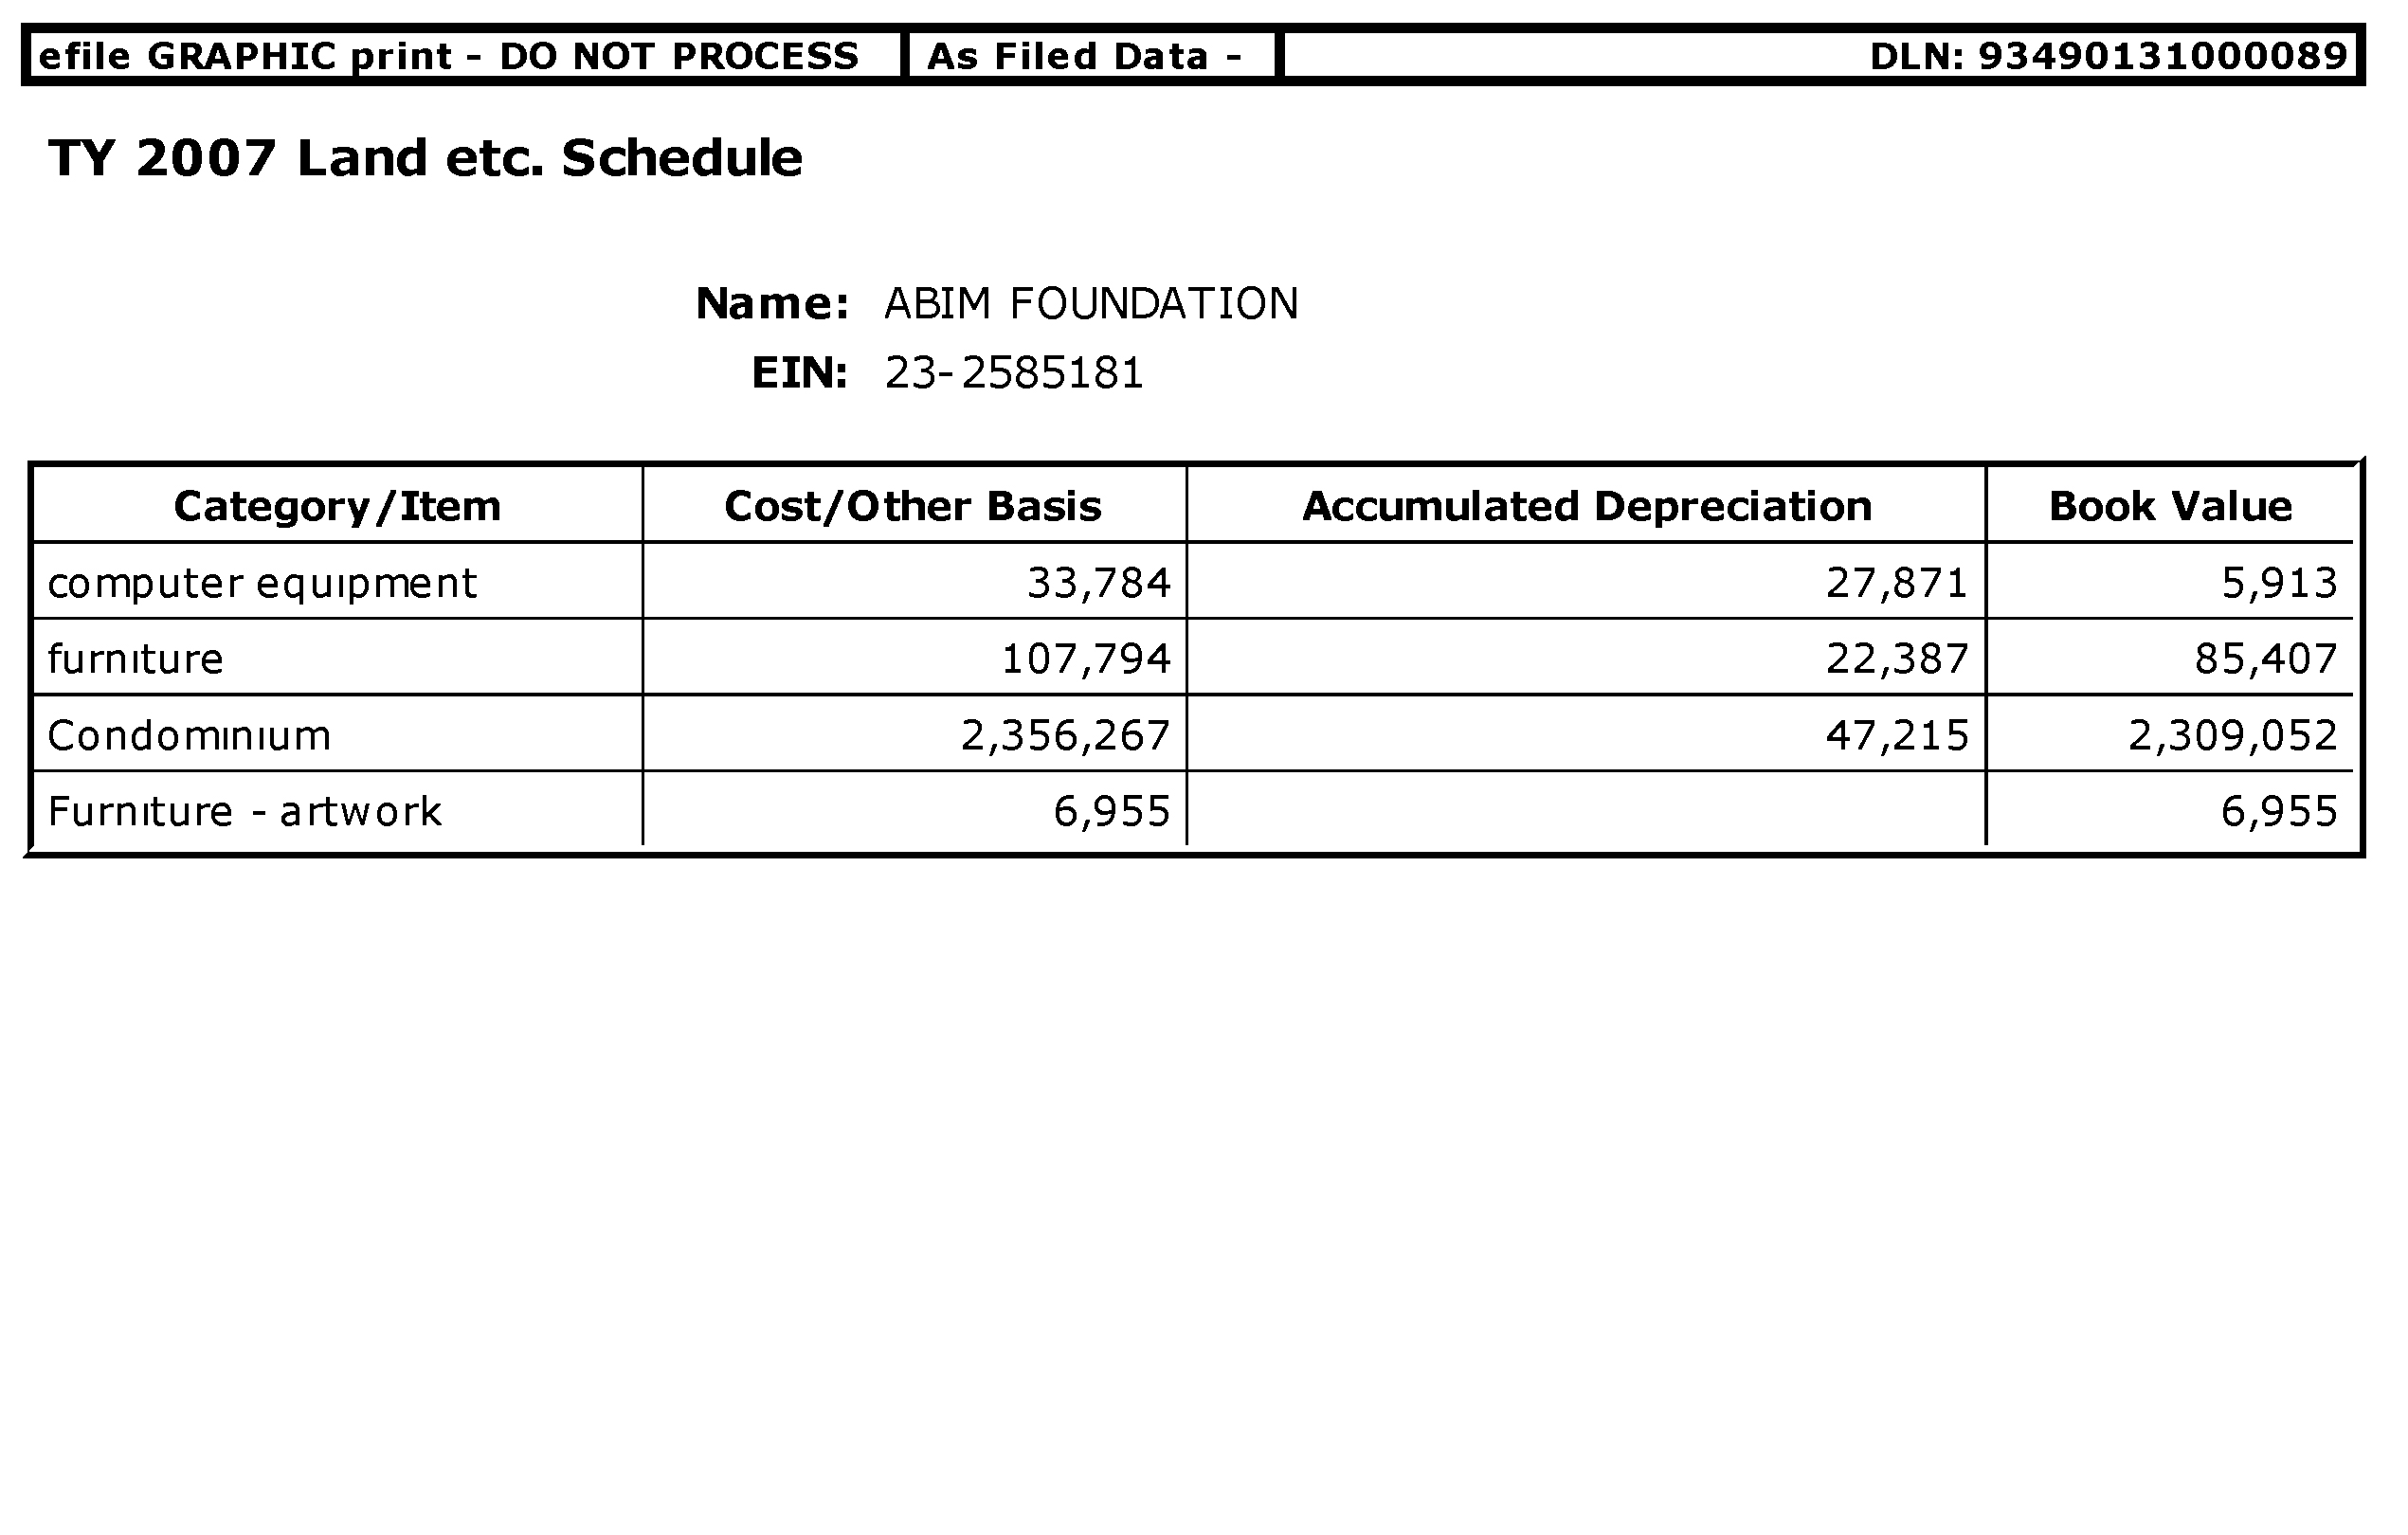
Furniture expense: $56,267


And then there's the annual condo fees, cable, phone, electric, cleaning, etc., that came to $41,000-$50,000 annually (approximately $450,000 over 9 years) (Source: Richard Baron, MD, President and CEO of the ABIM and ABIM Foundation)

All told, ABIM took $2,356,267 million of ABIM diplomat's cash and lost at least $1,265,267 on our behalf.

So much for "Choosing Wisely®."

But let's face it, incurring a financial loss on an "investment" is not necessarily illegal. After all, any of us could have made a horrible investment decision.  Rest assured we'll soon hear the ABIM trying to justify their real estate loss because they would have lost this money anyway if they had to pay hotel costs for all of their out-of-town guests and programmers from India eager for a cheap place to stay.

But we should ask ourselves now with the sale of this condominium, what was illegal at the ABIM Foundation? Anything?

Tax Fraud

First, recall that Dr. Baron claimed in my communications with him that much of the condominium expenses they claimed on their tax forms as program service expenses was actually a depreciation expense they lumped into the "program services expenses" of the condominium. Yet the ABIM and their accountants never claimed depreciation under the separate line item on their federal IRS Form 990 for this expense.

Honest mistake?

Unlikely. After all, other tax filing discrepancies with the ABIM Foundation have occurred repeatedly and systematically over many years. Any credible accounting audit should have disclosed most of them.

For instance, surely someone at the ABIM knew the difference between the two states of Iowa and Pennsylvania, didn't they? So why was the ABIM Foundation domicile claimed as Iowa for years when, in fact, it was domiciled in Pennsylvania but never disclosed? And isn't it striking that the ABIM Foundation was claimed for years as being formed in 1999 until this blog disclosed that it was actually created in 1989, some ten years earlier? Only in its most recent tax filings has that little "oversight" miraculously been corrected without explanation to the Internal Revenue Service.

And why didn't the ABIM disclose that it was lobbying Congress on its tax forms when it had been doing so for years? Was this merely a mistake? Or was it because the ABIM and their Foundation would have opened themselves up to closer scrutiny and lost their tax-exempt status if they had?

Unethical Research Practices

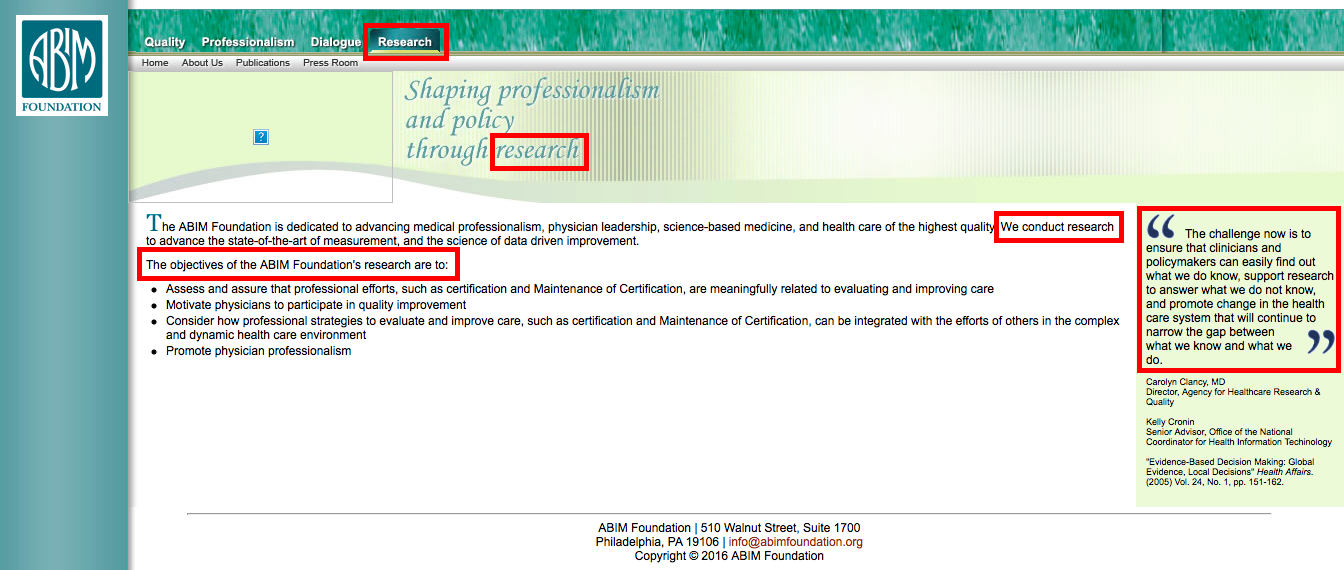
Finally, we have to ask ourselves just what kind of research on physicians for the betterment of health care requires a $2.3 million condominium? After all, the ABIM Foundation has always heavily touted their research work and publications.

Some may argue there wasn't "research" being conducted at the ABIM Foundation but rather "quality assurance" or "Quality Improvement" exercises performed there. If so, then why did the ABIM Foundation promote it's pioneering research by using the term at least five times on a single web page in May of 2007?

Archived Screen May 2007 - ABIM Foundation
(Click image to enlarge)
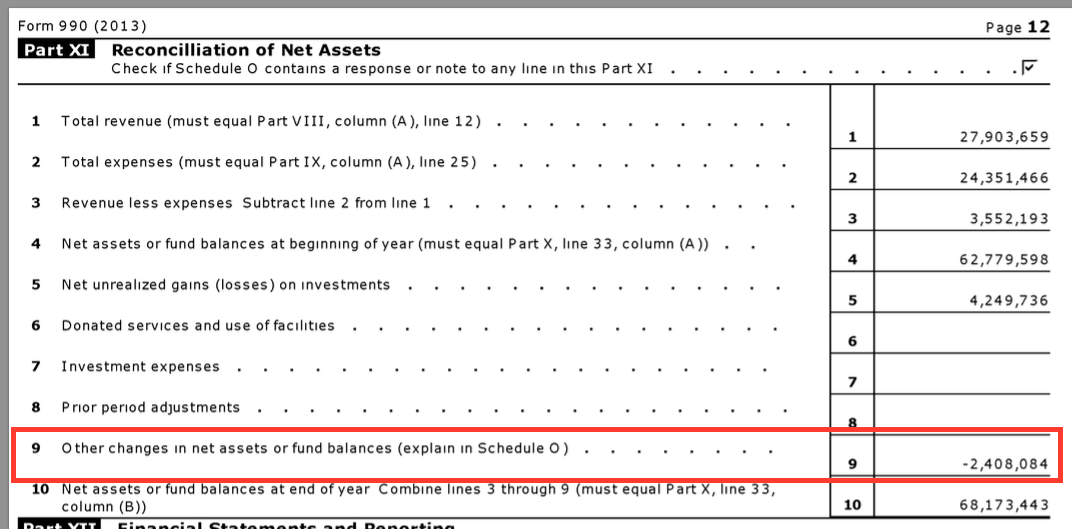
We also find that the ABIM funded "various research projects" at its Foundation in the fiscal year 2008 with the transfer of $6,000,000 of ABIM diplomat fees:

Evidence of ABIM Funding "research projects" at the ABIM Foundation
for $6 million in Fiscal Year 2008
(Click image to enlarge)

There is no escaping the fact that this was a very serious effort at conducting "research" on physicians.

Or not.

Was the whole "research" story told by the ABIM and ABIM Foundation just a front for other activities? I wish to bring my reader's attention that the ABIM Foundation no longer has the word "research" appear anywhere on its website. Instead, there are only words like "Medical Professionalism Charter," "Initiatives," "Grants" and "Choosing Wisely®." The cover-up continues.

Credentialing of physicians involves human testing. As such, it appears the ABIM Foundation unilaterally decided to perform research on physicians without informed consent, without an impartial Investigational Review Board, and without a clear research hypothesis, method, or analysis of the harms they might cause.

"Research" conducted in such a manner is dangerous for many reasons and some of the most egregious examples of dangerous research have happened in government agencies or when the individual or collective social beliefs or dogma were imposed on others as justification for "research."

The Nuremberg Doctrine which rose from the World War II war crimes is very clear in its requirements for human subject research, especially as it pertains to proper consent. From my recently conducted bi-annual CITI Training:
"The voluntary consent of the human subject is absolutely essential.

This means that the person involved should have the legal capacity to give consent; should be so situated as to be able to exercise free power of choice, without the intervention of any element of force, fraud, deceit, duress, over-reaching, or other ulterior form of constraint or coercion; and should have sufficient knowledge and comprehension of the elements the subject matter involved, as to enable him to make an understanding and enlightened decision. This latter element requires that, before the acceptance of an affirmative decision by the experimental subject, there should be made known to him the nature, duration, and purpose of the experiment; the method and means it is to be conducted; all inconveniences and hazards reasonably to be expected; and the effects upon his health or person, which may possibly come from his participation in the experiment.

The duty and responsibility for ascertaining the quality of the consent rests upon each individual who initiates, directs, or engages in the experiment. It is a personal duty and responsibility which may not be delegated to another with impunity."
It goes without saying that human subject research that involves real estate investment strategies to fund research on practicing physicians is unethical (at least) and likely highly illegal. As we have seen, the MOC recertification program can cause significant harm to physicians, their patients, and their families, especially when this credential is tied to physician employment and remuneration. Worse still, the average failure rate of the unproven "Maintenance of Certification" re-certification metric has averaged 13.2% over the past 10 years with wide year-to-year volatility in pass rates using an inconsistent metric. Was the impact of funneling money from the ABIM to the ABIM Foundation for the ABIM Foundation's "research" really that harmful?

Absolutely.

But this story isn't about a condominium or its sale, is it? It's about the wholesale sell-out by some in Organized Medicine that have systematically and repeatedly turned their back on their fellow practicing physicians and the doctor-patient relationship for their own political and financial benefit. For this story is not just restricted to the ABIM or its Foundation. This story extends to all member organizations of the Accreditation Council for Graduate Medical Education (ACGME) that tie the ABMS Board certification credential to medical training program directors, lab certifications, and a host of other regulatory traps, too. So it should come as a surprise to no one that we find more recently that each of these organizations appears to have been complicit with the ABIM Foundation moving funds derived from practicing physicians' "research" fees offshore.

In the end, the entire American Board of Medical Specialties' Maintenance of Certification® story has alway been about making money for their coffers at the expense of practicing physicians, irrespective of the specialty.

Always has been and always will be.

It's NEVER been about "Choosing Wisely®."

-Wes


Thursday, July 07, 2016

Pennsylvania Medical Society Spearheads Effort to End MOC Nationwide


Recently, the Pennsylvania Medical Society sent this letter to the executive vice presidents of all US state medical societies and many specialty societies regarding their vote of no confidence regarding the ABMS Maintenance of Certification® (MOC®) program and the current leadership at ABIM, stating specifically:

"... We believe that their current leadership is not capable of reforming the process in a timely, academically meaningful, and fiscally responsible way.

In keeping with the consensus of our members and physicians across the country, we call for the immediate replacement of the entire ABIM Board of Directors and leadership with new leadership, representative of physicians actively participating in the full-time practice of clinical medicine. The undersigned organizations would further offer to assist the ABIM and any of the ABIM subspecialties with the formation and transition to a new Board that is representative of and accountable to the physicians whom they will certify. ..."
For those interested in learning more or who's state is ready to sign on can email Dr. Scott Shapiro, President of the PA Medical Society at stat@pamedsoc.org‎ for more information.

Please forward a copy of this letter to all of your practicing physician colleagues (irrespective of specialty) and ask each of them to contact the leadership of their respective state medical societies and specialty societies to urge them to co-sign this letter and work with the PA Medical Society to end the corrupt ABMS MOC® re-certification requirement.

Only through aggressive, meaningful, nationwide collective action against this needless, unaccountable, expensive, and coercive ABMS re-certification program will practicing physicians restore sanity to our own life-long continuing medical education process.

Thank you-

-Wes

A copy of the letter to circulate to your colleagues can be downloaded here.

Wednesday, July 06, 2016

An Upcoming ABIM "Community Exploration" Day in Chicago!

(Click image to enlarge)

I just received the notice above in my inbox at work. It seems there's going to be an "ABIM Exploration Day" here in Chicago 26 August 2016. I requested an invitation but have a feeling I won't be sent one since I disclosed I was one of the ABIM's foremost critics of the ABIM MOC program. (That's right, you have to request an invitation at the link provided in this email blast)

Let's make this like open microphone night and feel free to leave your questions for the ABIM in the comments section on this blog. That way, no matter who goes to this hosted event, they'll have plenty of "exploration" questions to ask Yul Enjes, MD and Richard Baron, MD or their representatives. (Physicians are encouraged to identify themselves (and their ABIM diplomat number) so the ABIM knows you're real).

-Wes

Saturday, July 02, 2016

The ABMS MOC Contagion Spreads

It seems the humiliation of physicians to collect revenues by member boards of the American Board of Medical Specialties (ABMS) Maintenance of Certification (MOC) program knows no bounds.

This time, we begin our focus on the American Board of Pediatrics (ABP).

First, take a moment to read what happened to a younger physician mother-of-three who tried to re-certify in pediatrics when her child was 9 months old and still breast feeding.  Horrible.

Pediatricians are one of the lowest paid medical specialties in medicine. Yet like all US physicians, the must pay thousands to "re-certify" with the American Board of Pediatrics every 10 years.

And why must they pay such high fees?

Perhaps there's no better example than James A. Stockman, III, MD.

Dr. Stockman worked for the ABP for 20 years, retiring 31 Dec 2012.

Dr. James A Stockman III, MD Retires from ABP 31 Dec 2012
(Click image to enlarge)

As part of that retirement, we see the ABP paid him over $2.4 million:

(Click to enlarge)

(Click to enlarge)

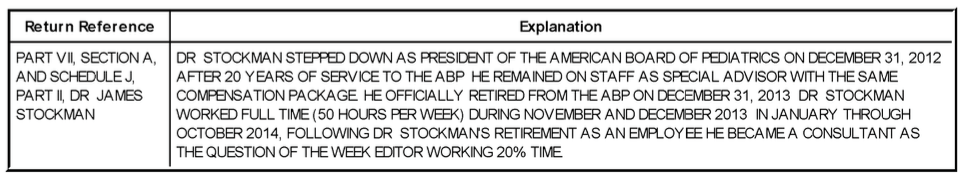
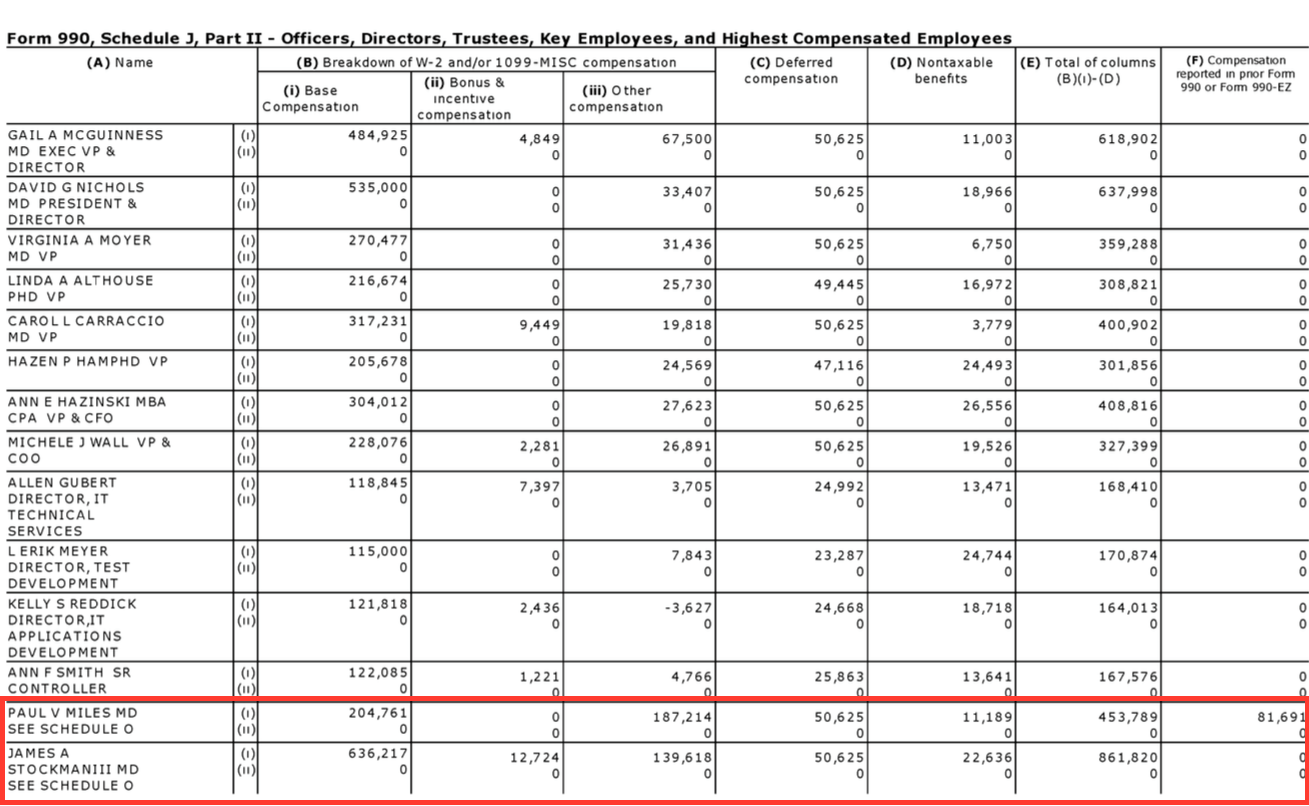
But this, you see, wasn't enough. Despite often earning over a million dollars a year prior to his retirement while working for the ABP, and then making a $2.4 million golden parachute on his retirement, Dr. Stockman stayed on as a "consultant" for the ABP. His first year there, he earned a cool $861,820 working 45-50 hours a week.
(Click image to enlarge)


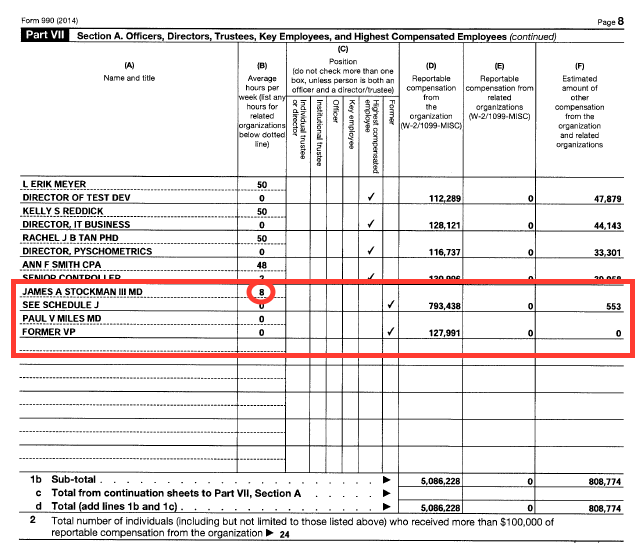
But the next year was even better. On their most recent 2014 Form 990, we see that Dr. Stockman earned $793,438 for working just eight hours a work-week:
(Click image to enlarge)

If we assume there are 48 work weeks in a year and Dr. Stockman works just eight hours a week for a total of 384 hours, then in 2014 Dr. Stockman earned a whopping $2066.24 per hour.

I think it's time pediatricians join internists and cry foul loud and clear.

The ABMS Maintenance of Certification extortion of US physicians has to go.

-Wes

Friday, July 01, 2016

One Small Step

Here's the official final wording of the AMA House of Delegates' Resolution 309, Continuing Medical Education Pathway for Recertification adopted June 15, 2016:
Resolution 309, Continuing Medical Education Pathway for Recertification, was adopted as amended. The final recommendations are as follows:

RESOLVED, That our American Medical Association call for the immediate end of any mandatory, secured recertifying examination by the American Board of Medical Specialties (ABMS) or other certifying organizations as part of the recertification process for all those specialties that still require a secure, high-stakes recertification examination; and be it further

RESOLVED, That our AMA support a recertification process based on high quality, appropriate Continuing Medical Education (CME) material directed by the AMA recognized specialty societies covering the physician’s practice area, in cooperation with other willing stakeholders, that would be completed on a regular basis as determined by the individual medical specialty, to ensure lifelong learning; and be it further

RESOLVED, That our AMA reaffirm Policies H-275.924 and D-275.954 (Author's note: use the AMA Policy Finder to review these policies); and be it further

RESOLVED, That our AMA continue to work with the American Board of Medical Specialties (ABMS) to encourage the development by and the sharing between specialty boards of alternative ways to assess medical knowledge other than by a secure exam; and be it further

RESOLVED, That our AMA continue to support the requirement of Continuing Medical Education (CME) and ongoing, quality assessments of physicians, where such CME is proven to be cost-effective and shown by evidence to improve quality of care for patients.

-Wes

ACGME Announces New Affiliation with ABMS

PRNewswire - (Chicago) July 1, 2016 - Today, the Accreditation Council of Graduate Medical Education (ACGME) announced a new affiliation with the American Board of Medical Stenographers (ABMS), promising new efficiencies and reduced medical transcription errors within the Electronic Medical Record (EMR). "Ever since the Institute of Medicine's (IOM) 1999 report entitled "To Err is Human" that claimed as many as 98,000 patient deaths as a result of medical errors, we've been looking for ways to reduce medical errors in today's hospitals and clinics," said Joseph Throckmorton, MD, President and CEO of the ACGME. "The public has been asking for a way to certify all US physician's typing skills to assure the highest standards of patient care quality and safety," he said.

As part of this program, the ABMS has instituted a Maintenance of Typical Skills® (MOTS®) program using a simple online typing test performed each month in the convenience of the physician's own home or via his or her mobile device. Test scores will be verified and uploaded to the ABMS CertificationMatters website for public review. The cost for physicians will be nominal - only $25 per month. Typing speed and error toleranance levels will be determined by the Board and subject to change. Physicians who fail the test can retake it twice before they must re-register to maintain their credential. A Pledge of Honesty is required of all participants.

"The importance of such a credential comes at a time when self-regulation of our profession is more important than ever," said Imso Boring, MD, JD, President and CEO of the ABMS. "We're proud we could play a part in the harmonization of this important patient care metric with other critical patient care quality and safety initiatives promoted by the ACGME."

Existing members of the ACGME include the American Board of Medical Specialties, the American Medical Association, the American Hospital Association, the Association of American Medical Colleges, the Council of Medical Specialty Socities, the American Osteopathic Association, and the American Association of Colleges of Osteopathic Medicine.

It is currently estimated that EMR typographical errors are the third leading cause of death in the United States.

* * *
 
Hope all my faithful readers have a happy and healthy 4th of July.
 
-Wes

Wednesday, June 29, 2016

On Brexit and Maintenance of Certification

The degree to which this was a vote that was directed against the British elite is vital to understand. Politicians, business leaders, and intellectuals were all seen as having lost their right to control the system. The elites had contempt for their values - for the nationalism and their interests. This is not a new phenomenon in Europe, but it is one that the EU had thought it had banished. This is not a British phenomenon by any means. This is something that is sweeping Europe and China. It is also present in the U.S., in the figure of Donald Trump, whose entire strategy is to attack the Democratic and Republican leadership and the elite who have contempt for the nationalism and moral principles of those beneath them. It is the general process the West is undergoing, and it came to London (Thursday).

George Friedman, Geopolitical Futures

Could what has happened in London parallel what is simultaneously happening to Organized Medicine in the United States? Cracks have formed in the foundation that American physicians have trusted for years: the Accreditation Council on Graduate Medical Education (ACGME), the American Board of Medical Specialties' (ABMS), American Board of Internal Medicine, the American Medial Association, and our many of our specialty societies. Practicing physicians are looking with a new lens at "politicians, business leaders and intellectuals" who were once trusted to protect the practice of medicine and the physician-patient relationship.

Can our current byzantine system of unelected, unaccountable, non-profit health care organizations "lose their right to control" our health care system - a roughly $3.0 trillion dollar sector or 17% segment of the entire US gross national product? Will they endure under this new level of scrutiny and demand for transparency from those on the front line of health care delivery? How will these structures pivot?

How much tax fraud must occur, how many laws must be broken, how many physician personal liberties must be tossed aside before practicing physicians and their patients demand change?

You can feel the ground shaking.

The silence is deafening.

-Wes

Friday, June 24, 2016

Heart Rhythm Society Waffles on MOC

On Thursday (yesterday), I received this notice from the Heart Rhythm Society (HRS) concerning their stance on the American Board of Medical Specialty's (ABMS) Maintenance of Certification (MOC) referendum at the recent AMA House of Delegates meeting held in Chicago:
"The American Medical Association (AMA) House of Delegates recently approved resolutions addressing concerns about the American Board of Medical Specialties' (ABMS) MOC program at its annual meeting.

The resolutions are consistent with the HRS concerns and commitment to advocate for changes to the Maintenance of Certification (MOC) program. HRS currently has a representative in the AMA House of Delegates. To ensure that HRS maintains its seat at the AMA House of Delegates, the Society must demonstrate that 20 percent of the Society’s U.S. physician members are also members of the AMA.

The AMA also approved the commissioning of a study that will evaluate the impact of MOC and Maintenance of Licensure requirements on physicians. This study addresses the heart of the debate and HRS looks forward to the results of this important study."
I found this notice puzzling.

While the Heart Rhythm Society states the resolutions "are consistent with the HRS concerns and commitment for changes to the MOC program," it appears they do not understand that the House of Delegates overwhemingly resolved to end Maintenence of Certification immediately:
"RESOLVED, That our American Medical Association call for the immediate end of any mandatory, secured recertifying examination by the American Board of Medical Specialties (ABMS) or other certifying organizations as part of the recertification process for all those specialties that still require a secure, high-stakes recertification examination."
This does not mean changing the ABMS MOC program, it means ending it.

This does not mean studying the ABMS MOC program, it means ending it.

And this certainly does not mean supporting the AMA with our dues when they fail to act in the practicing physicians' best interests either.

Look, it is now abundantly clear that the ABIM did many, many illegal and self-serving activities with our diplomat fees for (at least) the past 27 years. And when they were caught red-handed with their hand lodged in the practicing physician's personal liberty and financial cookie jar, they tried (and continue to try) to cover it up. What they've done is illegal in many fronts. This is not acceptable and none of us need to "change" MOC or perform "another study" on MOC (funded by our dues) to sweep these actions under the rug. MOC just needs to end immediately.

I worry that the HRS leadership doesn't understand how angry practicing physicians are about what has transpired behind our backs as we've struggled to do the yeoman's work of patient care.

Here's the deal:  if the HRS wants my dues for another year going forward, move to end MOC now. Put your actions where our money is. Otherwise, I'll save my hard-earned assets for other things besides supporting groups who don't support those of us on the front line of health care who obey the law and prefer to manage our profession ethically and transparently, rather than through political channels using threats and intimidation as their modus operandi.

-Wes

Wednesday, June 22, 2016

ABIM's Bedfellows

Right now, the Center for Medicare and Medicaid Services (CMS) has a comment period that extends through 27 Jun 2016 regarding MACRA, the new payment scheme created by the health care industry, to pay physicians on the front line of health care. I encourage every physicians to voice their  opinion about this plan,

Before you do, however, I'd like to remind you of the recent indifference by the AMA regarding the House of Delegates overwhelming vote to end Maintenance of Certification last Monday.  Needless to say, there's a reason why.

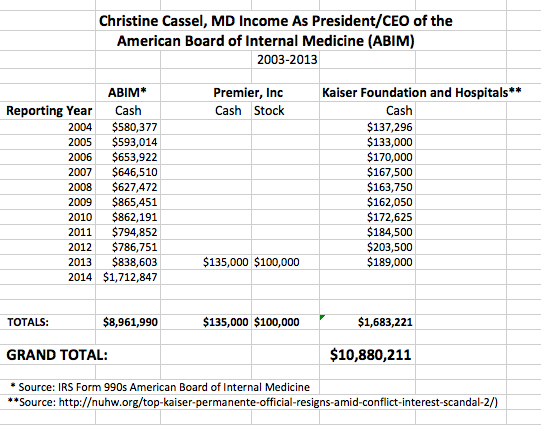
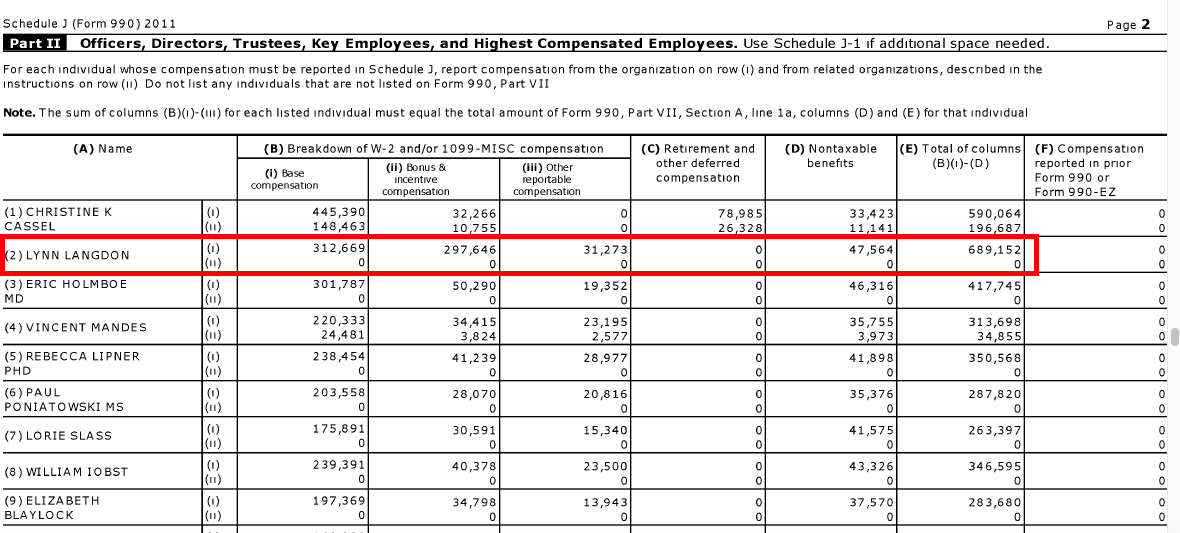
Remember those conflicts of interest with Christine Cassel, MD, former President and CEO of the American Board of Internal Medicine (ABIM) and, later, the National Quality Forum, the ABIM, and ABMS?  Remember the huge splash the announcement of those conflicts had when her conflicts were disclosed by Propublica, and Dr. Cassel quickly relinquished her ties to Premier and Kaiser Health Plan and Hospitals? Remember how Christine Cassel, MD pocketed a cool $230,000 ($100,000 of which was in Premier securities) just before Premier, Inc purchased CECity for $400 million?

Here's the image on the front page of the CECity website:

(Click to enlarge)
Look at all of the friends of the ABIM who welcome CECity's services: Johns Hopkins Medicine, the American Osteopathic Association (AOA), Merck, the American Medical Association (AMA), Aetna, The American College of Physicians (ACP), Premier, the ABIM, NextGen, Athenahealth, and Optum. These are just a few of ABIM's corporate bedfellows. The AMA has no interest in what doctors really want or need.  The AMA has no interest in ethics or what's best for patients.

The AMA and the ABIM only have interest in what's best for the AMA and the ABIM.

This is why the ABIM wants physicians to do Maintenance of Certification and enter all their demographic and survey data into the ABIM's database. It has nothing to do with maintaining physician skills but has everything to do with medicine's new digital party.

This is why physicians must act collectively to stop the tax fraud, violations of research ethics, and abuse of our civil rights that has occurred at the ABIM and the ABMS. Because like it or not, you're paying to have your right to practice medicine independently corrupted by these organizations that stand to earn billions from your work while being simultaneously coerced into paying ABIM's fees.

-Wes


Monday, June 20, 2016

Pennsylvania Medical Society Explains Their Vote of No Confidence Against the ABIM

The Pennsylvania Medical Society just sent this letter to all Pennsylvania physicians explaining their rationale for issuing a "vote of no confidence" against the American Board of Internal Medicine (ABIM):
The Pennsylvania Medical Society (PAMED) believes that continual professional development, lifelong learning, and providing quality patient care based on the best science and evidence to guide medical decision-making is the fundamental cornerstone of what it means to be a physician.

For two years, PAMED leadership has had numerous meetings with senior management at the American Board of Internal Medicine (ABIM) with the purpose of representing our members' high levels of dissatisfaction with the ABIM Maintenance of Certification (MOC) program. Early in this process, we concluded that the reason ABIM leadership was so out of touch with practicing physicians was because nearly every member of the ABIM's board is not involved in the full-time practice of seeing patients. We attempted to work collaboratively with ABIM's leadership to help them better understand that their punitive process is needlessly time-consuming and takes physicians away from their patients. We demonstrated to them that their process is exorbitantly and unnecessarily expensive compared to other continuing medical education activities through which medical knowledge and excellence in patient care can be maintained and demonstrated. Most importantly, we clearly expressed to the ABIM that the content and available medical resources of their secure, high-stakes computer exams bear little to no relevance to the care we render to our patients in our offices and hospitals.

Through their marketing efforts, the ABIM has worked hard to give the impression that their recertification exam demonstrates competency. However, despite numerous calls to substantiate this assertion, the ABIM has been unable to provide reliable independent evidence that a secure, high-stakes exam—taken every 10 years by some and for which others are "grandfathered" and therefore exempt—leads to better patient care. This is because while the overwhelming majority of practicing physicians pass the ABIM recertification secure, high-stakes computer exams, this test and the MOC process have no correlation to how well a doctor can take care of a patient. Shockingly, countless medical leaders, numerous national mainstream publications, and several forensic accounting reviews have published information which suggests that the ABIM's motivation for their recertification process was primarily driven by little more than financial mismanagement.

If true, what makes these actions so deplorable to physicians is that it was perpetuated on all of us by our colleagues whom we mistakenly believed were part of our medical family. In response to the overwhelming pressure being placed on their leadership, the ABIM has begun a public relations campaign with a barrage of emails and blog posts to create an illusion that they have the ability and the desire to correct this problem. As our PAMED Board reviews these emails, we believe that the ABIM's motivation and ultimate program will continue to have as their cornerstone the creation of as financially lucrative a position as possible for their Board and their misguided foundation.

It is for all of these reasons that I announced at the American Medical Association's (AMA) Annual Meeting last week in Chicago that the Board of the Pennsylvania Medical Society has voted a position of NO CONFIDENCE in the leadership of the Board of the American Board of Internal Medicine. We believe that their current leadership is not capable of reforming the process in an academically meaningful and fiscally responsible way. ABIM leadership has issued an apology for instituting their January 2014 MOC program. The ABIM has admitted that all three aspects of the program were improperly designed and deeply flawed. Millions of dollars were spent by the ABIM in preparation for this program. It can be argued that the January 2014 MOC program was the most expensive mistake in the history of medical education.

In keeping with the consensus of PAMED members and physicians across the country who are embittered with the practices of ABIM, we call for the immediate replacement of the entire ABIM Board and leadership with new leadership, representative of physicians actively participating in the full-time practice of clinical medicine. In the absence of this happening in a timely manner, we plan on calling on ALL specialty boards and societies to listen to their members and to work to remove the MOC process from ABIM oversight. Our PAMED Board is committed to aggressively advocating for all physicians on this important issue. We hope to see more meaningful progress in the coming weeks. We will explore every avenue to bring about meaningful MOC reform and will plan on keeping all PAMED members informed on any progress made in our efforts. Most sincerely,

Scott Shapiro, MD, FACC, FCPP
PAMED President
I hope other state medical societies across the country issue similar statements in the weeks ahead.

-Wes

Saturday, June 18, 2016

Video: The Gory Details of ABIM Maintenance of Certification

The Pennsylvania Medical Society posted the presentations made at the AMA House of Delegates Meeting at the Hyatt Regency Chicago on 13 Jun 2016 this morning (please see that link for all of the presentations made).

I post just two of those presentations here for your review.  First, the finances of the ABIM and ABIM Foundation that prompted the creation of Maintenance of Certification, as told by certified public accountant, Charles P. Kroll (27 min) (Slides here):


Next, my presentation on how Maintenance of Certification has affected practicing US physicians and their patients (22 min) (slides here):


Spend some time to review these videos and and inform yourself when you get a chance. Then work with your state medical societies and hospitals to end this onerous and corrupt physician program.

-Wes

It's Time to End the MOC® Brand

After Monday's resounding AMA resolution calling for an end to Maintenance of Certification®, it is time to end, once and for all, the MOC® brand held by the American Board of Medical Specialties (ABMS).

Maintenance of Certification® remains as a failed social justice experiment foisted on unsuspecting and vulnerable practicing US physicians by the American Board of Internal Medicine (ABIM) and the ABMS solely for the dual purposes of financial and political gain. Multiple studies have demonstrated MOC's inability to improve patient care or quality while wasting valuable time and physicians resources to fund this illegal experimentation.  After secretly lifting at least $55 million in diplomate fees to form the ABIM Foundation, MOC® has become the poster child for financial malfeasance, corporate cronyism, conflicts of interest, and fraud.  In all my years of practicing medicine, I have never seen such an egregious violation of medical ethics levied on practicing physicians by some of our own.

Yet MOC lives on in the hearts and minds of the AMA and affiliates of the Accreditation Council for Graduate Medical Education (ACGME). From the AMA press release after Monday's passage of the anti-MOC® resolution, it seems the AMA still thinks MOC® is a good idea:
Asking the American Board of Medical Specialties to encourage its member boards to review their MOC policies regarding the requirements for maintaining underlying primary or initial specialty board certification in addition to subspecialty board certification to allow physicians the option to focus on MOC activities most relevant to their practices
At the same time in an apparent attempt to render MOC® life support, the Accreditation Council for Continuing Medical Education (ACCME) has recently begun co-branding CME with MOC®.  They've even produced a new logo (they call it a "badge" - seen above) for sympathetic training organizations and medical schools to download. It all amounts to brainwashing our youngest and most vulnerable physician professionals that the behavior demonstrated by the ABIM and the ABMS should not only be condoned but promoted.

Practicing physicians have spoken loud and clear about their feelings about the ABMS/ABIM MOC® program.  It's time to end it, all of it, and expunge this horror story from the practice of medicine.

-Wes

Tuesday, June 14, 2016

AMA House of Delegates MOC Session Recap

It was a beautiful day in Chicago yesterday: sunny, not too humid. I left home early. The sun had risen some time ago and could be seen reflecting off the lake to the front of the downtown skyscrapers highlighting every detail of their construction. Lake Shore Drive is magnificent this time of day. I parked, as many must do each day, down in the basement of a nearby parking garage, making the "early bird special" parking fee of $16 when your arrive before 8 AM.

Nice.

(Click to enlarge)
I entered the Hyatt and saw a large meeting room across the foyer with a "Southeastern Delegate Meeting" sign outside the huge room. Lots of people with the representative state name on a card in front of them and a man in a bright kelly green jacket sitting next to the speaker stand who looked like a preppy leprechaun: the "Vice Chair." Heh.

I had to find registration at the Hyatt Regency Chicago: no easy task for someone who's never attended the AMA House of Delegates meeting, but approached what must have been a senior delegate adorned with his AMA badge with multi-colored tags draped some 14" beneath it highlighted by political stickers and little metal badges (I learned later you got some of these after contributing to various political action committees). He was cordial and helped direct me to the subterranean registration desk in the East Tower.

There were delightful ladies more than willing to help. "Are you a delegate?" they asked. "No, just a speaker." They gave me a registration card and I filled it out and was promptly handed a badge of my own with a lonely gray "speaker" badge dangling below.

"Don't listen to a thing he says, he's a doctor," someone said behind me. I turned around to find Charles Kroll, who has also just arrived, waiting to register.  I hadn't seen him for two years since we started to work together on the ABIM story. He grabbed his badge and we headed upstairs. I called David Winchester, MD, a delightful young cardiologist that I was introduced to via Twitter  (cardiologist and Florida delegate) and he joined me and Mr. Kroll for coffee.

AMA House of Delegates MOC Meeting
(Click to enlarge)
Next, I called Charles Cutler, MD from the Pennsylvania Medical Society who met us in the lobby of the East Tower. We headed to the meeting room and he introduced me to numerous people: Steven E. Weinberger, MD of the American College of Physicians (Executive VP and Chief Executive of the ACP), Stephen R. Permut, MD, JD, (Chair of the Board of Trustees of the AMA), and newly-elected Board Member of the American Board of Internal Medicine (ABIM), Yul Enjes, MD, among others. Only later did I realize Lois Margaret Nora, MD, President, and Chairman of the American Board of Medical Specialties (ABMS) was there, too, among many others (seated in the back, far right). Many stood in the back of the room despite available chairs in the front of the room (some things never change).

As luck would have it just before we began, the projector bulb blew shortly after it was turned on so another projector had to be retrieved. Meanwhile, the videographer had set up and was ready to go, but we had to remain seated as we spoke to use the available microphones. Once the new projector was secured, we were ready to begin.

Mr. Kroll went first (slides at link, video here) and explained his background as a forensic accountant specializing in health care and non-profits to the audience. He began discussing his educational background, credentials, prior experience with other non-profit shenannigans in Minnesota (Alina/Medica scandal) and his experience working with the attorney general there. He then explained how he stumbled across the ABIM story (a former article by Linda Girgis, MD asking if ABIM was "extorting" physicians). He pulled the ABIM's financials and immediately found discrepancies and outlined many of his findings to the audience. You could see heads shaking with disbelief. He kept it simple and understandable.  It was devastating. He then told the story how he contacted a mainstream media outlet who requested the last twelve years of audited financials from the ABIM and how the ABIM refused to produce all but the last year, and only if they met in persons to review them together. Evidently, the reporter politely declined and then requested these financials from the PA Attorney's Office (who never responded).  Only after a request was made to the press secretary of the PA Governor's office were the last two years' of audited financials produced. Mr. Kroll, who had these full financials in his possession, then noted that when the ABIM published them, they failed to publish six key parts of those financials on its website. Only after he disclosed this fact in an article in MedCityNews, did the ABIM recant and post the full financials. Finally, we concluded with a description of the meeting he help with the Iowa Attorney General's office and the recommendations he made regarding actions the Iowa AG could impose on the ABIM and their Foundation.

I was next.

In my presentation (a rather large Powerpoint presentation can be downloaded here, video here), I discussed my background, the background of how Board certification, how the philosophy of lifetime certification morphed to time-limited based on the ABIM's assertion that older physicians lost their skills over time, but then pointed to the paradox of the "grandfathering" of physicians and the inherent age discrimination against our most vulnerable physicians with that policy change. I also explained patient's definition of the excellent physician vs the ABIM's definition, and reviewed the costs in terms of out-of pocket costs and time involved (detracting from patient care). I also touched on the creation of the ABIM Foundation and the transfer of funds from the ABIM to the Foundation for "research" and showed the webpage asking for physician data for more "research" without informed consent and disclosure to physicians who were serving as study subjects in violation of the Belmont Report. With the purchase of the ABIM condominium, perhaps they were performing investment research instead, I suggested. I then summarized much of what has transpired with the ABIM and asked the important question, "How did it get this way?" and why I thought it happened. Finally, I summarized the disturbing code of silence that has surrounded the ABIM controversy by using the "Little Red Hen" allegory. The only people who will fix this mess is practicing physicians, starting with a full investigation of the responsible parties.

Next up was Bonnie Weiner, MD, board member of the National Board of Physicians and Surgeons (NBPAS.org) who gave an update of their efforts to create a more credible board credential for assuring continuing medical education. She expressed concern that future modifications to MOC will result in making one wasteful test taken once every ten years into many worthless tests over the same time period. She summarized the philosophy and finances of the NBPAS.org and explained that she could no longer serve as an interventional cardiology program director because she refused to perform MOC for that credential. (So much for "voluntary" certification!) She noted over 30 hospitals now accept NBPAS as an alternative to NBPAS.org and emphasized the need to have competition in the credentialing market.

With the last presentation by Scott Shapiro, MD, President of the Pennsylvania Medical Society, a shot was fired across the bow of the ABIM. Dr. Shapiro announced that the PA Medical Society was publicly announcing  their "vote of no confidence" against the ABIM and approved funds to evaluate legal options against the ABIM:
Today, at the AMA Annual Meeting in Chicago, our Pennsylvania Medical Society Delegation convened a national discussion panel to present their research findings, insights, and recommendations regarding the failures of the American Board of Internal Medicine and the MOC process. The discussion regarding the actions, finances and possible historical motivations for the ABIM actions was eye-opening and alarming.

Notably, during the conference, we announced that our PAMED Board of Trustees—after reviewing the available data and recent ABIM actions—voted and are now issuing a statement of no confidence in the ABIM's Board and leadership.

We also announced that, earlier this year, our PAMED Board approved the necessary funding to move forward with obtaining a legal opinion into whether PAMED would have standing to file a lawsuit against the ABIM. We hired a firm and recently received their opinion that not only would we have standing but they found potential legal claims consistent with our concerns that could be filed in a lawsuit against the ABIM.

Physician leaders from many other states have inquired about how their state can join PAMED's efforts. We look forward to these and other strategic conversations in the near future.
Boom.

You could have heard a pin drop.

After his announcements (and I probably missed a few key words), the floor was open for question and answer. Lots of people asked questions respectfully. Many were in support. Some were disappointed that there was not a more broad perspective of the opposite arguments for MOC on the panel. One physician with lots of tags on his chest approach the microphone saying," I learned a lot today in this session. Most of all I learned that I'm really glad I never became an internist." (He was an anesthesiologist). The room burst into laughter. He then went on to express his like of anesthesia's "MOCA minute" initiative but never disclosed if he had conflicts with the program or how much it cost. (By now, Dr. Nora from the ABMS had joined the question and answer line.)

It had to be difficult for Dr. Nora to enter this room, but I respected the fact that she came to the microphone to point out her views.  Unfortunately, rather than mentioning anything about the corruption we had just uncovered, Dr. Nora seemed upset that I had been inaccurate with my portrayal of where the ABMS gets their money (I am paraphrasing here). She also commented that we have been given a privilege to self-regulate and that we should consider carefully what we are doing. I then asked her a question as she walked away. She turned to answer. My question was this: "Have you ever studied what happens the physicians that you fail and what happens to their patients in turn?"  She stated she didn't "understand" my question and then proceeded to redirect to another topic before turning to walk away. Perhaps there will be an audio feed soon of this interaction. It wasn't one of our chief regulator's best moments.

Other questions kept coming, with many shifting to "what's next?"  Unfortunately the session went 30 minutes over and another meeting needed the room.

Finally, it was over.

I would like to take this moment to thank Charles Cutler, MD of the Pennsylvania Medical Society for his invitation to speak in this important venue. I am glad I could meet the players in this saga firsthand. There's no excuse for delaying any longer. Everyone knows the problems. Illegal stuff has occurred.

I can only hope those responsible take meaningful and serious steps to resolve the financial malfeasance, corruption, cronyism, and lack of accountability that has been ongoing at the ABIM (and other affiliated member boards of the ABMS hierarchy) for so long.  Otherwise, it's going to get very ugly very quickly.

Practicing physicians across the US have had enough of the ABMS MOC requirement shenanigans.

-Wes

AHA House of Delegates MOC Session Speakers, June 13, 2016
(L to R: Scott Shapiro, MD, Bonnie Weiner, MD, Charles Cutler, MD,
Wes Fisher, MD, and Mr. Charles P. Kroll)

P.S.: I will post a link to the videos of the sessions as soon as they become available. (Update: links added where appropriate above)


Monday, June 13, 2016

Dr. Wes Speaks At the AMA House of Delegates Meeting on MOC

This morning I will be speaking at the AMA House of Delegates Meeting in downtown Chicago at the Hyatt Regency Hotel, 151 Upper East Wacker Drive, Columbus Room E-F at 09:00 AM CST to encourage the abandonment of ABMS MOC re-certification for other alternatives.

For those unable to make the talk, you can download the full Powerpoint presentation here.

-Wes

Thursday, June 09, 2016

Maintenance of Certification: Medicine's House of Cards

Background

In 1986 after struggling for years to secure a growing stream of revenue, the American Board of Internal Medicine (ABIM), a 501(c)(3) non-profit physician testing agency originally domiciled in Iowa and now located in Philadelphia, PA, unilaterally decided to make its once voluntary and lifelong Board certification credential time-limited. In 1986, the prospect of implementing universal healthcare (Hillarycare) loomed on the political landscape so there was a growing sentiment within the ABIM that its role should shift from determining a physician's excellence to practice medicine to assuring a physician's practice adequacy. By making this strategic philosophic change, the ABIM assured itself a new and virtually limitless revenue stream for years to come on a promise they knew how to determine such a metric.

There was only one problem: how does one define physician excellence?

Excellence in medicine is not easily defined. Is physician excellence defined by patience, empathy, intellect, experience, surgical dexterity, technical skills, or some combination of these things? Or might it be judged on something else entirely? Might the qualities of excellence from a general internist be very different from those of a specialist in internal medicine?

Such important questions did not concern the leadership at the ABIM. They were convinced that not only was it possible to define methods for measuring excellence, they would blaze the trail for this endeavor. To assist them, the leadership of the ABIM co-opted the nation's brightest scholars, lured by first-class airfares, the nation's most luxurious hotels, and elegant wine selections at dinner, to create more challenging and clever test questions for practicing physicians. None of these scholars complained.  Many were honored to provide such a service; it was a great gig for those lucky enough to escape the mundane work of actually caring for patients while being wowed by the lavish creature comforts afforded to them.

On the other hand, working physicians on the front line of health care were caught completely off-guard by the unexpected unilateral "re-certification" rule change developed in December 1986 and ultimately implemented by the ABIM in 1990. Practicing physicians, accustomed to a lifetime of testing and unaccustomed to strongman tactics and political pandering that threatened  "uncertain consequences" if they did not participate, never questioned the rationale for the rule change. For most doctors, the change was seen as just another test they needed to pass to keep working despite never being independently shown to improve patient care or outcomes.

That is, of course, until practicing physicians slowly awakened to the gravity of the ABIM's rule change if they failed re-certification: there was a very real possibility that they might find themselves no longer "Board certified" and could lose their license to practice medicine, hospital admitting privileges, or ability to receive insurance payments. They were cleverly trapped. What choice did they have other than to participate?

Empowered by the significant additional revenues garnered by re-certification and a politically lackadaisical physician workforce, the leadership of the ABIM and the American Board of Medical Specialties (ABMS), along with the many friends they secretly lobbied on Capitol Hill, were asked to deliver even more for their undisclosed corporate clientele: Premier, Inc., CECity, Kaiser Foundation Health Plans and Hospitals, the IPC The Hospitalist Company and their close-held relationships with the Center for Medicare and Medicaid Services (CMS). The leadership at the ABIM decided to expand their definition of physician "excellence" to include the concept of "medical professionalism." This way, a health care cost-saving imperative could be levied on physicians, too.

But medical professionalism, like medical excellence, was not easily defined. Like pornography, the leadership at the ABIM just knew it when they saw it.

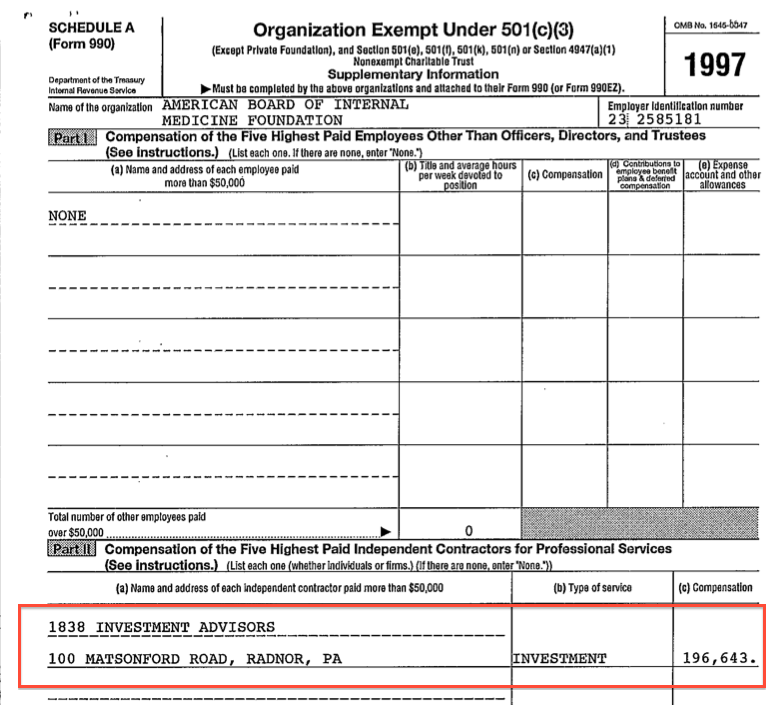
Never deterred, the ABIM convened a "writing group" funded by $59,618,428 in assets the ABIM had secretly funneled from unsuspecting ABIM diplomats' board certification and re-certification fees from 1989 to June 30, 1999 to the secret "American Board of Internal Medicine Foundation." (Author's note: In my opinion, the amount taken from practicing physicians may have been considerably more since the ABIM paid large fees to a high-risk investment firm, 1838 Investment Advisors, LLC that lost 74% of its value before it was quietly shut down. Only after an IRS name change was the undisclosed "ABIM Foundation" finally revealed to the public and practicing physicians in 1999. I believe the origination date and domicile of the Foundation was repeatedly misrepresented to the IRS from fiscal year 2009 to as late as the 2013 IRS Form 990 to obscure its origin. To the best of my knowledge and belief after piecing together available tax forms, the leadership and board of the ABIM authorized $80,278,428 to be taken from diplomats' testing fees to fund the ABIM Foundation in the form of contributions and grants from 1989 through 2007.)

After several years of meetings with members of sympathetic U.S. and European professional societies and leadership from the Robert Wood Johnson Foundation, the writing group from the ABIM Foundation achieved their goal. They published their missive entitled "Medical Professionalism in the New Millennium" in 2002 as a non-peer reviewed white paper in the Annals of Internal Medicine and Lancet with the help of sympathetic editors. Not surprisingly, many of the creators of this document have since left medicine to join the lucrative ranks of the insurance and retail pharmaceutical industry like Wellpoint and CVS.

Thanks to their growing avarice and their undisclosed political and health care policy activities, none of the leadership or board members of the ABIM found fault with the purchase of a $2.3 million condominium complete with a chauffeur-driven Mercedes S class town car in December 2007. According to Richard Baron, MD, such an "investment" was the norm for tax-exempt non-profit 501(c)(3) corporations. (The condominium expenses totaled $850,340 from December 2007 through June 30, 2013 (FY 2008: $42,522, FY 2009: $164,460, FY 2010: 161,957, FY 2011: $165,982, FY 2012: $161,980, FY 2013: $153,439)). In the email I received from him regarding this discrepency, Dr. Baron claimed that many of these "condo expenses" included the depreciation expense for the condominium, yet depreciation for the condominium was never claimed on any ABIM Foundation IRS Form 990 tax form until this fact was disclosed on these pages.

As the requirements to participate in Maintenance of Certification (MOC) mandated by the American Board of Medical Specialties (ABMS) grew, many physicians found the requirements little more than onerous busy-work exercises that distracted from patient care. Many practicing physicians elected to stall or not participate. For these reasons, the pressure on the ABIM to market the ABMS MOC recertification program and to protect their monopoly on the program increased. Many specialty societies, hungry for cash as physician participation at national scientific sessions waned, were increasingly happy to help the ABIM market MOC because of the revenue it generated for them.

ABIM's Director of Investigations

In 2008, it appears the ABIM hired a "Director of Investigations" to investigate physicians or individuals who they suspected might be stealing secrets from their proprietary certification process and disrupting their monopoly.  A unique individual had surfaced that year that promised a return on their investment.  He was perfect: someone with deep ties to law enforcement and surveillance techniques who had created a niche for himself in test security. He was comfortable collaborating with various law-enforcement organizations like the U.S. Postal Inspection Service and the FBI. His self-generated LinkedIn webpage (Author's addendum 9 June 2016 @ 20:00 PM CST: LinkedIn page has been brought down. Earlier partial copy can be viewed here or his Infragard info page should suffice. *** Author's Addendum: July 4, 2016: Mannes' LinkedIn page brought back up) impressive so few would question his integrity. But while this individual seemed perfectly amicable and credit-worthy on the surface, he held a more concerning past that the ABIM may have known but chose to ignore. Perhaps this is why his position and true background has never been formerly disclosed to physicians or the public. He appeared on the scene quietly at first with a press release concerning the existence of "phony boards" in AMA Medical News. A similar press release remains on the ABIM website. As others reportedly tried to capitalize on the board certification money pipeline, another warning of a fraudulent board scheme was circulated by the Connecticut Attorney General's office a short time later. In fact, according to my review of available Form 990 tax forms, this individual and the salary he receives from the ABIM has never been disclosed by the ABIM, yet he freely promotes his position at the ABIM with the movie and test security industries.

It was becoming abundantly clear: the ABIM meant business when it came to protecting their physician testing empire.

Teaching to the Test

With the exponential growth of information in health care, "knowing what to know" to pass a re-certification examination became more important than ever to practicing physicians. Not only were the insurance company and pharmaceutical company pre-authorizations adding to physicians' workload, certification requirements to remain employed were as well. By 2009, the demand for Board review courses that promised successful re-certification pass rates had skyrocketed. Because the stakes were so high and the content of the examination often obtuse, many physicians recognized that they could no longer just rely on their experience to pass the examination. Board review courses became a necessary pre-requisite for many to pass because hints and tips of what content to study were always provided, irrespective of which organization or individual offered them.

As the stakes for certification and re-certification grew, word spread that a doctor, Rajender K. Arora, MD was running an "Unusual Board Review" course that used content remarkably similar to study questions on the ABIM certifying examinations. They had heard he got most of his study materials  from physicians that had already taken the test. Pass rates and course ratings from attendees of Arora's course were good. Many medical schools and hospitals, eager to report high board certification pass rates for their physicians to remain ACGME credentialed, recommended their residents and physicians attend this course. After all, the Arora Board Review had received ACGME accreditation.

But for the ABIM (and for their affiliated professional societies like the American College of Physicians that earn handsome returns from board review materials) who felt their databank of re-used test questions might become compromised and less valuable, something had to be done.

The Raid

So the ABIM tapped the skills of their "Director of Investigations." According to the original complaint of a suit filed under seal by the ABIM, an employee of the ABIM was tapped to attend (see items 43 and 48) and audiotape at least one of Arora's courses. The ABIM has retained this audiotape in their possession (partial transcripts of the recordings made by ABIM are included here, here, and here). It appears this evidence was used to help secure an ex parte Temporary Restraining Order and Seizure and Impoundment Order issued against Rajender K. Arora, MD, Anise Kachadourian, MD, and another 50 unnamed "John Doe's" in 2009. The complaint was filed "under seal" (not disclosed to the public initially). Only three names (other than the ABIM's counsel) appear on that order that supplied the judge with the evidence the ABIM had acquired: Christine Cassel, MD (President and CEO of the ABIM), Rebecca Baranowski (Senior Clinical Content Manager for the ABIM), and A. Benjamin Mannes (Director of Investigations for the ABIM). On the basis of the evidence obtained by the undisclosed ABIM employee (s), US Marshals executed a writ to seize materials from Dr. Arora's residence including copies of computer hard drives, backup tapes, Dr. Arora's cell phone as well as 36 boxes of course materials.

But what the Director of Investigations, A. Benjamin Mannes, (aka "Ariel Benjamin Mannes") likely failed to disclose to the judge (and still has never been fully disclosed in my own earlier personal email communications with him, other US physicians, or the public) is that Mr. Mannes carries two felony convictions. These convictions were issued Dec 13, 2005. According to District of Columbia felony conviction #006438 found on the DC Court Cases Online search web page, Mr. Ariel Benjamin Mannes, a former DC police officer released from the DC police force in 2003 after targeting a journalist who wrote a satire on dirty DC cops, was later convicted on charges of (1) impersonating a DC police officer and (2) carrying an unregistered firearm in 2005 after working as a bouncer "keeping the piece" (details at this link) at a local D.C. nightclub to supplement is income while working for the TSA, Railroad division. As a result of the night club incident, Mr. Mannes was released from the TSA in late 2007 just before apparently joining the ABIM. He lost his appeal of these convictions Oct 21, 2008 less than two months before he appeared (backup pdf of the webpage here) in the press as the "director of test security" for the ABIM.


This revelation is not a minor concern for practicing physicians and the public. Certainly using convicted felons for security jobs is not news. But the irony that a felon would be hired to tract the elusive physician thought to be cheating as they studied for a credentialing examination is lost on few.

Many other important questions remain. Did the ABIM call the police before initiating their investigation or use Mr. Mannes, a confirmed expert at intimidation, as a "law enforcement officer" to establish probable cause for the search and seizure at Dr. Arora's residence? What policy and process does the ABIM have to assure due process of physicians accused of cheating? Why was a press release issued before due process occurred? Why is his salary and position of someone this instrumental to physician "investigations" and intimidation not disclosed on ABIM tax forms or elsewhere? How much did (and does) Mr. Mannes earn for his "services" at the ABIM? Would the 139 physicians who were either sued, sanctioned, or vilified in the mainstream media for "cheating" without due process have had a very different outcome if Mr. Mannes' past history been brought to light? How many other of the "50 John Doe's" does the ABIM intend to sue based on Mr. Mannes' "investigation" work and how much will this cost practicing physicians?  With whom did Mr. Mannes collaborate in law enforcement? Did Mr. Mannes' access to law enforcement assets allow him to track physician email addresses? What did he disclose to them and what did they disclose to him? Were the physicians struggling to remain credentialed to practice medicine after the ABIM's abrupt unilateral and highly lucrative certification rule change at fault or was the leadership and board members of the ABIM who instigated this attack on their character using a convicted felon? Who at the ABIM directed an "employee" to attend and secretly audiotape the Arora Board Review courses?  Should attendees of Dr. Arora's course have been informed they were being audiotaped or did the ends justify the means? Were physicians' Fourth Amendment Constitutional rights violated because a law enforcement officer was not used to obtain the search and seizure order on Dr. Arora's residence? Was evidence manipulated? What right to privacy are physicians entitled that study for their MOC re-certification examination? Do physicians have a right to know that attendance at a board review course could be used against them if they mention question content they heard from others?

Considering the millions of dollars involved, the myriad of conflicts of interest, and use of a felon for Board certification and re-certification "investigations," who cheated whom in 2009?

Sadly, these concerns have not disqualified Mr. Mannes and the ABIM's former prosecuting attorney from ABIM's law firm, Marc Jacob Weinstein (with whom Mannes collaborated and who helped bring the original legal complaint against Dr. Arora in 2009) from serving leadership roles (or as employees) of the test security firm, Caveon and marketing their expertise to the Association of Inspectors General or test security conferences (page 19) as late as November, 2015. It is also concerning that Mr. Mannes' background allows him to serve as Governor on the Board of Directors of Philadelphia InfraGard. (For those unfamiliar, "InfraGard is a partnership between the FBI and the private sector created after the 9/11 terrorist attacks that is an association of people from businesses, academic institutions, state and local law enforcement agencies, and other participants dedicated to sharing information and intelligence to prevent hostile acts against the U.S." Doctors should note that Philadelphia InfraGard lists its address as the same address as the FBI in Philadelphia.)

I believe Christine Cassel, MD, who was President and CEO of the ABIM at the time, bears much of the responsibility for the actions and direction of the organization during her tenure. The day after publishing the ABIM press release about the ABIM's actions and the appearance of a simultaneous article in the Wall Street Journal on the matter, Dr. Cassel published a column on the KevinMD blog 10 Jun 2010 entitled "ABIM responds to doctors sharing board certification questions." The original link to the redacted Arora emails that the ABIM claimed formed the basis of their suits against physicians has since been removed. (I retrieved the emails from the internet archive here). In her column, Dr. Cassel explained: "through these actions we are taking, we are reassuring patients and the public that the can continue to trust the process and, and (sic) physicians can continue to trust that it is a fair and rigorous assessment of their medical knowledge and judgment." In retrospect, I believe Dr. Cassel had good reason to use strongman tactics and a convicted felon against more vulnerable physicians: to insist the income generated by physician re-certification be protected. In her 11-year history as President and CEO, to the best of my knowledge, she earned at least $10.88 million dollars, with nearly $9 million of that amount from fees paid diplomats of the ABIM. Dr. Cassel, who it appears was pivotal in organizing the raid on these physicians' residences for her financial and political benefit, was a member of the President's Council of Advisors on Science and Technology (PCAST) at the time and remains there today. PCAST is an advisory group of the nation’s leading scientists and engineers who directly advise the President of the United States and the Executive Office of the President. Not surprisingly, Dr. Cassel who ironically describes herself a "leading expert in geriatric medicine, medical ethics, and quality of care," does not participate in Maintenance of Certification despite being a founding member of the Institute of Medicine and the former President and CEO of the National Quality Forum that determines quality metrics for the nation's hospitals on behalf of the Center for Medicare and Medicaid Services. Given her long-standing conflicts of interest with Kaiser Foundation Healthcare and Hospitals, is there any wonder why she was appointed as Planning Dean for the newly-announced Kaiser Permanente School of Medicine as of March 1, 2016? What message will her history of intimidation and questionable ethics send to Kaiser's future medical students?

ABIM's Ongoing Legal Actions

Currently, the ABIM is involved in another suit they brought against Arora Board Review attendee, Jaime Salas Rushford, MD from Puerto Rico. According to the letter sent to Dr. Salas Rushford on May 8, 2012, the ABIM was "conducting an investigation into the practices of Arora Board Review and its customers." According to the letter, the ABIM traced emails they obtained from Dr. Arora's computers and on the basis of their discovery "determined to indefinitely revoke your certification and will notify the Medical Board in every jurisdiction in which you are licensed" without due process. Given what we now know about the practices of the ABIM and their "Director of Investigations," is there any surprise that  Dr. Salas Rushford is having difficulty obtaining documents from the ABIM for his defense and for his countersuit against them? The foot-dragging and excuses made by the ABIM, including the possibility that Dr. Salas Rushford will make the settlement arrangement between Dr. Arora and the ABIM publicly available on his website, suggests the ABIM cut a special deal with Dr. Arora whom they never sued. What was that arrangement? Why has this not been disclosed publicly? How many other physician email addresses obtained from the Arora Board Review course computers does the ABIM still plan to track down and sue? How many millions of dollars have been squandered by the ABIM in legal attacks upon physicians attempting to fulfill the ABIM's unilaterally mandated re-certification requirements?

Most of all: how much more is the ABIM hiding?

It is difficult to imagine a more Kafkaesque twist to US medicine's professional regulatory system.  At least six physicians were sued as a result of the ABIM's raid on Arora's residence and 134 more sanctioned, resulting in untold professional ridicule, anxiety, embarrassment, and potential loss of their ability to practice medicine. No doubt their patients suffered, too. To add insult to injury, Ms. Lynn Langdon, then the Chief Operating Officer of the ABIM and a non-physician staff member of the ABIM who earned $681,152 in FY 2012 ($297,646 as a "bonus and incentive compensation"), sent thousands of "letters of concern" to other physicians who attended the Arora Board Review course and reportedly keeps those letters on file. Richard Baron, MD, the current President and CEO of the ABIM, earned $61,216 as Chair of the Directors at the time of the audiotaping of the Arora Board Review course and was surely was aware of the raid as well. Like the McCarthy era, it appears we have a system of regulators that will stop at nothing to intimidate and blackball physicians to assure funding of their regulatory cartel.

It is time for the public and our professional societies to know the truth. I believe, given these facts, that the ABMS MOC program (and any iteration that it might morph into) has no place in US medicine and should be abandoned immediately. I also believe the Wall Street Journal that published its earlier story in 2009 with the headline suggesting physicians "cheated" should publish a retraction and provide a follow-up investigation of the ABIM with these facts in mind to set the record straight.  After all, the simultaneous release of the Wall Street Journal story the same day the ABIM press release was issued, coupled with the fact that physicians' names appeared in the article that did not appear in the press release, suggests the Journal was tipped to the story by the ABIM who sought to profit from their actions. To the best of my knowledge at this time, no physician that was sued by the ABIM as a result of the Arora raid has paid a dime in penalties to the ABIM for copyright infringement for attending the Arora course. Yet how much harm was experienced by the 139 physicians who were sued or sanctioned by the ABIM on the basis of the irresponsible actions of the ABIM and their felonious "Director of Investigations?" I know of at least one physician who received the ABIM's "letter of concern" has been unable to re-certify in any subspecialty since that letter was issued.

Moving Forward

It is time for a full investigation of the ABIM and its practices by the Department of Justice, Internal Revenue Service, or the Federal Trade Commission. Are the tactics, that have been used by the ABIM typical of a non-profit 501(c)(3) organization granted tax-exempt status? It will take time and resources to do so, but the public and practicing US physicians deserve to know the truth of all that has transpired and continues to transpire with our nation's physician regulatory system. Without such an investigation, it is hard to see how the ABIM or the ABMS will ever regain the trust of physicians or the public. Clearly, the status quo is unacceptable. If the ABIM and ABMS structure are to survive, bylaws must be changed to insist that an elected board will lead each subspecialty society in lieu of the appointed ones and membership of each organization must decouple themselves from the government and corporate interests that financially benefit the current system.  A full independent financial audit as far back as 1986 as well with full disclosure of tax filing discrepancies is especially needed.  Professional societies and academic journals who conspired with the ABIM and continue to support the ABMS MOC program for their financial benefit need a similar shake-up as well.

Physicians want to care for patients, we do not need unaccountable henchmen and bureaucrats hell-bent on their own power and profits to do our job. It will be up to each of us to demand that hospital systems and insurance companies no longer require ABMS specialty board "maintenance of certification" as an exclusive requirement for licensure, hospital admitting privileges, academic appointments, or insurance panel participation. If they do, it will be up to each of us to demand justice.


"It ain't what you don't know that gets you into trouble.
           It's what you know for sure that just ain't so."

- Mark Twain

(borrowed shamelessly from the opening quote of "The Big Short")

-Wes


References:

Dr. Wes blog: The Maintenance of Certification Controversy 2015 - The Year in Review 
Dr. Wes blog: The Business of  Testing Physicians

Image references: 
https://www.thrillist.com/culture/best-frank-underwood-quotes-house-of-cards-funny-and-witty-lines
http://houseofcardsquotes.tumblr.com/post/77137104455
http://www.scoopwhoop.com/world/hoc-quotes/