Writing in the Wall Street Journal (WSJ) Dr. Daniel F. Craviotto Jr., an orthopedist, made a plea to physicians to declare independence from third parties and emancipate themselves from servitude to payers, mandates and electronic health records (EHR).Saurabh Jha, MD's (@RogueRad) piece first appeared on The Health Care Blog, where it caught my attention.
As rants go, this was a first class rant. But its effect was that of a Charles de Gaulle’s whisper to Vichy France rather than a Churchillian oratory at the finest hour.
The article went viral (it has been tweeted nearly 3000 times), though with little virulence. And it is not WSJ’s paywall to blame.
The author might have assumed that most the healthcare community in general and physicians in particular wish to be free from regulations. I have serious doubts that this assumption is correct in the aggregate. The relationship between regulators and physicians is more complex and symbiotic than it first appears.
Some physicians believe in bureaucracy. Rationalism will march us out of our healthcare wilderness. This belief in scientific managerialism, faith in technocracy, is the new theism. The rationale of the new theists is that regulations fail not because they are inherently useless but because there are so few of them, and even fewer that are actually smart.
Like the first religions started with polytheism, the new believers want more agencies, more alphabet soups, more gods.
This type of reasoning can empirically neither be proven nor disproven. Hence, the comparison to religion is apt. It is like the argument made by neo-Keynesian economists: stimulus failed because it was too small. How do we know it was too small? Because it failed.
This circular reasoning is immortal and akin to an infinite set; one can always impute upon it the promise of success if only one added just a little more.
Convinced of their own virtue and the vice of others, many physicians crave more regulations. They hope that in the next round will emerge the regulatory Thor wielding his nuanced hammer on evil Medicare serpents and fraudsters. Instead we receive the leviathanic, uncoordinated Moby Dick that throws Quuequeg out with Ahab and splashes a lot of salt water in the process.
Some meet any criticism of third party players, coding and regulatory waste with a false dichotomy “so now you want to abolish insurance and Medicare, what’s your alternative?” or “you are against ICD-10, so should we descend in to anarcho-capitalism and send poor kids to workhouses?”
This line of thinking reminds me of the willful scarcity of cerebral activity that allows some to interpret in any government intervention a short step to National Socialism. The phenotype is the same. The polarity is merely reversed.
The rest of us, those who can see the vast zone between a dysfunctional Electronic Health Record and Zero Government, are merely quibbling about the price, not the principle.
And quibble we must.
We should question the marginal utility of regulations, the evidence base from which they arise, the unintended consequences of their complexity, their opportunity costs and the waste of tax payer’s money for rules that do not improve outcomes.
Outcomes, remember outcomes? We hold a new drug or device to this metric, why not a regulatory decree that is both perennially alive and permanently fossilized?
And so the author of the rant has a point.
An inordinate time of physicians is spent on non-clinical work such as coding, billing and compliance. This has been estimated to be as high as 80 % (I am waiting for the regulated shape shifter to say this is clinical work, really). One recognizes that non-clinical work is unavoidable to an extent, and in saying that 80 % is too high I hope the binary minds of some do not infer that I think it should be zero percent. But if 80 % is not too high how about 90 %? 99 %? 99.5 %? Is there no limit?
If physicians spend more time in activities that allow them to be measured than the activity for which the measurements are sought, this is a sign of dysfunction. The clinical “horse” is being grounded by the regulatory “cart.”
And this has consequences for patient care. Physicians rarely make eye contact with patients these days staring, instead, at the vast dark matter of their EHR wondering how many words it takes to say the patient has a common cold.
As Nietzsche warned, well sort of, “If you gaze into the EHR, the EHR also gazes in to you. Beware physicians, lest you become an electronic health record.”
We are living an epidemic of documentation of such utter clinical irrelevance that one struggles to comprehend. And yet some demand even more rules, more codes and more metrics as more granularity is desired and imperfection of information even less tolerated.
To paraphrase Churchill “never was so little owed by so few to so many.” Never was so little achieved by so many. A giant bureaucratic sledgehammer is being wielded against a nut it repeatedly fails to crack.
Craviotto’s declaration of independence is misplaced. To rue government involvement in healthcare within the safety of a guild, protected from the vicissitudes of the market and competition with Rajeev from Bangalore is a tad rich and rather like the famous ungrateful climber who was carried on the back of Sherpas to within a canter of the summit of Everest.
He should, instead, have appealed to our sanity and common sense, the only weapons we have to tame the bipartisan regulatory Goliath.
Friday, May 16, 2014
When We Worship Process More Than Patients
If you read nothing else this week, please read these words from Saurabh Jha, MD, Assistant Professor of Radiology at the University of Pennsylvania (republished here with permission):


The Iron Triangle and Evidence-based Medicine
From the Journal of Evaluation in Clinical Practice:
-Wes
h/t: Ivan Oransky on Twitter
It is naïve to think that we can prevent vested interests from introducing bias. Politicians cannot tally their votes and in sport we rely on umpires, not player, to call the penalties. What are we thinking relying on industry provide evidence about health interventions that they have developed, believe in and stand to profit from? We need to recognize this inherent bias and take action against it.Read the whole thing.
It is beyond the scope of this paper to discuss practical solutions in great detail, however, we make the following suggestions:
- The sensible campaign to formalize and enforce measure sensuring the registration and reporting of all clinical trials (see http:// www.alltrials.net/) should be supported – otherwise trials that do not give the answer industry wants will remain unpublished.
- More investment in independent research is required. As we have described, it is a false economy to indirectly finance industry-funded research through the high costs of patented pharmaceuticals.
- Independent bodies, informed democratically, need to set research priorities.
- Individuals and institutions conducting independent studies should be rewarded by the methodological quality of their studies and not by whether they manage to get a positive result (a ‘negative’ study is as valuable as a ‘positive’ one from a scientific point of view).
- Risk of bias assessment instruments susch as the Cochrane risk of bias tool should be amended to include funding source as an independent item.
- Evidence-ranking schemes need to be modified to take the evidence about industry bias into account. There are already mechanisms within EBM evidence-ranking schemes to up- or downgrade evidence based on risk of bias. For example, the Grading of Recommendation Assessment, Development and Evaluation (GRADE) system allows for upgrading observational evidence demonstrating large effects, and downgrading randomized trials for failing to adequately conceal allocation (and various other factors). However, currently such schemes are agnostic to the origins of evidence and do not expressly recognize the high risk of bias when the producers of evidence have an invested interest in the results. It would be easy to introduce an evidence quality item based on whether a trial was conducted or funded by a body with a conflict of interest. If so, the evidence could be downgraded. Given the failure of current evidence-ranking schemes to detect and rule out industry-funding bias, this is a necessary step if EBM critical appraisal is to remain credible.
-Wes
h/t: Ivan Oransky on Twitter
Wednesday, May 14, 2014
What's Wrong With This Picture?
A US medical conference opening plenary session:
A European medical conference opening plenary session:
Just sayin' -
-Wes
 |
| Heart Rhythm Society Meeting 2014 (Click to enlarge) From https://twitter.com/HugoOC/status/464204486576058368 |
A European medical conference opening plenary session:
 |
| NICE Annual Conference 2014 (Click to enlarge) From https://twitter.com/LockOn_Tweets/status/466514188521598976 |
-Wes
Friday, May 09, 2014
The Health Care Industrial Complex and the Iron Triangle
Walking to the 2014 Heart Rhythm Society (HRS) Scientific Sessions this morning, I couldn't help but marvel how beautiful San Francisco seemed today. The weather was perfect, the streets bustling, the quaint shops and eateries doing brisk business in a very hip metropolitan city with a distinctive West Coast vibe. As I walked up to the Moscone Conference Center, I was struck by the size and scope of the facility and its cool, corporate look.
"Welcome," I thought, "to the Health Care Industrial Complex." This meeting was, after all, designed for me and the other Heart Rhythm Specialists from all over the world.
After picking up my badge I shuttled off to my first session and picked up the fresh flier published on the previous day's events. The publication was remarkably professional, processed with all the proper public relation jargon and complementary hyperbole. The Heart Rhythm Society app that I downloaded on my iPhone, too, looked eerily similar to the polished one at the ACC meeting earlier this year, just the sponsor page that blinked "Biotronik" instead of "Amgen" as it had earlier this year. Finally, as I turned by attention back to the flier, there on page two was a picture of Hugh Calkins, MD the current President of HRS and James Youngblood, the Society's "professional" CEO, honoring the "HRS Infinity Circle Supporters" from Medtronic. Infinity Circle Gold members from Biosense Webster, Boerhinger Ingelheim, Boston Scientific and Janssen and Silver member St. Jude Medical also were honored in the picture's caption.
Of course they were.
Twenty-six years ago I entered the North American Society and Pacing and Electrophysiology (NASPE) as a young fellow in cardiac electrophysiology competing for the Young Investigator Competition. I was nervous as hell as I practice and re-practiced by presentation. I was competing against some of the best and brightest and was thrilled at the opportunity, the heady notoriety, and the opportunity to rub noses with the reviewers (international senior mentors) first hand. Back then I did not have the perspective I have now with the interplay of forces that have come to define US health care. I had no concept of the powerful influence that the vast sums of money, lobbies, special interests, regulators, and oversight agencies have in medicine.
Since that time, NASPE has changed its name to the Heart Rhythm Society to reflect a more global mission. Over the years I have seen the bureaucratic and political influence change the landscape of medicine as I never imagined as I struggle to cope with what it means to practice medicine today. I suppose when one considers that for many communities in America, health care is their economy, I shouldn't be surprised that the business and politics of medicine are now more important than ever.
Years ago near the start of the Vietnam War, President Dwight D. Eisenhower coined the phrase "military industrial complex" in his farewell speech to America. He was describing the policy and monetary relationships that exist between legislators, our national armed forces, and the military industrial base that supports them. These relationships include political contributions, political approval for military spending, lobbying to support bureaucracies and oversight of the industry. The concept began with the concept of coordination between the government and the private sector to provide weaponry to government-run forces.
Now we have the private sector providing funding for our instruments of health care. We see companies that supply medical devices, drugs, insurance, electronic medical records and companies that support lobbying efforts and data mining and richly-paid oversight entities. Today, however, the budget is much, much larger for medicine than the military. Our "health care industrial complex" has grown into the monster it is today with a supporting flotilla of corporate, special interest, regulators and oversight entities, with doctors and patient's swept up by its wake.
Some have called this the "Iron Triangle." And just like it's original reference for the military, we should recognize that it pertains to health care, too. While this may be distasteful to many (including myself), I have also come to recognize that like the military, we need health care. Unfortunately for all of us, this monstrous bureaucratically-wasteful system is what we've created. For me, I find it helpful to understand this interplay, because it helps me focus on my role as a doctor today.
"Welcome," I thought, "to the Health Care Industrial Complex." This meeting was, after all, designed for me and the other Heart Rhythm Specialists from all over the world.
 |
| HRS Infinity Circle Supporters |
Of course they were.
Twenty-six years ago I entered the North American Society and Pacing and Electrophysiology (NASPE) as a young fellow in cardiac electrophysiology competing for the Young Investigator Competition. I was nervous as hell as I practice and re-practiced by presentation. I was competing against some of the best and brightest and was thrilled at the opportunity, the heady notoriety, and the opportunity to rub noses with the reviewers (international senior mentors) first hand. Back then I did not have the perspective I have now with the interplay of forces that have come to define US health care. I had no concept of the powerful influence that the vast sums of money, lobbies, special interests, regulators, and oversight agencies have in medicine.
Since that time, NASPE has changed its name to the Heart Rhythm Society to reflect a more global mission. Over the years I have seen the bureaucratic and political influence change the landscape of medicine as I never imagined as I struggle to cope with what it means to practice medicine today. I suppose when one considers that for many communities in America, health care is their economy, I shouldn't be surprised that the business and politics of medicine are now more important than ever.
Years ago near the start of the Vietnam War, President Dwight D. Eisenhower coined the phrase "military industrial complex" in his farewell speech to America. He was describing the policy and monetary relationships that exist between legislators, our national armed forces, and the military industrial base that supports them. These relationships include political contributions, political approval for military spending, lobbying to support bureaucracies and oversight of the industry. The concept began with the concept of coordination between the government and the private sector to provide weaponry to government-run forces.
Now we have the private sector providing funding for our instruments of health care. We see companies that supply medical devices, drugs, insurance, electronic medical records and companies that support lobbying efforts and data mining and richly-paid oversight entities. Today, however, the budget is much, much larger for medicine than the military. Our "health care industrial complex" has grown into the monster it is today with a supporting flotilla of corporate, special interest, regulators and oversight entities, with doctors and patient's swept up by its wake.
Some have called this the "Iron Triangle." And just like it's original reference for the military, we should recognize that it pertains to health care, too. While this may be distasteful to many (including myself), I have also come to recognize that like the military, we need health care. Unfortunately for all of us, this monstrous bureaucratically-wasteful system is what we've created. For me, I find it helpful to understand this interplay, because it helps me focus on my role as a doctor today.
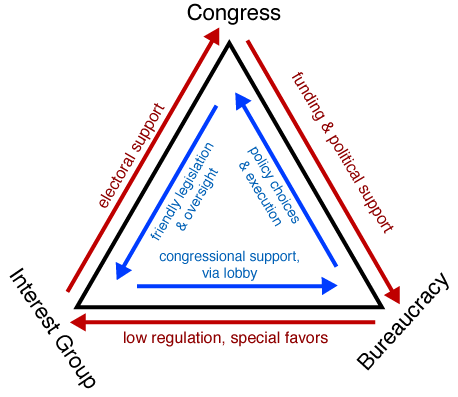 |
| The Iron Triangle |
I can only hope that our younger medical students, residents, fellows, and younger doctors get taught this perspective. Much too often I see them looking more like lambs being led to slaughter. Hopefully, a little insight will help them cope with the seemingly endless bureaucratic and oversight "ideas" that keep surfacing as we struggle to care for our patients. Hopefully this perspective will keep them engaged in pushing back when the onerous becomes intolerable. Hopefully they'll come to understand what they're up against before they throw up their hands in disgust.
Perhaps bringing these concepts to consciousness will allow us to become coordinated advocates for our patients who are being affected by these very same forces. Maybe then, we can continue to hold true to what we love about medicine, and beat back the Iron Triangle that is making it so difficult to do so.
-Wes
Thursday, May 08, 2014
Case Study: When Technology Collides
With the advent of the iRhyhm Xio XT patch monitor capable of recording a single lead EKG for up to 14 days, new moments in cardiac electrophysiology have been born. Some of these moments are anxiety producing for the individual who has to interpret the reports generated by these devices.
Here's a few pages of one I read not too long ago that disclosed some, shall we say, interesting findings and a considerable clinical conundrum.
To orient the reader, when a doctor reads the information collected by the Xio XT patch, he or she first reviews a summary sheet of all the heart rhythm data measured by the device. A clever graphic is supplied that permits rapid overview of the tracing with parallel vertical lines closely arranged next to each other. Each tiny vertical line represents a 20-minute interval of heart rate whose ends represent the minimum and maximum heart rate over those 20 minutes. A dot in the center of the line represents the mean heart rate. Below these closely-arranged parallel lines are other dots that fall on a row representing an arrhythmia or action taken by the patient. Here's what the overview picture of the patient I reviewed looked like (note that only 5 days of heart rhythm data were collected):
A closer inspection of the rhythms represented by the vertical lines with high heart rates reveals some important findings:
The bottom part of the tracing continues on to the next page:
Finally, on the next page, the wide complex rhythm stops, but a more rapid supraventricular rhythm is discovered:
So now what? Clearly, one of the rhythms appears to be a rapid, potentially life-threatening episode of a wide-complex tachycardia. So I called the doctor who ordered the study, a solo doctor (yes, some still exist) and reach his answering service. I have him paged. There was no answer, so I leave a voicemail message urging a return of my phone call. I then attempt to call the patient. No answer. I call again. No answer to either the doctor or the patient's home/work/cell phone.
Uh oh.
So here's a question: When reading such a study, how much more should the reading doctor be expected to do?
-Wes
Here's a few pages of one I read not too long ago that disclosed some, shall we say, interesting findings and a considerable clinical conundrum.
To orient the reader, when a doctor reads the information collected by the Xio XT patch, he or she first reviews a summary sheet of all the heart rhythm data measured by the device. A clever graphic is supplied that permits rapid overview of the tracing with parallel vertical lines closely arranged next to each other. Each tiny vertical line represents a 20-minute interval of heart rate whose ends represent the minimum and maximum heart rate over those 20 minutes. A dot in the center of the line represents the mean heart rate. Below these closely-arranged parallel lines are other dots that fall on a row representing an arrhythmia or action taken by the patient. Here's what the overview picture of the patient I reviewed looked like (note that only 5 days of heart rhythm data were collected):
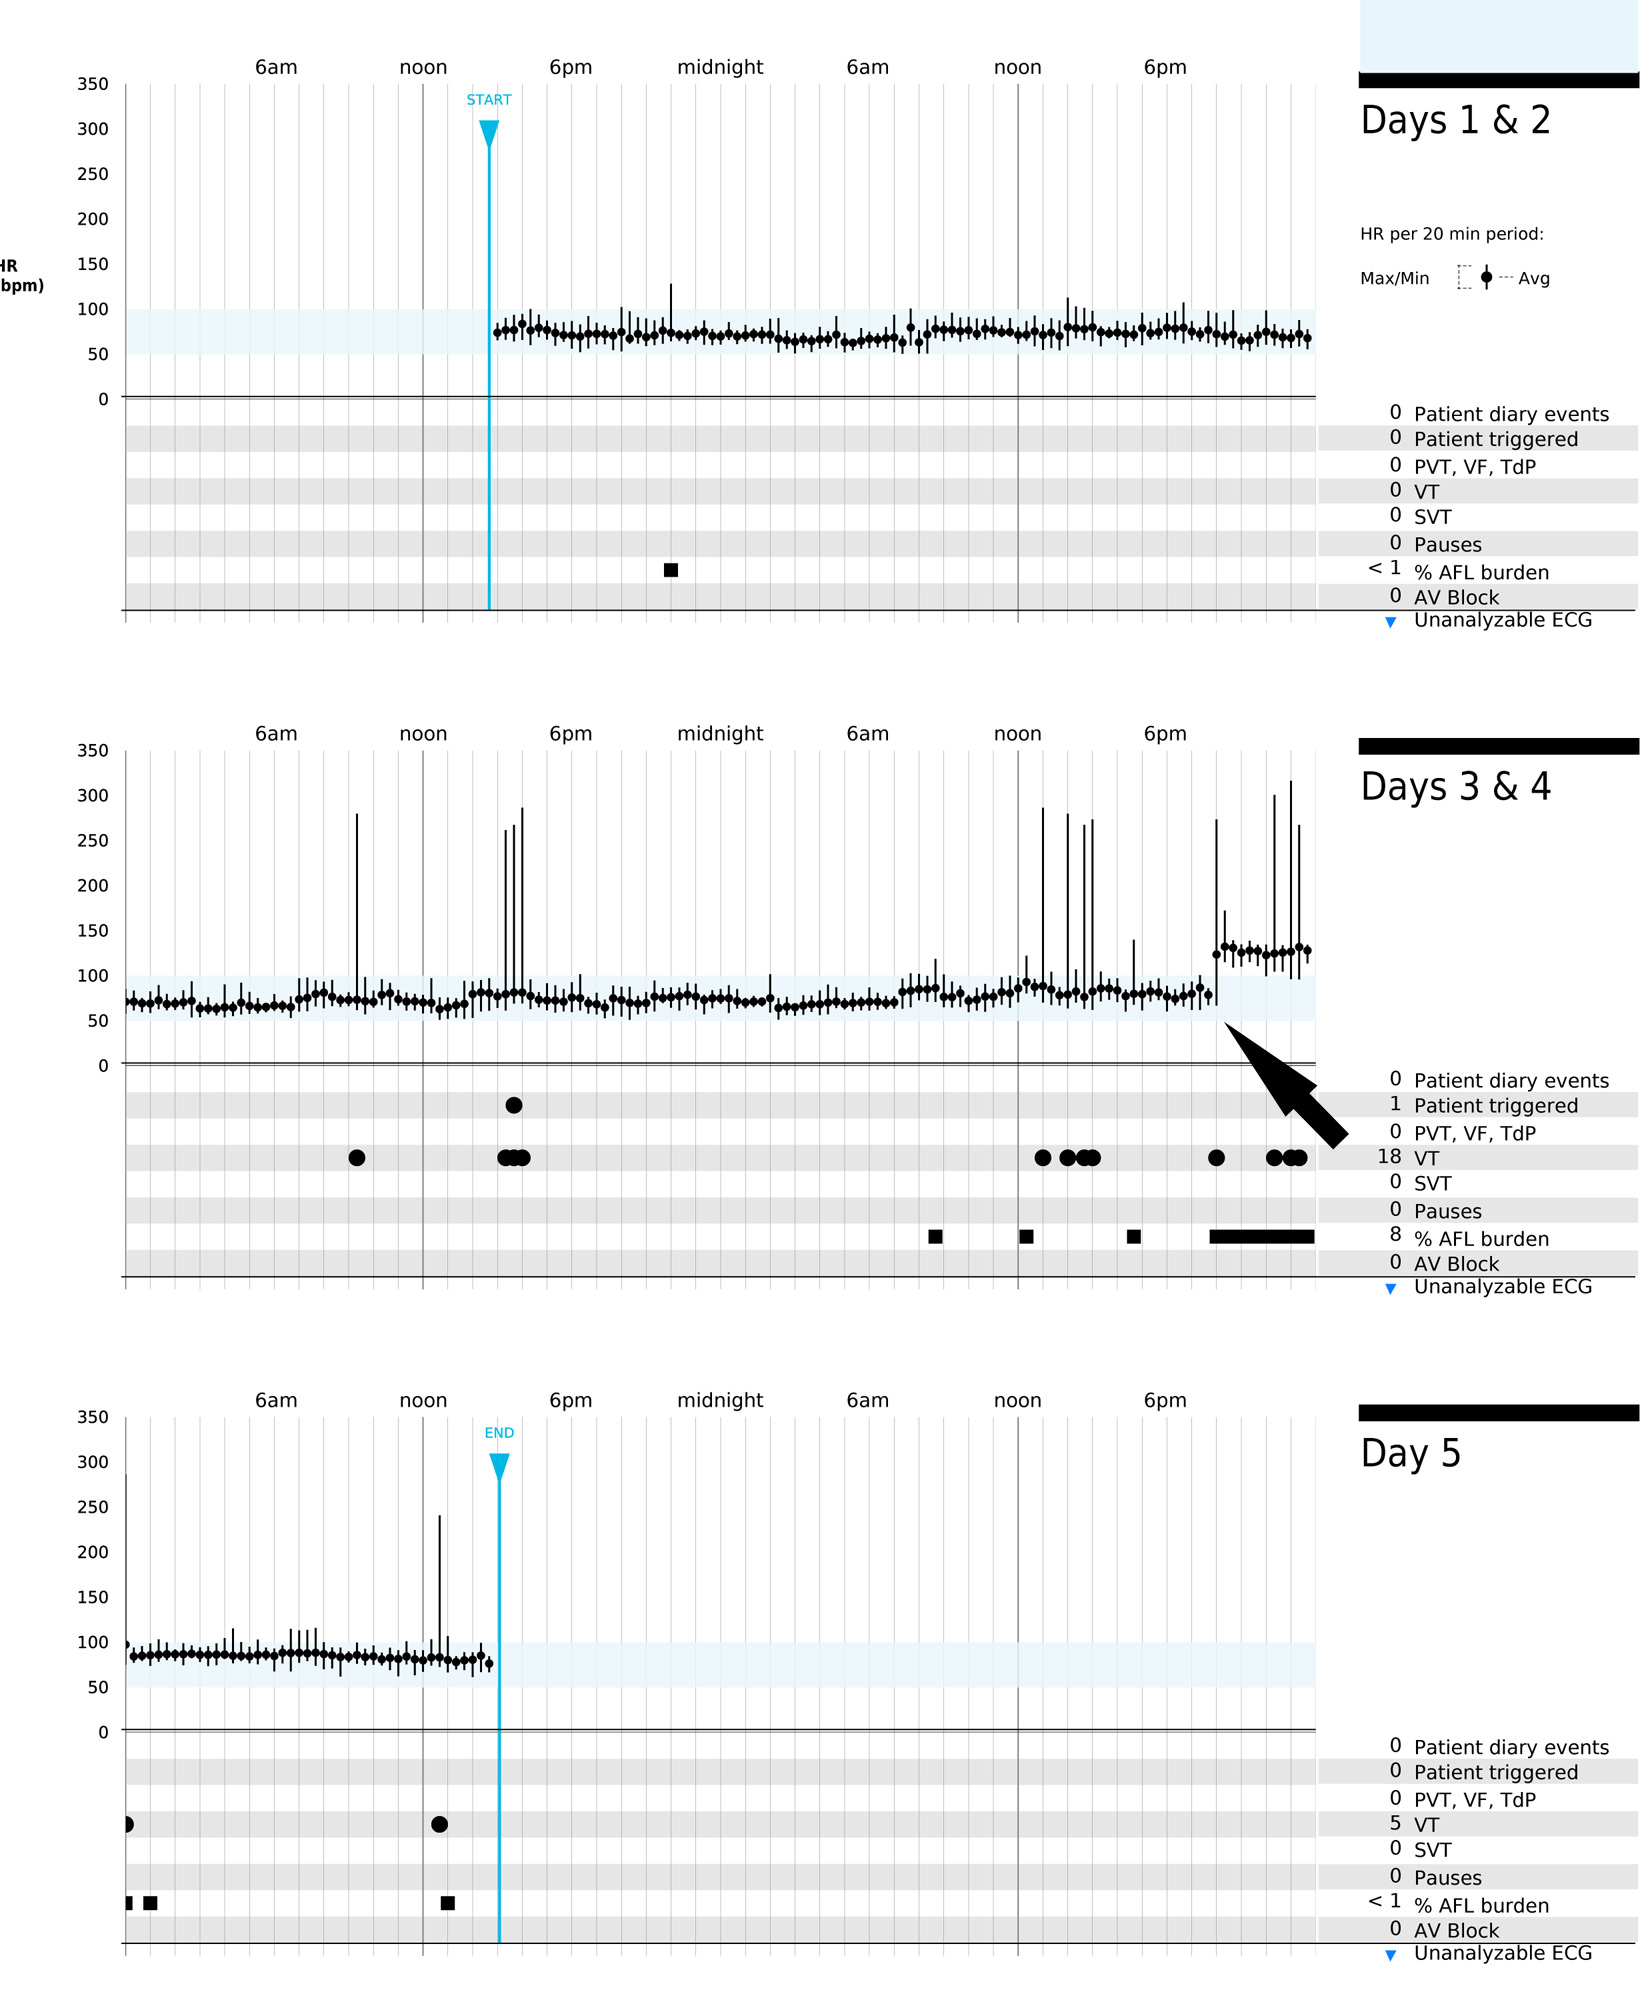 |
| Click to enlarge. Note the increase in average heart rate that occurred at the arrow. |
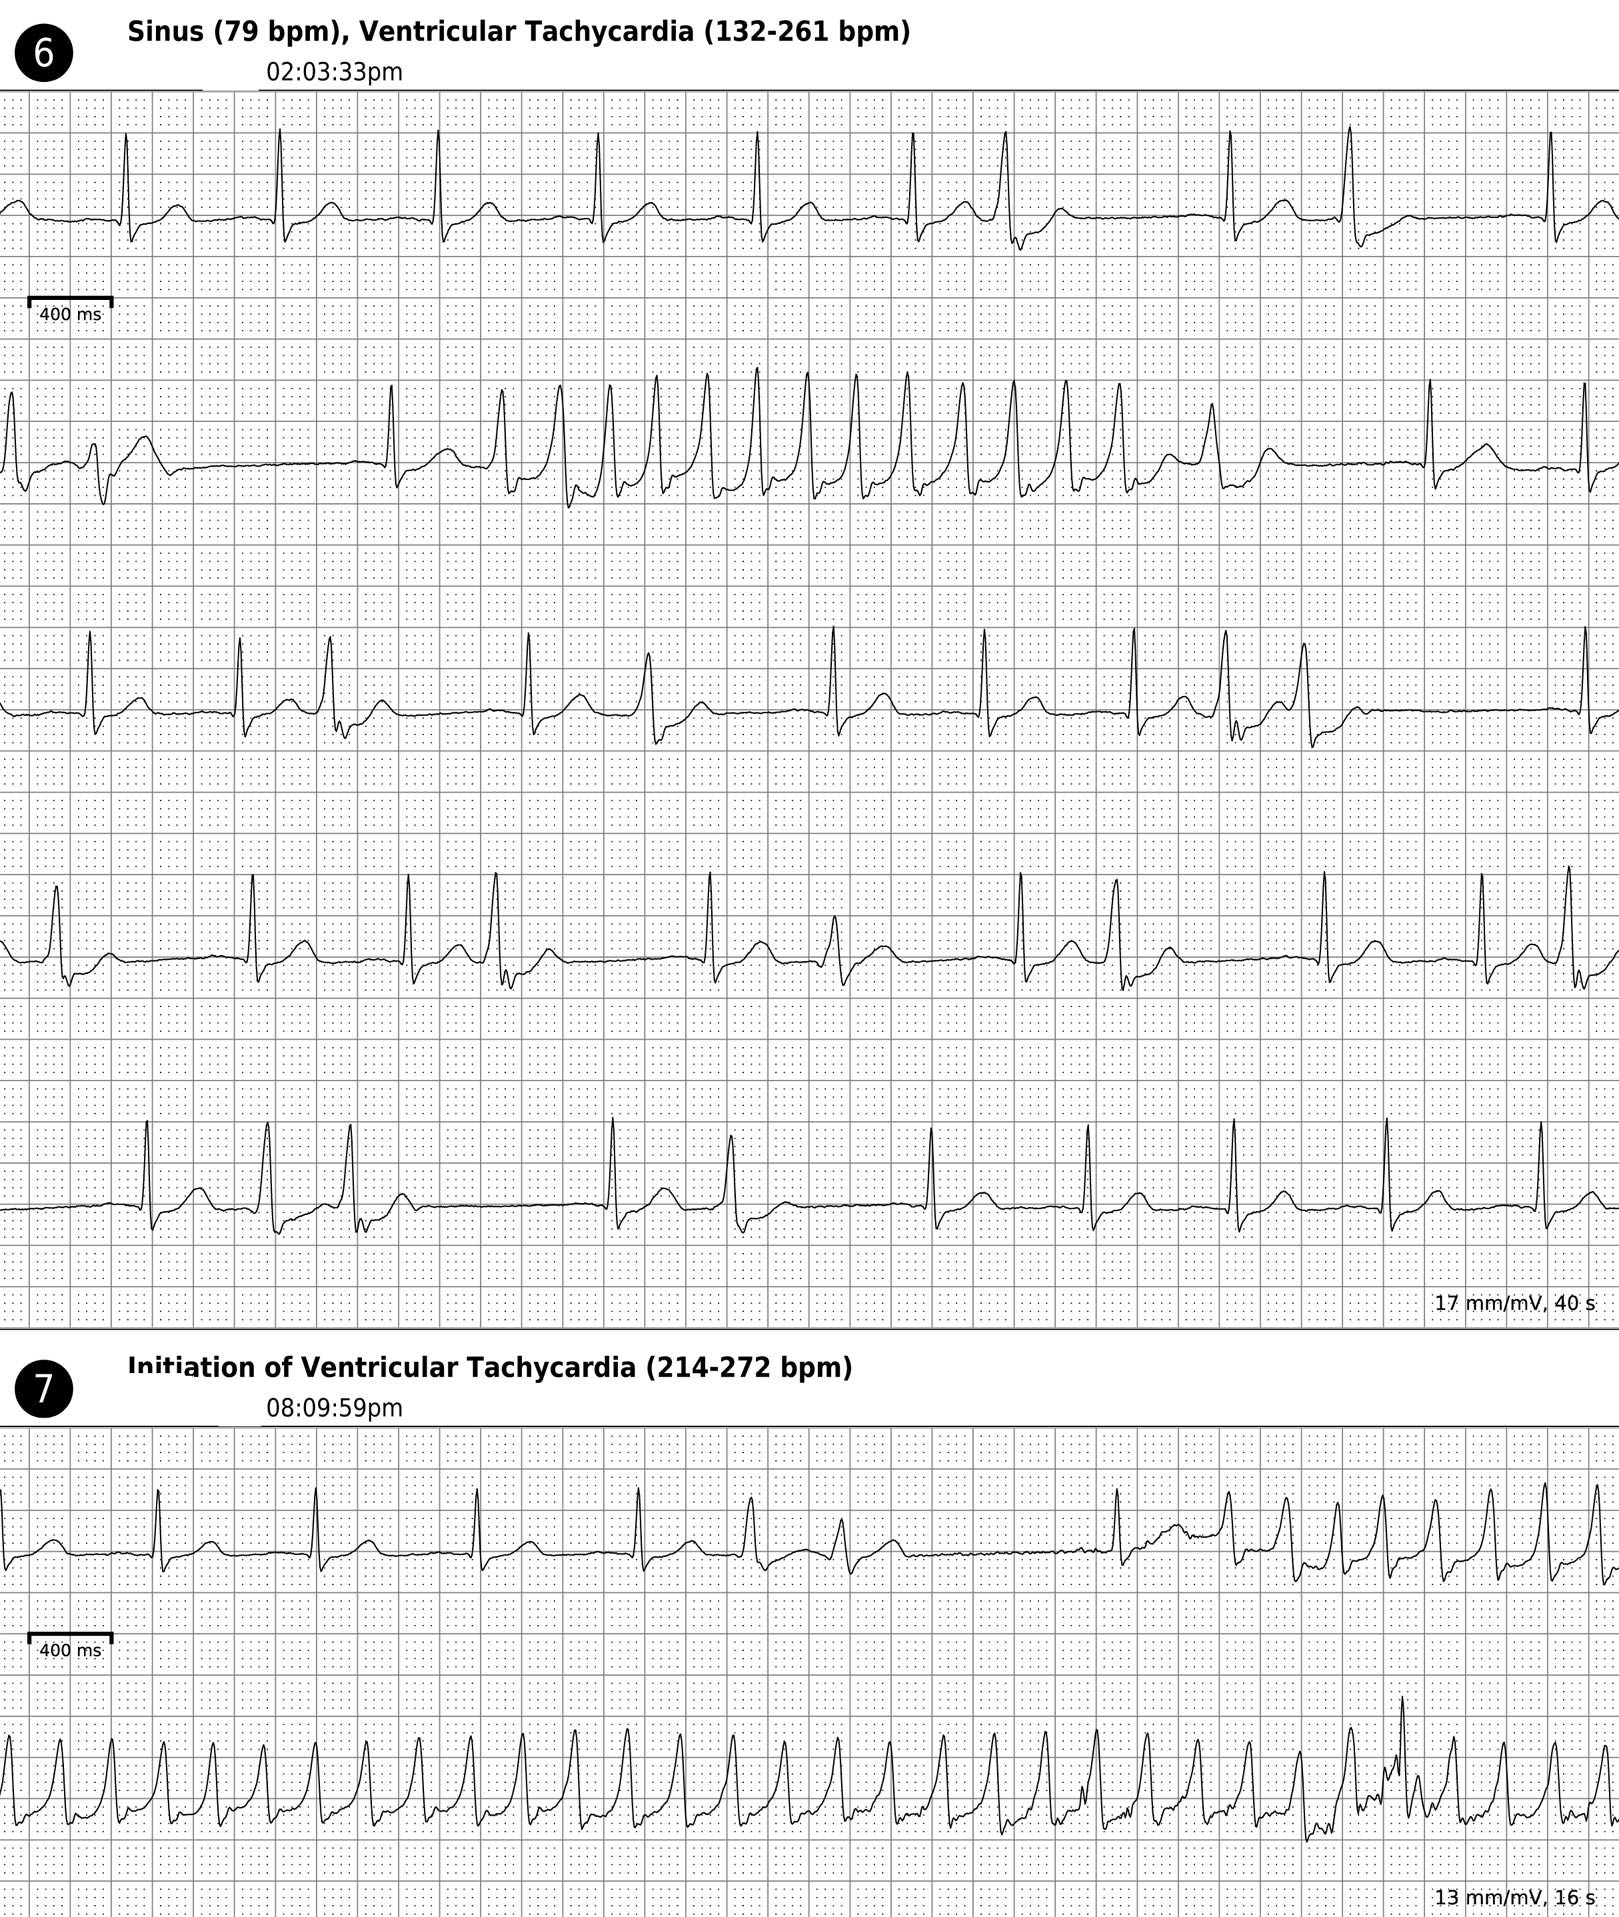 |
| Click to enlarge |
The bottom part of the tracing continues on to the next page:
 |
| Click to enlarge (Note the artifact at the arrow) |
Finally, on the next page, the wide complex rhythm stops, but a more rapid supraventricular rhythm is discovered:
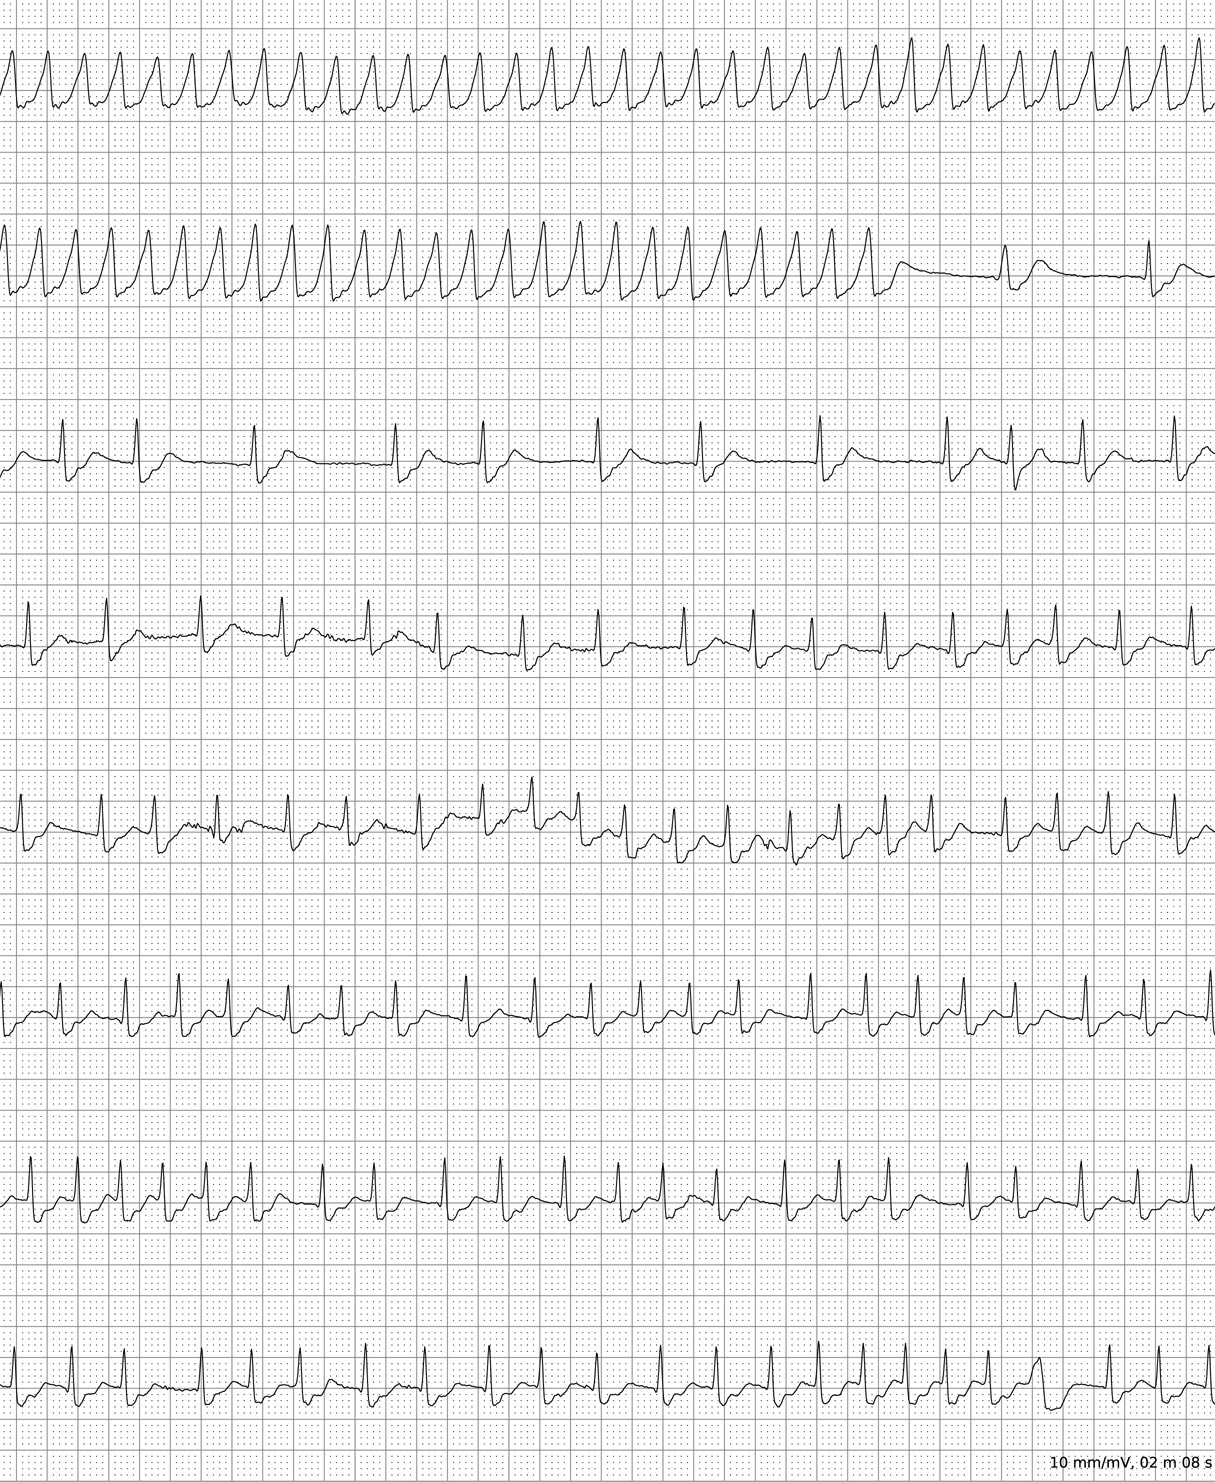 |
| Click to enlarge |
So now what? Clearly, one of the rhythms appears to be a rapid, potentially life-threatening episode of a wide-complex tachycardia. So I called the doctor who ordered the study, a solo doctor (yes, some still exist) and reach his answering service. I have him paged. There was no answer, so I leave a voicemail message urging a return of my phone call. I then attempt to call the patient. No answer. I call again. No answer to either the doctor or the patient's home/work/cell phone.
Uh oh.
So here's a question: When reading such a study, how much more should the reading doctor be expected to do?
-Wes
Tuesday, May 06, 2014
When We Reward Regulators More Than Doctors
Medicine has always had it regulatory fiefdoms, but in 2002 they were greatly expanded. At that time, a charter on "medical professionalism" was published by the American Board of Internal Medicine, the American College of Physicians, and the European Society of Internal Medicine in the Annals of Internal Medicine that touted three fundamental principles: (1) the principle of primacy of patient welfare, (2) principle of patient autonomy, and (3) principle of social justice. The first set of professional responsibilities for physicians was a "commitment to professional competence." While I would truly like to believe this article was sincere, increasingly I am concerned it was a regulatory ploy - one that is more concerned about financial gain than patient benefit.
Let me explain.
I have spent time reviewing the 2011 IRS Form 990 "Returns of Organization Exempt from Income Tax" (the last ones publically available) for each of the member boards of the American Board of Medical Specialties (ABMS) and the ABMS itself. I used the website Guidestar.org to gather these. I assembled the salaries and benefits of the senior executives from each of these organizations in descending order and was surprised what I found (here is the complete 2-page pdf of the data for your review). No more than the top three executive salaries of these organizations represented over $16 million in total compensation in 2011 alone. But even more troubling was the negative relationship that existed between the top-paid executives of these private ABMS member boards and the 2011 compensation for working subspecialty physicians they are supposed to represent. Recall that pediatrics, family medicine, and internal medicine are consistently some of the lowest paid physician subspecialties.
Here is a chart I made of the top 10 board members' annual income compared to the same subspecialty physician salaries in 2011 as reported by Medscape:
Clearly, the US physician credentialing system as it exists now overwhelmingly rewards people with regulatory oversight rather than those who provide patient care. Was this the intent? More specifically, was the intent of the ABIM's "medical professionalism" manuscript to line the pockets of the ABMS member boards in lieu of social justice? What kind of justice is this?
The answer now is not so clear.
To add insult to injury, realize that front-line physicians are increasingly burdened by very high medical school and residency debt for much of their career. As part of their rite of passage into their subspecialty, they must pay the credentialing fees that pay the salaries of these regulators. Should we insist our doctors pay such high fees to support these expensive salaries? How might patients be affected, especially when they have reduced access to doctors who must undergo repetitive certification and re-certification exercises. How do patient's benefit when the certification process appears so flawed?
To me, it seems that we are not seeing a definition of "medical professionalism" in the credentialing juggernaut that these private organizations have created.
We're seeing the definition of "greed."
-Wes
PS: Physicians are welcome to print out the pdf of 2011 ABMS Board members' salaries to share with colleagues and to sign the petition to stop the new onerous biannual MOC recertification requirements.
Let me explain.
I have spent time reviewing the 2011 IRS Form 990 "Returns of Organization Exempt from Income Tax" (the last ones publically available) for each of the member boards of the American Board of Medical Specialties (ABMS) and the ABMS itself. I used the website Guidestar.org to gather these. I assembled the salaries and benefits of the senior executives from each of these organizations in descending order and was surprised what I found (here is the complete 2-page pdf of the data for your review). No more than the top three executive salaries of these organizations represented over $16 million in total compensation in 2011 alone. But even more troubling was the negative relationship that existed between the top-paid executives of these private ABMS member boards and the 2011 compensation for working subspecialty physicians they are supposed to represent. Recall that pediatrics, family medicine, and internal medicine are consistently some of the lowest paid physician subspecialties.
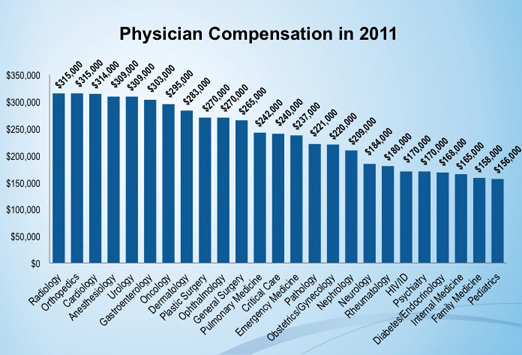
Here is a chart I made of the top 10 board members' annual income compared to the same subspecialty physician salaries in 2011 as reported by Medscape:
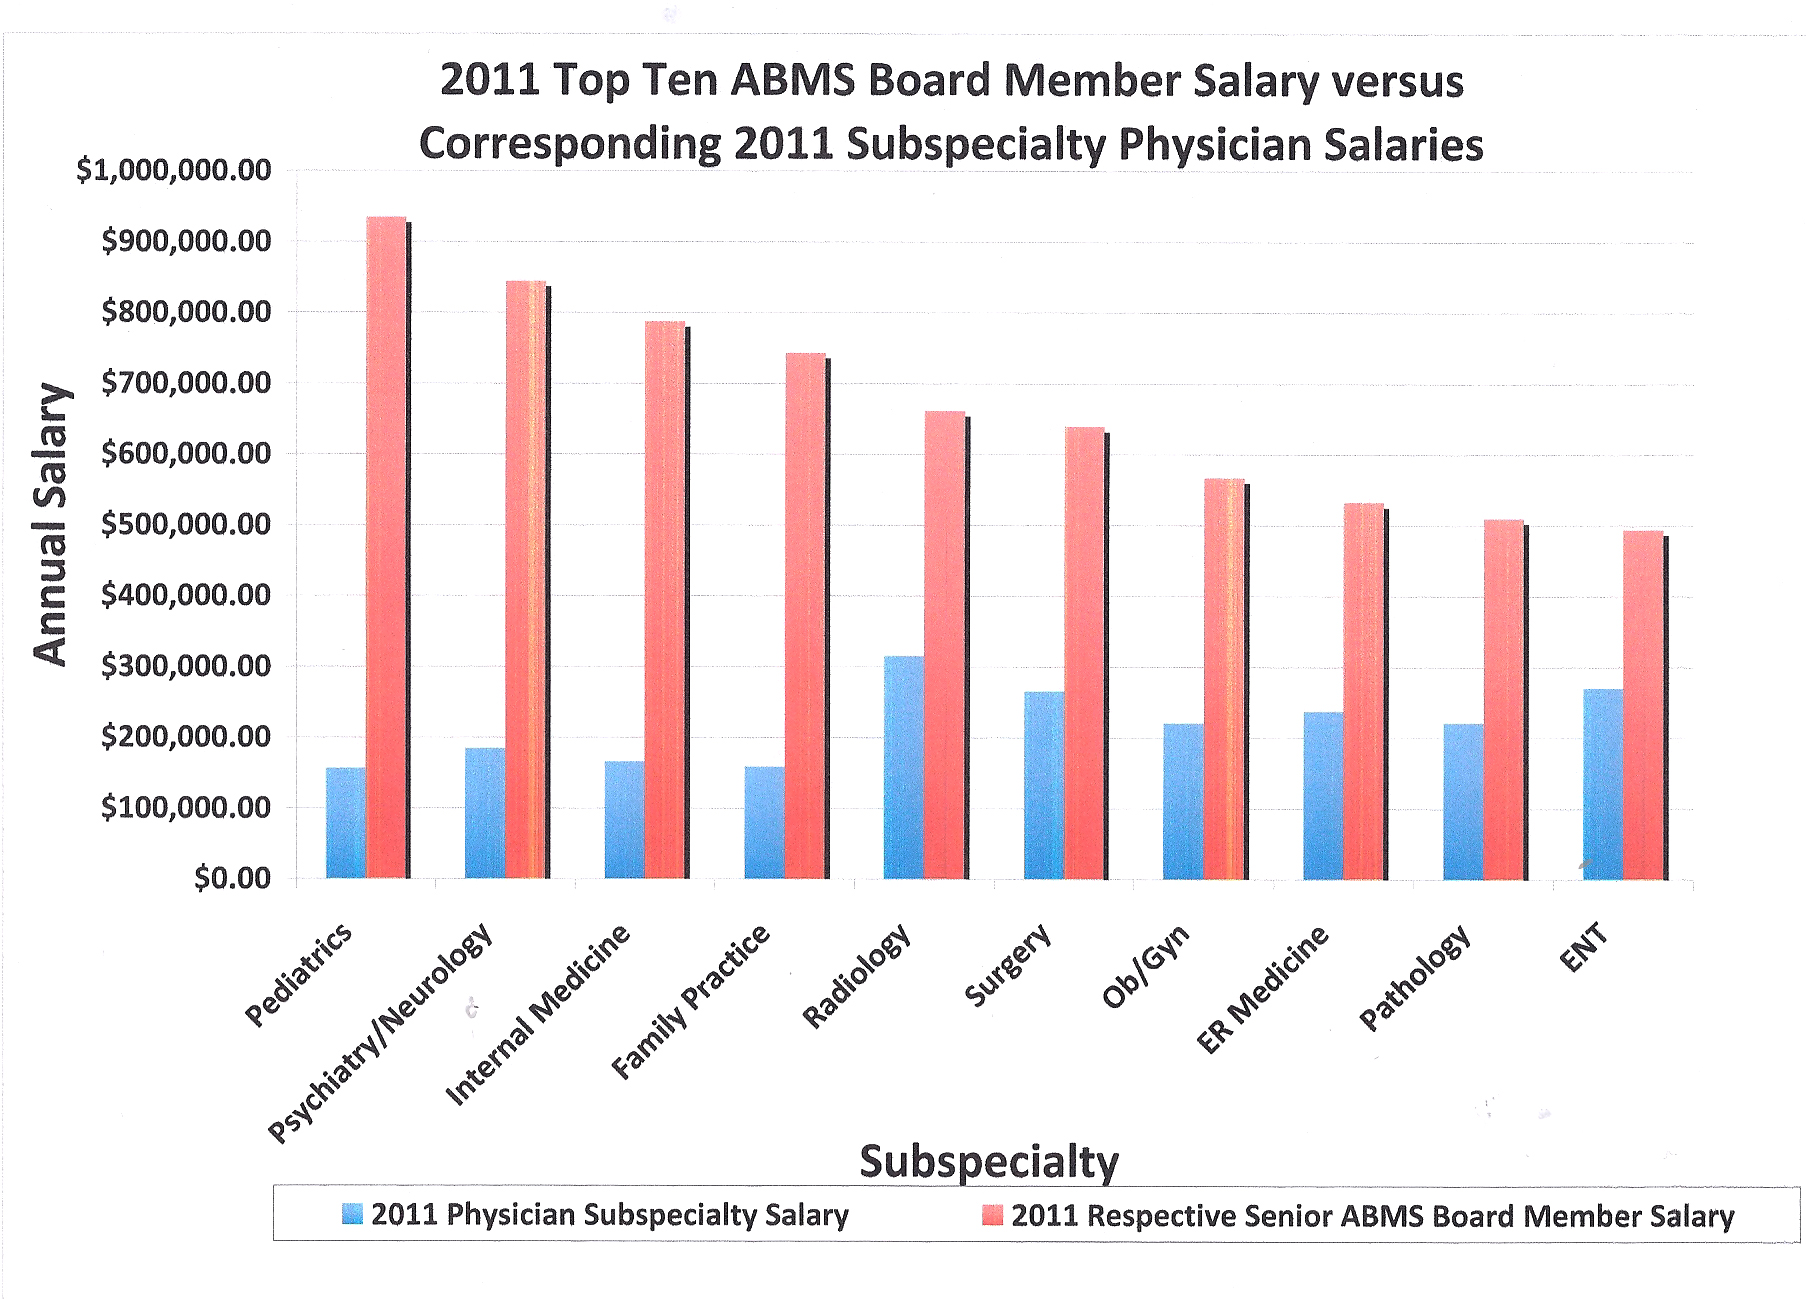 |
| (Click to enlarge) |
Clearly, the US physician credentialing system as it exists now overwhelmingly rewards people with regulatory oversight rather than those who provide patient care. Was this the intent? More specifically, was the intent of the ABIM's "medical professionalism" manuscript to line the pockets of the ABMS member boards in lieu of social justice? What kind of justice is this?
The answer now is not so clear.
To add insult to injury, realize that front-line physicians are increasingly burdened by very high medical school and residency debt for much of their career. As part of their rite of passage into their subspecialty, they must pay the credentialing fees that pay the salaries of these regulators. Should we insist our doctors pay such high fees to support these expensive salaries? How might patients be affected, especially when they have reduced access to doctors who must undergo repetitive certification and re-certification exercises. How do patient's benefit when the certification process appears so flawed?
To me, it seems that we are not seeing a definition of "medical professionalism" in the credentialing juggernaut that these private organizations have created.
We're seeing the definition of "greed."
-Wes
PS: Physicians are welcome to print out the pdf of 2011 ABMS Board members' salaries to share with colleagues and to sign the petition to stop the new onerous biannual MOC recertification requirements.
Thursday, May 01, 2014
Who's In?
“If you understand, things are just as they are; if you do not understand, things are just as they are.”
― Zen Proverb
Today, the clock strikes one: One May, 2014. Today, doctors who failed to enroll in the ABMS Maintenance of Certification (MOC) process will wear the scarlet letter of "Not Meeting MOC Standards" on the American Board of Medical Specialities' CERTIFICATION MATTERS™ website (provided you register on the website and follow the ABMS Terms of Use Agreement).
Just a few days ago, on 28 April 2014, the American Board of Internal Medicine refused to change their policy of requiring physicians to enroll in the MOC process and pay "$200-400" per year to the ABIM despite a petition signed by over 11,800 board-certified physicians who felt the frequency of participation to be expensive and excessively complex and called on the ABIM "to recall the changes in MOC and institute a simple pathway consisting of a recertification test every ten years."
Despite this request from over 11,800 board certified physicians, they refused to budge on their every-two-year MOC requirement.
So at least we know where the American Board of Internal Medicine stands.
But where do the other member boards stand? Do they stand with practicing board certified physicians or do they stand with regulators who continue to heap more unnecessary busywork of uncertain value on already stretched physicians? We should understand that the threat to physicians and our profession is much more severe, especially when MOC is increasingly tied to hospital credentialing and doctors' ability to earn a living. The MOC pass rate for internists was only 78% in 2013.
Today, each member board of ABMS has a unique opportunity to demonstrate their solidarity with the practicing board-certified physicians of their subspecialty. Each member board should publish a statement regarding the MOC petition circulated by physicians on their websites and where they stand on the issue, just as the American Board of Internal Medicine did. Subspecialty physicians deserve a response.
Nietzche once wrote, " Hope is the evil of evils because it prolongs man's torment." What we need in the face of what Nietzche calls "a strict, hard factuality" is a clear view of the playing field. When physicians are feeling increasingly anxious and unclear who truly represents them, we need to have "courage in the face of reality."
Here's a list of the 24 member boards of the American Board of Medical Specialties:
- The American Board of Allergy and Immunology
- The American Board of Anesthesiology
- The American Board of Colon and Rectal Surgery
- The American Board of Dermatology
- The American Board of Emergency Medicine
- The American Board of Family Medicine (NOTE: new anti-MOC petition drive underway)
- The American Board of Internal Medicine (posted statement)
- The American Board of Medical Genetics
- The American Board of Neurological Surgery
- The American Board of Nuclear Medicine
- The American Board of Obstetrics and Gynecology
- The American Board of Ophthalmology
- The American Board of Orthopaedic Surgery
- The American Board of Otolaryngology
- The American Board of Pathology
- The American Board of Pediatrics
- The American Board of Physical Medicine and Rehabilitation
- The American Board of Plastic Surgery
- The American Board of Preventative Medicine
- The American Board of Psychiatry and Neurology
- The American Board of Radiology
- The American Board of Surgery
- The American Board of Thoracic Surgery
- The American Board of Urology
-Wes
Tuesday, April 29, 2014
ABIM Thumbs Its Nose at Senior US Physicians
Yesterday, the President and CEO of the American Board of Internal Medicine (ABIM), in a moment that must have been heartbreaking for him, found himself in the position of having to chasten more than 10,000 unruly senior US physicians, thanks to a petition drive. In his statement, the aggrieved Dr. Baron, in a plea for common sense, bemoans the fact that physicians do not care enough about patient care or safety to spend $200-400 dollars per year for the ABIM. This is what the benighted ABIM is up against! Senior physicians are nothing more than penurious whiners who fail to be appreciative of the Mothership.
For those cynics out there might cast a jaundiced eye on the image of the ABIM as the Mothership, let's not forget the sterling flotilla that the Mothership floats with. Recall that the ABIM rides in the wake of the American Board of Medical Specialities (ABMS). Recall that both the ABIM and ABMS arose from the shipyard of the Amedican Medical Association (AMA) that produces the trademarked CPT procedure codes that Electronic Medical Record industry celebrates. Recall that Dr. Baron hails from the Center for Medicare and Medicaid Services. Recall that the former president of the ABIM, Christine Cassells, had an exemplary friendship with Premier, Inc, a North Carolina company that provides group purchasing and performance improvement consulting for an alliance of 2,900 hospitals and Kaiser Foundation Health Plans and Hospitals. With these kind of credentials, physicians should trustingly take their hands off the policy rudder and know that their profession is secure.
How could doctors doubt the purity of the Mothership? Given their tireless efforts on the behalf of physicians and our patients, we should, in fact, be holding a fund-raising drive for the ABIM! How can we be unsympathetic to the responsibility and burden of reimbursing the ABIM's necessary expenses, such as Doctor Baron's $800,000 annual salary or the bottom line of their testing agency? Don't doctors know that they are singlehandedly preserving the integrity of our specialties and subspecialties that the rest of us would squander willy nilly?
I'd like to reassure President Baron. It appears we've reached a tipping point. Physicians are starting to understand the need for active advocacy in protecting our patients and our medical profession. Disturbingly for the current regime who have commandeered the dignity of practicing physicians for their own benefit, there are appear to be heavy seas ahead.
-Wes
For those cynics out there might cast a jaundiced eye on the image of the ABIM as the Mothership, let's not forget the sterling flotilla that the Mothership floats with. Recall that the ABIM rides in the wake of the American Board of Medical Specialities (ABMS). Recall that both the ABIM and ABMS arose from the shipyard of the Amedican Medical Association (AMA) that produces the trademarked CPT procedure codes that Electronic Medical Record industry celebrates. Recall that Dr. Baron hails from the Center for Medicare and Medicaid Services. Recall that the former president of the ABIM, Christine Cassells, had an exemplary friendship with Premier, Inc, a North Carolina company that provides group purchasing and performance improvement consulting for an alliance of 2,900 hospitals and Kaiser Foundation Health Plans and Hospitals. With these kind of credentials, physicians should trustingly take their hands off the policy rudder and know that their profession is secure.
How could doctors doubt the purity of the Mothership? Given their tireless efforts on the behalf of physicians and our patients, we should, in fact, be holding a fund-raising drive for the ABIM! How can we be unsympathetic to the responsibility and burden of reimbursing the ABIM's necessary expenses, such as Doctor Baron's $800,000 annual salary or the bottom line of their testing agency? Don't doctors know that they are singlehandedly preserving the integrity of our specialties and subspecialties that the rest of us would squander willy nilly?
I'd like to reassure President Baron. It appears we've reached a tipping point. Physicians are starting to understand the need for active advocacy in protecting our patients and our medical profession. Disturbingly for the current regime who have commandeered the dignity of practicing physicians for their own benefit, there are appear to be heavy seas ahead.
-Wes
Monday, April 21, 2014
Paid NEJM Subscriptions: There's No Such Thing As A Free Lunch

Now, I'm not so sure.
New conflict of interests between the NEJM and my hospital have arisen that make me question the wisdom of this policy of free subscriptions provided to doctors, not only our institution, but all other medical centers that offer such an free subscriptions to their medical staff. As they say, there's no such thing as a free lunch.
Especially when the lunch being served supports tying Maintenance of Certification to maintaining doctors' hospital privileges.
On 7 April 2014, the New England Journal of Medicine launched their NEJM Knowledge+ website, a product of the NEJM Group, a division of the Massachusetts Medical Society, that breathlessly markets their own costly version of preparing for the ABIM's MOC process to their readership. A tiny sliver of their exhaustive marketing even promotes the use of their product during the few remaining non-medical hours of a physician's day:
"Whenever you’ve got a moment to lean back and reflect, Internal Medicine Board Review is there with you — whether it’s in line at the supermarket, in the parking lot while waiting for your child’s soccer practice to let out, or during an unplanned minute between patients."Seriously?
Never is there a mention what NOT passing the ABIM MOC testing means to doctors and their families. Never is mentioned that since the advent of MOC re-certification, the financial reserves of the ABIM and ABIM Foundation have increased substantially; in 2006 and 2007, the ABIM transferred $13 million to its "foundation." Never is there a mention that reserves of this magnitude demand accountability to physicians upon which their system has been foisted without any unbiased scientific evidence of its merits. Never is there a mention of the cozy financial relationship that exists between Area9 Labs (the manufacturer of the NEJM Group's new Knowledge+ website), McGraw-Hill publishing, and the NEJM. Never is mentioned how Area9 distributes and markets the web-based physician learning data it collects on the Knowledge+ website.
Most of all, there is never a mention of the ABIM's unrelenting efforts to link their MOC process to doctors' hospital privileges and their ability to practice their trade - hence where my concern with the conflict of interest exists when hospitals and medical centers purchase the NEJM free of charge for their physicians. Hospitals don't need to buy into this manipulation of their staff. Almost every medical group has mechanisms to acquire continuing medical education for their staff that are open and not restricted to the ABIM's costs and onorous re-certification process. By purchasing paid subscriptions to the NEJM, are our hospitals supporting the ABIM's proprietary, self-mandated and scientifically unproven educational process that ties passing a test to the maintenance of hospital privileges?
It is very troubling that the NEJM Group has decided to ally with the ABIM in its MOC efforts. The ABIM leadership continues to exist under a non-transparent and unethical conflict of interest policy. The ramifications of the conflicts that existed with former and current members of the ABIM leadership are only now coming to light. This leaves the ABIM's professional credibility seriously in question with physicians. Is the money that the NEJM Group receives from doctors of all levels of training on their Knowledge+ website worth the damage to their credibility as they ally with the ABIM?
It seems so. After all, the NEJM seems more concerned about its educational subscription fees than the ethics and scientific integrity of the training process they're promoting.
Because of the clear and present danger that the promotion of the ABIM's MOC process presents to physicians' reputations and their ability to practice sound medicine, I recommend immediate termination of free paid subscriptions to the NEJM for physicians at our institution and others like it until the NEJM Group abandons its support of the ABIM's highly-flawed and manipulative MOC process.
After all, the conflict of interest problems inherent to this cozy institutional arrangement between the ABIM, NEJM Group, and the nation's hospitals far exceed anything that existed when pharmaceutical representatives supplied doctors with free pens.
-Wes
Sunday, April 20, 2014
Smile Because She Happened
- Ted Geisel (Dr. Seuss)
It seems just yesterday she came to us, quiet, silky, trusting, needing just a finger to rest her head upon. Unwavering trust. Unconditional love. There in the morning yearning to go with us. There in the evening, excited to greet us at the end of our day. She was there before the iPhone and stayed true to us after. She was the only dog my kids have ever known.
Dogs are a wonderful addition to a young family. Ours taught us the meaning of devotion. She taught our young kids the meaning of love. She knew what we were thinking before we said a word. When sad, she'd offer her head upon our lap; when happy, she'd show her unbounded joy by quivering her adorable stunted tail at a rate that none of us could fathom. She would defend us against cement lawn ornaments that startled her, and threaten cats and squirrels fearlessly, as if we shouldn't put up with their misbehavior.
Her black tender nose saved the day more than once. Perhaps her greatest moment was the day the family hedgehog was lost in the back yard during a brief moment of inattention. The anxiety and family search party, despite their best efforts could not find the little creature. But there, wagging happily, was a little dog pointing at a spot in the ground cover. Beneath her, a hedgehog. And with that, tears of joy and another family crisis averted.
Her love of tennis balls, like life itself, evolved over the years. At first she'd chase them darting across the lawn in a burst of enthusiasm. Who knew such a simple toy could engender such joy? Then, as the years went by and her cataracts took her sight from her, she'd find their scent buried deep amongst thick bushes or hostas, wagging victoriously as she spirited them back home like treasures to store in our living room. Once there, she'd lie on the floor with the ball between her legs, then shove the ball forward with her nose as if to say, 'Come play!" We roll it back between her legs, and she'd shove the ball back to us over and over again in a game of blind dog catch.
Slowly, gradually, her hearing left her too, but her trusty nose would allow her to find her way, tail wagging all along. We'd come home, the head would raise, the tail would wag, and our presence would be acknowledged as she had so many times before - quietly, graciously, and with a tender heart.
Now we are gathered for Easter, seeing her breathing quicken, even at rest. We have to lift her to her favorite spot on our couch on occasion. She's not as hungry at mealtimes now. We know our time with her is short, but our lessons from her will last a lifetime.
And we can be happy. Really happy.
That she happened to our grateful family.
Happy Easter.
-Wes
Friday, April 04, 2014
The Business of Testing Physicians
If you want to understand the world of professional board certification, it is important to understand the business and politics of testing professionals. Such testing is big business. So big in fact, that huge international media and education companies that trade on the New York Stock Exchange have been created to service this need. According to one article on Reuters from 2012, "the entire education sector, including college and mid-career training, represents nearly 9 percent of U.S. gross domestic product, more than the energy or technology sectors."
Part of the expense of "maintaining" one's professional board certification goes for fees for the testing center where the computerized testing occurs. Because cardiac electrophysiologists must hold two board certificates (Cardiac EP and Cardiology), we must pay for two rounds of test-taking fees: the first is included with our cardiology maintenance of certification (MOC), then we must pay a second $750 testing fee for the second EP test. (Each test contained 180 questions - $4.17 per question). I am assuming almost all of this goes to the company that administered my test: Pearson VUE.
ABIM holds a contract with Pearson VUE, a professional testing subsidiary of Pearson Education, the North American subsidiary of Pearson, PLC (NYSE: PSO) - an 9 billion dollar British corporation that claims it is the largest commercial testing company and education publisher in the world. It boasts Penguin Random House publishing and the Financial Times Group as some of its other far-reaching subsidiaries. Mr. John Fallon is the 52 year-old Chief Executive Officer of Pearson, PLC and earns a cool $2.55 million dollars annually while holding 282,147 shares of Pearson stock and plently of stock options. He is joined by Mr. William T. Ethridge, age 62, who serves as "advisor" currently, but was previously responsible for the North American Educational Division of Pearson. According to one source, William Ethridge was once chief executive of Pearson's North American Education division in 2008. According to Forbes, his total compensation in 2011 was $1,390,000 and he held a half million shares of Pearson stock at that time.
Pearson VUE states it "is built on a foundation of experience in electronic testing." My experience with Pearson VUE was parodied in an earlier blog post. As I reflect, it seemed that Peason VUE was more concerned about storing my biometric palm scans and a digital photograph as much as they wanted to assure a fair testing environment. While the ABIM discloses this process on their website, doctors unaccustomed to such paranoid security measures are caught off-guard by these tactics and should be concerned about how this information is stored and used. Are previously-certified doctors really this sketchy?
Pearson VUE earns a pretty penny from its professional testing and its physician testing in particular. According to Pearson's most recent SEC filing:
Doctors should understand how and where their money and personal information are being used in the ABIM's MOC testing process, since much of those funds seem to support the corporations and political aspirations of those who are doing the testing rather than the needs of patients that the ABIM is pretending to protect.
-Wes
Part of the expense of "maintaining" one's professional board certification goes for fees for the testing center where the computerized testing occurs. Because cardiac electrophysiologists must hold two board certificates (Cardiac EP and Cardiology), we must pay for two rounds of test-taking fees: the first is included with our cardiology maintenance of certification (MOC), then we must pay a second $750 testing fee for the second EP test. (Each test contained 180 questions - $4.17 per question). I am assuming almost all of this goes to the company that administered my test: Pearson VUE.
ABIM holds a contract with Pearson VUE, a professional testing subsidiary of Pearson Education, the North American subsidiary of Pearson, PLC (NYSE: PSO) - an 9 billion dollar British corporation that claims it is the largest commercial testing company and education publisher in the world. It boasts Penguin Random House publishing and the Financial Times Group as some of its other far-reaching subsidiaries. Mr. John Fallon is the 52 year-old Chief Executive Officer of Pearson, PLC and earns a cool $2.55 million dollars annually while holding 282,147 shares of Pearson stock and plently of stock options. He is joined by Mr. William T. Ethridge, age 62, who serves as "advisor" currently, but was previously responsible for the North American Educational Division of Pearson. According to one source, William Ethridge was once chief executive of Pearson's North American Education division in 2008. According to Forbes, his total compensation in 2011 was $1,390,000 and he held a half million shares of Pearson stock at that time.
Pearson VUE states it "is built on a foundation of experience in electronic testing." My experience with Pearson VUE was parodied in an earlier blog post. As I reflect, it seemed that Peason VUE was more concerned about storing my biometric palm scans and a digital photograph as much as they wanted to assure a fair testing environment. While the ABIM discloses this process on their website, doctors unaccustomed to such paranoid security measures are caught off-guard by these tactics and should be concerned about how this information is stored and used. Are previously-certified doctors really this sketchy?
Pearson VUE earns a pretty penny from its professional testing and its physician testing in particular. According to Pearson's most recent SEC filing:
"Professional testing continued to see good revenue and profit with growth test volumes at Pearson VUE up 25% on 2012 to almost 12 million [pounds] ($19.9 million). Key contract renewals included tests for the American Board of Internal Medicine, the Association of Social Work Boards and the Pharmacy Technician Certification Board. "But profitting from physician education is a politically hot topic, too. Not surprisingly, Pearson Education seems quite active in this space spending $2,100,000 to lobby Washington during the last presidential election cycle in 2011 and 2012, contributing 7:1 to the Democratic side of the political aisle. Also, 6 of the eight current Pearson lobbyists have previously held government jobs.
Doctors should understand how and where their money and personal information are being used in the ABIM's MOC testing process, since much of those funds seem to support the corporations and political aspirations of those who are doing the testing rather than the needs of patients that the ABIM is pretending to protect.
-Wes
Thursday, April 03, 2014
Mandrola: A Time-Out for ABIM MOC Mandate
From theheart.org (registration required), John Mandrola, MD calls for a "time-out" for the American Board of Internal Medicine's (ABIM) Maintenance of Certification (MOC) mandate:
Some additional thoughts and suggestions to the ABIM:
Just sayin'-
-Wes
Here's a link to an anti-MOC petition underway.
The matter for debate is whether the ABIM method - and to be frank, it's arm-twisting tactics - is the best means to achieve physician quality.Read the whole thing.
Doctors are taught to be skeptical of evidence. Here, there is simply no evidence to judge. We can't know whether this brand of medical education achieves improved patient outcomes. Maybe it will. Maybe it will not. Or, perhaps it could make it even worse. How could aggressive education and measuring quality make things worse? Think heart-failure metrics and an 89 year old, who, a week later presents with a broken hip from all those evidence-based pills. I have many more examples, but I promised brevity.
Some additional thoughts and suggestions to the ABIM:
- Given the unproven nature of the MOC process to assure physician quality and the ethical breeches created by the ABIM's proprietary process, "board certification" as defined by the ABIM should revert to a lifelong certification to put the ABMS and its subsidiaries in competition with all the CME sources available.
- The new ABIM MOC rules that are now set to go into effect 1 May 2014 can cause "sudden and unanticipated" revoking of Board Certification based on failure to completely comply with MOC at ANY TIME. This should not be permitted.
- Since state medical boards are all headed by physicians, the marketing my the American Board of Medical Specialties and the ABIM that physician perform their MOC process to prevent government agencies from providing an alternative to their MOC process is pure propaganda. There are many many government and private agencies that monitor physician performance including hospitals, insurance companies, CMS, Medicare, Medicaid, trial lawyers, the Better Business Bureau to name a few.
- The ABIM's "board certification" is based on test-taking ability and not patient care metrics. As such it cannot be considered a patient care quality measure of any kind and should not be tied to CMS Physician Quality Reporting System (PQRS) payments to those who care for Medicare patients.
Just sayin'-
-Wes
Here's a link to an anti-MOC petition underway.
Monday, March 31, 2014
ACC14: The Quickening Pace of Change
I just returned from the American College of Cardiology and wanted to write down a few of my 50,000-foot impressions from the meeting for, as the song goes, the times, they are a-changin'.
First, while I don't know the overall attendance at the meeting, there really appeared to be fewer attendees. Interestingly, the outside-the-US contingent seemed strong, but by comparison, the US presence at the meeting seemed much lighter (no facts to support this, just my impression).
The pharmaceutical and medical device displays seemed awkwardly overdone. Gigantic displays, lots of sales people standing around, with really not much to do. The amount of money these companies spend to attract doctors in an era when doctors really aren't the purchasers of this stuff anymore, seems crazy - like they haven't gotten the memo. And for goodness sakes, pharma needs to understand how bad it looks when they're charging $6 a pill to our patients on novel oral anticoagulants and they've got these bulls**t displays. Either tone it down, or cut your price… er, never mind: do both.
Surprisingly, I never saw a single model walking on a regular treadmill - a standard at every cardiology meeting I have ever attended. What this means, I'm not sure. Perhaps the ACC has matured to realize that women cardiologists are a growing force, or (more likely) the advertisers understand that no one cared about regular treadmills (they don't make any revenue) and are sick and tired of standing in from of them at work.
RFID tracking seemed larger than ever. Little scanner doomajiggies were all over the place to track us wherever we went, that is, of course if we agreed to have one in our badge. (I was happy to see that the ACC respected by wishes not to have the RFID in my badge, and none was there). One thing that several doctors noticed (and I confirmed): they really didn't care if you had your badge on UNTIL you went to the expo floor, showing what really matters, I guess.
I had the great pleasure of meeting and chatting with a few fellows from across the country and around the world: New York, Massachusetts, North Carolina, California, China, China, and China. These younger folks were cool, but clearly lamenting that it might not be one they participate in much longer. For the most part, most of them were there on much of their own nickel. I quickly polled them to inquire about the annual stipend they receive from their institutions for these things, and the numbers I heard were quite low: from $1500 to $2500. Between cuts to doctors' income and low expense stipends, it is no wonder more and more physicians are staying away - kind of sad for doctors, sure, but really sad for these bright, eager residents and fellows. One is starting to wonder how many more years such expensive sessions will continue.
The other big thing that I noticed at this meeting: not much was scientifically new. It was striking. Think about it: the big trials were a trial on TAVR, a few talks on Mitra-clip, renal denervation, cardiac resynchronization, and pericarditis. Maybe the PCSK9 inhibitors that drop LDL substantially in folks with familial hypercholesterolemia were novel, but that one's not really my bag… It just seems that the of innovation in US medicine has taken a pause. Even in the posters: meta-analyses of old big trials seemed to outnumber and new big trials. It's different now. The cuts are real.
Finally, there was an important first at the meeting. I was impressed that the topic of social media in medicine was given it's own real, live session with it's own central room at #ACC14. I was even more amazed they invited me. After all, I haven't exactly ingratiated myself with the College lately. To their credit, however, they are giving folks like you and me a place to learn about and a platform to promote what I believe to be an important tool for physicians in the years ahead. For that, I am truly grateful. We are, after all, are all professionals all doing this crazy work of medicine together. We may not agree at times, but I think we all want to improve the system for our patients' sake, and social media is a very powerful way to affect change, act collectively, vet ideas, and improve our health care system for the better. Industry, too, is learning from doctors and patients as they use social media to critique, explain, and promote ideas and tools for better patient care. Sure there will be bumps. Sure there will be disagreements. And change may not come right away. But more more often than not, with enough collective voices reaching some compromise, there will be effective change for the better. Seriously, where else can we get value like that?
So to the ACC leadership and all the great people I had the chance to meet, discuss, learn from, share ideas with, thank you. It was a blast.
-Wes
First, while I don't know the overall attendance at the meeting, there really appeared to be fewer attendees. Interestingly, the outside-the-US contingent seemed strong, but by comparison, the US presence at the meeting seemed much lighter (no facts to support this, just my impression).
The pharmaceutical and medical device displays seemed awkwardly overdone. Gigantic displays, lots of sales people standing around, with really not much to do. The amount of money these companies spend to attract doctors in an era when doctors really aren't the purchasers of this stuff anymore, seems crazy - like they haven't gotten the memo. And for goodness sakes, pharma needs to understand how bad it looks when they're charging $6 a pill to our patients on novel oral anticoagulants and they've got these bulls**t displays. Either tone it down, or cut your price… er, never mind: do both.
Surprisingly, I never saw a single model walking on a regular treadmill - a standard at every cardiology meeting I have ever attended. What this means, I'm not sure. Perhaps the ACC has matured to realize that women cardiologists are a growing force, or (more likely) the advertisers understand that no one cared about regular treadmills (they don't make any revenue) and are sick and tired of standing in from of them at work.
RFID tracking seemed larger than ever. Little scanner doomajiggies were all over the place to track us wherever we went, that is, of course if we agreed to have one in our badge. (I was happy to see that the ACC respected by wishes not to have the RFID in my badge, and none was there). One thing that several doctors noticed (and I confirmed): they really didn't care if you had your badge on UNTIL you went to the expo floor, showing what really matters, I guess.
I had the great pleasure of meeting and chatting with a few fellows from across the country and around the world: New York, Massachusetts, North Carolina, California, China, China, and China. These younger folks were cool, but clearly lamenting that it might not be one they participate in much longer. For the most part, most of them were there on much of their own nickel. I quickly polled them to inquire about the annual stipend they receive from their institutions for these things, and the numbers I heard were quite low: from $1500 to $2500. Between cuts to doctors' income and low expense stipends, it is no wonder more and more physicians are staying away - kind of sad for doctors, sure, but really sad for these bright, eager residents and fellows. One is starting to wonder how many more years such expensive sessions will continue.
The other big thing that I noticed at this meeting: not much was scientifically new. It was striking. Think about it: the big trials were a trial on TAVR, a few talks on Mitra-clip, renal denervation, cardiac resynchronization, and pericarditis. Maybe the PCSK9 inhibitors that drop LDL substantially in folks with familial hypercholesterolemia were novel, but that one's not really my bag… It just seems that the of innovation in US medicine has taken a pause. Even in the posters: meta-analyses of old big trials seemed to outnumber and new big trials. It's different now. The cuts are real.
Finally, there was an important first at the meeting. I was impressed that the topic of social media in medicine was given it's own real, live session with it's own central room at #ACC14. I was even more amazed they invited me. After all, I haven't exactly ingratiated myself with the College lately. To their credit, however, they are giving folks like you and me a place to learn about and a platform to promote what I believe to be an important tool for physicians in the years ahead. For that, I am truly grateful. We are, after all, are all professionals all doing this crazy work of medicine together. We may not agree at times, but I think we all want to improve the system for our patients' sake, and social media is a very powerful way to affect change, act collectively, vet ideas, and improve our health care system for the better. Industry, too, is learning from doctors and patients as they use social media to critique, explain, and promote ideas and tools for better patient care. Sure there will be bumps. Sure there will be disagreements. And change may not come right away. But more more often than not, with enough collective voices reaching some compromise, there will be effective change for the better. Seriously, where else can we get value like that?
So to the ACC leadership and all the great people I had the chance to meet, discuss, learn from, share ideas with, thank you. It was a blast.
-Wes
Sunday, March 30, 2014
Is Maintenance of Certification Our Next Tuskegee?
“An experiment is ethical or not at its inception, it does not become ethical post hoc – ends do not justify means. There is no ethical distinction between ends and means.”
-- Henry K. Beecher, MD
New Engl J Med 274(24) June 16, 1966 pp 1354-1360.
“For the most part, doctors and civil servants simply did their jobs. Some merely followed orders, others worked for the glory of science."
-- John Heller, Director of the Public Health Service's Division of Venereal Diseases
The Tuskegee syphilis experiment was an infamous clinical study conducted between 1932 and 1972 by the U.S. Public Health Service to study the natural progression of untreated syphilis in rural African American men who thought they were receiving free health care from the U.S. government. The Public Health Service started working with the Tuskegee Institute in 1932. Investigators enrolled in the study a total of 600 impoverished sharecroppers from Macon County Alabama. Three-hundred ninety-nine (399) of those men had previously contracted syphilis before the study began, and 201 did not have the disease. The men were given free medical care, meals, and free burial insurance, for participating in the study. They were never told they had syphilis, nor were they ever treated for it. According to the Centers for Disease Control, the men were told they were being treated for "bad blood", a local term for various illnesses that include syphilis, anemia, and fatigue.
The 40-year study was controversial for reasons related ethical standards, primarily because researchers knowingly failed to treat patients appropriately after the 1940s validation of penicillin as an effective cure for the disease they were studying. Revelation of study failures by a whistleblower led to major changes in U.S. law and regulation on the protection of participants in clinical studies. Now studies require informed consent, communication of diagnosis, and accurate reporting of test results.
The Tuskegee Syphilis Study led to the 1979 Belmont Report and the establishment of the Office for Human Research Protections (OHRP). Importantly, it also led to federal laws and regulations requiring Institutional Review Boards for the protection of human subjects in studies involving human subjects.
Fast forward thirty-five years.
Could the new American Board of Internal Medicine (ABIM) mandate for participating in their Maintenance of Certification (MOC) process unilaterally imposed 1 January 2014 so they can maintain a publicly-reported maintenance of certification "status" be violating ethical standards set forth by the 1979 Belmont Report?
Let me explain why I think it does.
The increasingly complicated test- and survey-taking exercise called "Maintenance of Certification" has never been scientifically proven to improve physician quality. Our society's inability to agree on a definition of a "quality" physician (and how to measure those qualities) is part of the reason why this issue has never been studied. For instance, should we define a "quality" physician on the basis of his or her empathy, surgical skill, lack of complications, ability to recall facts or some combination of these or other attributes? The reality is, it is nearly impossible to adequately define a "quality" physician at the outset.
But the issue of maintaining "quality" health care delivery is critical to those paying for health care services (CMS and insurers, aka, "stakeholders"), especially now in this era of health care reform. Payers want to assure they receive the most value for their dollars spent in health care. Patients want to be reassured that they are receiving competent care by a physician, especially in a time where cost-cutting, deployment of unproven electronic medical systems, use of non-physician care-givers, and shortened physician training and work hours has occurred. Seeing an opportunity, the American Board of Medical Specialties (ABMS) and the ABIM stepped in to help the government define physician quality. Through the assurances of their leadership, the ABIM led "stakeholders" to believe that (1) quality is easy to measure (after all, they have a thorough testing "process") and (2) the responsibility for determining physician quality should rest with individual physicians. This leap of faith by government officials is similar to the Tuskegee era when government physicians were similarly obsessed with African American sexuality, believing that the responsibility for the acquisition of syphilis rested solely upon the individual.
Because the Maintenance of Certification process imposed by the American Board of Internal Medicine is unproven, it is, at best, an experiment that attempts to assure physician quality on patients without a defined hypothesis (what, really, does the ABIM test with the MOC process?) or informed consent. The issue of informed consent is critical, in my view, because the psychological, financial, and social consequences of NOT passing the test to doctors and their patients have never been evaluated.
 |
| The "MOC Complex" at ACC2014 (click to enlarge) |
First, I learned that the pass rate this year (2013) for internal medicine specialists was 86%, and for cardiac electrophysiologists was 84%. This means that fourteen percent of internists and sixteen percent of cardiac elecrophysiologists did not pass their test. (We were assured that 97% "ultimately" pass, however, but no data were supplied to the audience to this effect).
The second thing I learned directly from Dr. Baron yesterday during the question and answer period was this: the ABIM has never studied the psychological, social, or financial impact that NOT passing the MOC process upon physician test-takers. This is not a small issue, especially if one considers that many hospitals are beginning to tie the ongoing Maintenance of Certification process to the issuance of hospital privileges to practice medicine. How could anyone trained in the ethics of scientific study and research permit such an egregious oversight to the protection of physicians?
From the 1979 Belmont Report:
The expression "basic ethical principles" refers to those general judgments that serve as a basic justification for the many particular ethical prescriptions and evaluations of human actions. Three basic principles, among those generally accepted in our cultural tradition, are particularly relevant to the ethics of research involving human subjects: the principles of respect of persons, beneficence and justice.Let's examine each of these principles described in the Belmont Report in regards to MOC testing.
Regarding respect for persons:
Respect for persons incorporates at least two ethical convictions: first, that individuals should be treated as autonomous agents, and second, that persons with diminished autonomy are entitled to protection.Today, physicians are "persons with diminished authority" in the certification and licensure discussion. The decision to invoke every-two-year testing was imposed by leadership of several physician organizations whose leadership have had strong ties to government agencies (including the Center for Medicare and Medicaid Services, a la Dr. Baron) without the approval of their membership. Further, the MOC process is already being used by some hospitals as a lever to dispense hospital privileges without proof that the MOC process assures physician quality, however might have been defined.
Regarding beneficence:
Persons are treated in an ethical manner not only by respecting their decisions and protecting them from harm, but also by making efforts to secure their well-being. Such treatment falls under the principle of beneficence. The term "beneficence" is often understood to cover acts of kindness or charity that go beyond strict obligation. In this document, beneficence is understood in a stronger sense, as an obligation. Two general rules have been formulated as complementary expressions of beneficent actions in this sense: (1) do not harm and (2) maximize possible benefits and minimize possible harms.Given the fact that the negative consequences of failing to re-certify in medicine are very real for doctors, failing to pass the ABIM's tests may, in fact, harm them. No attempt to minimize harm to physicians has occurred. No attempt has been made to warn physicians about the negative consequences of what might happen to them if they fail to maintain their certification in good "status." Worse still: not allowing physicians to practice medicine may actually harm, rather than benefit, the doctor's patients! The ABMS and ABIM have clearly turned a blind eye to this possibility.
Finally, in regards to the last critical element of the Belmont Report, justice:
Who ought to receive the benefits of research and bear its burdens? This is a question of justice, in the sense of "fairness in distribution" or "what is deserved." An injustice occurs when some benefit to which a person is entitled is denied without good reason or when some burden is imposed unduly. Another way of conceiving the principle of justice is that equals ought to be treated equally. However, this statement requires explication. Who is equal and who is unequal? What considerations justify departure from equal distribution? Almost all commentators allow that distinctions based on experience, age, deprivation, competence, merit and position do sometimes constitute criteria justifying differential treatment for certain purposes. It is necessary, then, to explain in what respects people should be treated equally. There are several widely accepted formulations of just ways to distribute burdens and benefits. Each formulation mentions some relevant property on the basis of which burdens and benefits should be distributed. These formulations are (1) to each person an equal share, (2) to each person according to individual need, (3) to each person according to individual effort, (4) to each person according to societal contribution, and (5) to each person according to merit.So who is served by the Maintenance of Certification process, really? Are patients? Doctors? Or the leadership of ABIM?
Questions of justice have long been associated with social practices such as punishment, taxation and political representation. Until recently these questions have not generally been associated with scientific research. However, they are foreshadowed even in the earliest reflections on the ethics of research involving human subjects. For example, during the 19th and early 20th centuries the burdens of serving as research subjects fell largely upon poor ward patients, while the benefits of improved medical care flowed primarily to private patients. Subsequently, the exploitation of unwilling prisoners as research subjects in Nazi concentration camps was condemned as a particularly flagrant injustice. In this country, in the 1940's, the Tuskegee syphilis study used disadvantaged, rural black men to study the untreated course of a disease that is by no means confined to that population. These subjects were deprived of demonstrably effective treatment in order not to interrupt the project, long after such treatment became generally available.
There are significant financial incentives driving the marketing of the ABIM's ongoing MOC process to America's physicians. From the ABIM's own 2012 Form 990 that I could retrieve, the ABIM earned $30,661,314 from their members for examination fees, $17,509,141 for Maintenance of Certification, and an additional $970,415 for exam development, supplying duplicate certificates, and re-scores of the examination. Of the total revenues reported by the ABIM in 2011 ($49,304,645) fully 48.6% ($23,937,881) went to staff salaries, other compensation, and employee benefits. Christine Cassels, MD alone (who served as President and CEO at the time), earned $786,751 that year and had her spouse's travel fees to meetings thrown in, too. It goes without saying that the leadership of these organizations have received salaries far higher than most of their physician members. Justice (as defined by the Belmont Report) can hardly be served when scales are tipped so heavily toward those of our own profession that stand to benefit so handsomely from this certification process.
It is time that doctors and patients understand exactly what has transpired with the foisting of the ongoing MOC process upon America's physicians. Just as the Tuskegee experiments in Macon County Alabama did years ago, well-meaning members of our profession have represented physician "quality" by their own standards that include the ability to perform a serious of test- and survey-taking exercises without responsibly admitting the harms this process might have on their colleagues and their patients. Like the serious breaches of ethical standards that occurred when doctors worked "for the glory of science" in the Tuskegee era, this unfortunate unproven experiment of MOC re-certification by the ABIM continues unabated without checks and balances.
It is time for this injustice against physicians to stop. Responsible physicians and their patients everywhere need to rise up and demand accountability by the ABIM for their ethical breaches that have occurred. The heavy marketing of the benefit of this process without acknowledging its potential harms is dangerous to both doctors and patients. Further, it is not okay to entrap physicians by making them pay for an unproven process that could destroy their social status and ability to earn a living.
To believe otherwise is about as unethical as it gets.
-Wes
P.S.: Here's a link to an anti-MOC petition underway.
Friday, March 28, 2014
Social Media at Scientific Sessions
More and more physicians are entering the social media space - so much so that even our more classic academic physician colleagues are joining in. But there can be challenges that arise at scientific sessions when the old way of professional discourse meets the new way of social media.
Robert A Harrington, MD (Chair, Dept of Medicine, Stanford University, CA) and Clyde W. Yancy, MD, MSc (Northwestern Medical Center, IL) discuss these challenges nicely at theheart.org and offer some interesting insights and tips for doctors, both young and old, as they consider entering the social media space.
-Wes
P.S.: Then again, if you're still unsure how Twitter even works, consider this Twitter primer.
Why Do Most Medical Professional Societies Call Chicago Home?

Why is this?
First, there is the grand-daddy of all physician professional societies: the American Medial Association based at AMA Plaza, 330 N Wacker Drive, Chicago.
Next, there's the American Board of Medial Specialties (ABMS) (who boasts its supervisory role over 24 subsidiary specialty medical societies across the nation, including the American Board of Internal Medicine and the American College of Cardiology among others) that has it's home at 222 North LaSalle Street in Chicago, just blocks away from the AMA building.
Next, there's the little-known Council on Medical Specialty Societies, who also seemed to be concerned with physician "quality" located just across the Chicago river at 35 E. Wacker Drive.
And let's not forget the Acceditation Council on Graduate Medical Education who oversees all graduate medical education in the United States located at 515 North State Street in Chicago.
Makes you wonder why all of these societies are within blocks of each another in Chicago.
Maybe it's so they can have lunch together. Maybe it's because of all of the academic medical centers located here in Chicago who have retiring professors that need a place to land. Maybe it's because of the state's political leanings. Or perhaps it's just because of Chicago's fairly central US geographic location?
One thing's for sure, it certainly isn't because of low real estate prices or low taxes.
-Wes
Saturday, March 22, 2014
ACC's 2014: What's Out There That's New?
I will be attending the ACC 2014 Scientific Sessions this year in Washington, DC. Theheart.org has a nice post covering some of the early highlights of the conference (sorry, registration required).
But I'm going to try something a bit different this year. Call it self-indulgence. I'm going to try all my might to pull my head out of the corporate weeds for a while and look to my colleagues and start-up friends to see where the innovation in health care is going, not where we've been. After all, MADIT CRT, TAVR (Corevalve included), renal denervation (SYMPLICITY-3), colchicine in pericarditis (CORP 2 Trial), and 3-year results of bariatric surgery are, well, not exactly cutting edge.
I need to get back to my roots more. While I'm a doctor, I'm also a biomedical engineer, a social media nerd, and a guy who loves innovation and creativity in medicine. I want to discover new ideas, new people. I want to discover those who want to attack the colossal challenges patients will have in health care delivery in the years ahead with new and innovative strategies for cardiovascular disease or cardiac arrhythmia management. I want to connect with those who want to upend the status quo. I want to wander around in the swamp of creativity instead of being led lock-step toward more marketing spin.
Am I crazy? Does such a venue exist at this years' ACC Scientific Sessions?
We'll see.
-Wes
(If you'd like to connect or have something that's really cool that might be interesting to discuss over breakfast or lunch one day, shoot me an e-mail at wes - at - medtees dot com or message me via Twitter at @doctorwes . Please, no marketing pitches.)
But I'm going to try something a bit different this year. Call it self-indulgence. I'm going to try all my might to pull my head out of the corporate weeds for a while and look to my colleagues and start-up friends to see where the innovation in health care is going, not where we've been. After all, MADIT CRT, TAVR (Corevalve included), renal denervation (SYMPLICITY-3), colchicine in pericarditis (CORP 2 Trial), and 3-year results of bariatric surgery are, well, not exactly cutting edge.
I need to get back to my roots more. While I'm a doctor, I'm also a biomedical engineer, a social media nerd, and a guy who loves innovation and creativity in medicine. I want to discover new ideas, new people. I want to discover those who want to attack the colossal challenges patients will have in health care delivery in the years ahead with new and innovative strategies for cardiovascular disease or cardiac arrhythmia management. I want to connect with those who want to upend the status quo. I want to wander around in the swamp of creativity instead of being led lock-step toward more marketing spin.
Am I crazy? Does such a venue exist at this years' ACC Scientific Sessions?
We'll see.
-Wes
(If you'd like to connect or have something that's really cool that might be interesting to discuss over breakfast or lunch one day, shoot me an e-mail at wes - at - medtees dot com or message me via Twitter at @doctorwes . Please, no marketing pitches.)
Monday, March 17, 2014
Doctors as Drug Reps
There's a new gig for doctors - as drug rep:
No doubt these doctor drug reps will soon figure prominently as speakers at our upcoming scientific sessions.
God help us.
-Wes
Because they will be employees of Glaxo, the company won’t have to report payments to doctors under the so-called Sunshine Act in the U.S. that requires such disclosures. On the other hand, their credibility may be questioned, and they won’t be able to answer questions such as how they would treat a patient with specific symptoms or problems, given that they aren’t practicing physicians, Khedkar said.Ironically in the same article, a few paragraphs down:
In addition to targeted e-mails and Web seminars, drugmakers are increasingly using mobile platforms including instant replies to questions sent by text message that doctors can use while seeing patients, Khedkar said.Heh. There you have it: another regulatory problem solved.
No doubt these doctor drug reps will soon figure prominently as speakers at our upcoming scientific sessions.
God help us.
-Wes
Sunday, March 16, 2014
How Much Do Doctors Really Earn?
An interesting infographic was recently posted on Sermo (with references noted at the bottom):
I found this infographic interesting for several reasons.
The information puts the high US physician salary touted by the mainstream media and political policy makers in perspective with other countries when time spent providing care is considered.
However, the data presented in this infographic also address the important issue of training debt that currently averages about $300,000 for US physicians (We should note that the 2013 Association of American Medical Colleges report on medical student debt mentions only the "median" debt of medical students: $170,000 - a much more palatable way to spin the truth in favor of our educators.)
So while Congress grapples with the SGR "fix" that is never enforced anyway, there are much bigger issues to consider in regard to physician compensation going forward as the US struggles with its growing doctor shortage.
-Wes
 | |
| (Click to enlarge) |
I found this infographic interesting for several reasons.
The information puts the high US physician salary touted by the mainstream media and political policy makers in perspective with other countries when time spent providing care is considered.
However, the data presented in this infographic also address the important issue of training debt that currently averages about $300,000 for US physicians (We should note that the 2013 Association of American Medical Colleges report on medical student debt mentions only the "median" debt of medical students: $170,000 - a much more palatable way to spin the truth in favor of our educators.)
So while Congress grapples with the SGR "fix" that is never enforced anyway, there are much bigger issues to consider in regard to physician compensation going forward as the US struggles with its growing doctor shortage.
-Wes
Friday, March 14, 2014
Case Study: An Unusual Catheter Course to the Right Atrium
Recently, our laboratory was performing a catheter ablation of paroxysmal atrial fibrillation in a patient with a permanent pacemaker previously implanted from the left axillary venous approach. The fellow placed a decapolar catheter from the left femoral vein, but it took an unusual course to the right atrium. Attempts to place the catheter via a more typical course could not be achieved.
Here are the RAO and LAO fluoroscopic images he saw (labeled for your convenience):
At first, the fellow thought the catheter was extravascular was the catheter passed behind the heart, but continued advancement resulted in the catheter entering the right atrium.
Here's the LAO Cineangiogram of the finding that helped us identify the cause:
Here's the RAO image of the same shot:
What is this? What happened next?
-Wes
PS: If you can't wait, here's a link to a pretty illustration of the anatomy. Note the hepatic drainage to the right atrium is separate from the drainage of the IVC in this anomaly. Here's another link to factoids from the radiology literature regarding this interesting finding.
Here are the RAO and LAO fluoroscopic images he saw (labeled for your convenience):
 |
| RAO Fluoroscopic Image (click to enlarge) |
 |
| LAO Fluoroscopic Image (click to enlarge) |
Here's the LAO Cineangiogram of the finding that helped us identify the cause:
Here's the RAO image of the same shot:
What is this? What happened next?
-Wes
PS: If you can't wait, here's a link to a pretty illustration of the anatomy. Note the hepatic drainage to the right atrium is separate from the drainage of the IVC in this anomaly. Here's another link to factoids from the radiology literature regarding this interesting finding.
Thursday, March 13, 2014
A Quiz: Is Maintenance of Certification Worth It?
Recently, I noted that the Center for Medicare and Medicaid Services (CMS) Physician Quality Reporting System (PQRS) was going to offer an incentive payment of 0.5% beginning 1 January 2014 to doctors who participate in the American Board of Medical Specialties' proprietary Maintenance of Certification® (MOC) process and are in good standing.
I wondered: how much more money does that extra payment from CMS represent for the average physician?
So I decided to do some back-of-the-envelope calculations to see what the investment of hours of studying the ABMS's proprietary materials, test-taking, board review courses, patient survey-taking, and practice improvement studies could garner for the average physician. Is there some real dollar-and-cents value to participating in this process?
To estimate this value, I made some assumptions to simplify the math:
(1) Given the above assumptions, how much more income will the average US male physician earn as a result of their total PQRS payment from CMS each year?
(2) How much does this additional PQRS income represent per patient visit?
(3) In your estimate, is this additional income worth the time spent away from your patients or your family events because of study requirements?
Please show your work (and/or your thoughts) in the comments.
Rest assured you will not be timed on this test nor will you receive any renumeration, CME credit, or MOC credit for your participation in this fun. Rather, it is hoped it helps educate physicians on what they'll be getting for their "required" $194 to $256 fee paid annually to the ABIM.
The first one to answer this quiz correctly will be officially crowned with the invaluable and highly-esteemed Dr. Wes Adminstrative Oversight Award®. (I added the trademark symbol to this fictitious award because I'm sure this exercise will be of great value one day.)
Good luck!
-Wes
PS: In the interest of saving time for my busy colleagues who'd rather cut to the chase, here's a link to my back-of-the-envelope calculations. (Feel free to point out errors in the comments)
I wondered: how much more money does that extra payment from CMS represent for the average physician?
So I decided to do some back-of-the-envelope calculations to see what the investment of hours of studying the ABMS's proprietary materials, test-taking, board review courses, patient survey-taking, and practice improvement studies could garner for the average physician. Is there some real dollar-and-cents value to participating in this process?
To estimate this value, I made some assumptions to simplify the math:
- First, I assumed the Mediscape 2013 average male physician salary in America was reasonably accurate ($259,000/yr) and will not change this year.
- Doctor salary is taxed at a 24% rate after withholdings are considered.
- No time during regular work hours is devoted to performing any MOC requirement.
- The average US male physician works and average of 45 weeks per year, 5 days per week for their total salary.
- The doctors only see Medicare patients.
- Every patient office visit is billed as a 99213 (established patient visit - 15 min). (I know, not realistic, but simple to estimate)
- Doctors work 8AM-12 noon and 1pm-5pm daily, seeing 32 patients per day, every day they work.
- Income medicare pays the physician for each 99213 established patient visit is $69.66 and there is a 100% collection rate
(1) Given the above assumptions, how much more income will the average US male physician earn as a result of their total PQRS payment from CMS each year?
(2) How much does this additional PQRS income represent per patient visit?
(3) In your estimate, is this additional income worth the time spent away from your patients or your family events because of study requirements?
Please show your work (and/or your thoughts) in the comments.
Rest assured you will not be timed on this test nor will you receive any renumeration, CME credit, or MOC credit for your participation in this fun. Rather, it is hoped it helps educate physicians on what they'll be getting for their "required" $194 to $256 fee paid annually to the ABIM.
The first one to answer this quiz correctly will be officially crowned with the invaluable and highly-esteemed Dr. Wes Adminstrative Oversight Award®. (I added the trademark symbol to this fictitious award because I'm sure this exercise will be of great value one day.)
Good luck!
-Wes
PS: In the interest of saving time for my busy colleagues who'd rather cut to the chase, here's a link to my back-of-the-envelope calculations. (Feel free to point out errors in the comments)
Sunday, March 09, 2014
E-Flooded
I have been a way from blogging for a bit - tried to clear my head a bit with a vacation skiing - left the computer at home, disconnected (as best I could), and had the luxury of feeling the knees working less fluidly than they had before, but still had some fun for a brief 3-day stint. It was nice to notice that there's a whole world out there - beautiful mountains, fresh air, nice friends. All things considered, I am pretty lucky to have a stable job, appreciative patients, and a fulfilling career.
But it didn't take long after my return to work for me to feel flooded again. Two days after returning to work, it was like I never left. Perhaps it's like that for most busy folks, but somehow the world of health care delivery feels more frenetic than ever. The in-basket messages, the mountains of results, the re-scheduled patients on top of those already scheduled, the seemingly endless phone and e-mail messages, the late-night consults after a full day of procedures - all demanding time - it's bordering on crazy. I have several nurse practitioners who assist, but the volume of electronic patient care that's happening now is overwhelming to even the most computer-savvy of us doctors.
And all of this communication is not compensated. There are no "RVUs" for answering an e-mail. There are no "RVUs" for speaking on the phone. There are no "RVU's" for typing. No "RVUs" for data entry and clicking a mouse. Physician time means nothing to programmers and policy-makers.
It's a larger symptom, I think, of the new "efficiencies" built into the electronic medical record (EMR) that has become ubiquitous with the world of medicine today. Information flies so fast and there's so much of it that it's getting almost impossible for doctors to keep up with the screen responsibilities, not to mention their care responsibilities. The EMR is no longer just an EMR. The EMR has morphed into a scheduling agent, pharmacy, reminder pad, calculator, care pathway generator, instant-messaging service, a procedure orderer-by-proxy (and guideline) and a patient messaging portal that, aside from a 400-character limit, provides unprecedented access to physician in-boxes and schedules. There are so many buttons that they no longer fit on a single screen and the "allergy" field no longer can be displayed as it's pushed out of the way by the name of the patient's insurer. Add to this the constant and growing influx of patients (thanks to marketing pushes and programs to spur referrals), voluminous administrative meetings, and growing CME requirements, it's no wonder many of us feel flooded. I work later than ever now thanks to these electronic "efficiencies," then find myself waking in the middle of the night wondering: Did I call Ms. Smith? Did I miss something? Did I put that order in? When am I going to do those result notes?
I think I'm suffering from post-traumatic electronic overload disorder (PTEOD).
Oh sure, we could hire another guy or gal to offload some of the work - maybe even hire a wasteful manpower-intensive scribe like those that work in some ERs that click for cash - but that really won't help stem the ongoing barrage of information that is now pummeling physicians and their care teams at an unprecedented rate. Sadly, I don't see this trend changing anytime soon - the business case for the EMR is just too attractive for hospitals and payers. Still, with the prospect of ICD-10 and it's 71,924 procedure codes and 69,823 diagnosis codes (that must be paired correctly lest doctors not be paid) just around the corner, I fear that physician stress, burnout and PTEOD will only increase as we are force-fed this diet of electronic overload without any reflection of what its doing to those who provide the care.
Ugh. I need another vacation.
-Wes
But it didn't take long after my return to work for me to feel flooded again. Two days after returning to work, it was like I never left. Perhaps it's like that for most busy folks, but somehow the world of health care delivery feels more frenetic than ever. The in-basket messages, the mountains of results, the re-scheduled patients on top of those already scheduled, the seemingly endless phone and e-mail messages, the late-night consults after a full day of procedures - all demanding time - it's bordering on crazy. I have several nurse practitioners who assist, but the volume of electronic patient care that's happening now is overwhelming to even the most computer-savvy of us doctors.
And all of this communication is not compensated. There are no "RVUs" for answering an e-mail. There are no "RVUs" for speaking on the phone. There are no "RVU's" for typing. No "RVUs" for data entry and clicking a mouse. Physician time means nothing to programmers and policy-makers.
It's a larger symptom, I think, of the new "efficiencies" built into the electronic medical record (EMR) that has become ubiquitous with the world of medicine today. Information flies so fast and there's so much of it that it's getting almost impossible for doctors to keep up with the screen responsibilities, not to mention their care responsibilities. The EMR is no longer just an EMR. The EMR has morphed into a scheduling agent, pharmacy, reminder pad, calculator, care pathway generator, instant-messaging service, a procedure orderer-by-proxy (and guideline) and a patient messaging portal that, aside from a 400-character limit, provides unprecedented access to physician in-boxes and schedules. There are so many buttons that they no longer fit on a single screen and the "allergy" field no longer can be displayed as it's pushed out of the way by the name of the patient's insurer. Add to this the constant and growing influx of patients (thanks to marketing pushes and programs to spur referrals), voluminous administrative meetings, and growing CME requirements, it's no wonder many of us feel flooded. I work later than ever now thanks to these electronic "efficiencies," then find myself waking in the middle of the night wondering: Did I call Ms. Smith? Did I miss something? Did I put that order in? When am I going to do those result notes?
I think I'm suffering from post-traumatic electronic overload disorder (PTEOD).
Oh sure, we could hire another guy or gal to offload some of the work - maybe even hire a wasteful manpower-intensive scribe like those that work in some ERs that click for cash - but that really won't help stem the ongoing barrage of information that is now pummeling physicians and their care teams at an unprecedented rate. Sadly, I don't see this trend changing anytime soon - the business case for the EMR is just too attractive for hospitals and payers. Still, with the prospect of ICD-10 and it's 71,924 procedure codes and 69,823 diagnosis codes (that must be paired correctly lest doctors not be paid) just around the corner, I fear that physician stress, burnout and PTEOD will only increase as we are force-fed this diet of electronic overload without any reflection of what its doing to those who provide the care.
Ugh. I need another vacation.
-Wes
Monday, March 03, 2014
When Regulators Pay for Peer-review
The ongoing controversy among US physicians over newly-implemented "Maintenance of Certification (MOC)" requirements created by the private organization, the American Board of Medical Specialties (ABMS) and its 24 subsidiary subspecialty boards has breached another ethical front: paying for peer-reviewed publications in support of their expensive and proprietary MOC process.
In the Fall of 2013, the ABMS single-handedly funded an entire supplement devoted to the MOC process in the Journal of Continuing Education in the Health Professions. This journal is published quarterly by the Alliance of Continuing Education in the Health Professions, the Society for Academic Continuing Medical Education, and the Council on CME of the Association for Hospital Medical Education. Not surprisingly, the articles published were uniformly favorable about the MOC process despite evidence to the contrary. The American Medical Association (who also stands to benefit from the process politically) was quick to provide a free link to the full pdf of the supplement from its AMA Wire news bulletin.
Interestingly, the literature review of the MOC process performed by Lipner et al. (page S20 of the supplement) admitted the limitations of their review:
I welcome the ABMS's response regarding their practice of paying for publications in support of the MOC process in the comment section of this blog.
-Wes
In the Fall of 2013, the ABMS single-handedly funded an entire supplement devoted to the MOC process in the Journal of Continuing Education in the Health Professions. This journal is published quarterly by the Alliance of Continuing Education in the Health Professions, the Society for Academic Continuing Medical Education, and the Council on CME of the Association for Hospital Medical Education. Not surprisingly, the articles published were uniformly favorable about the MOC process despite evidence to the contrary. The American Medical Association (who also stands to benefit from the process politically) was quick to provide a free link to the full pdf of the supplement from its AMA Wire news bulletin.
Interestingly, the literature review of the MOC process performed by Lipner et al. (page S20 of the supplement) admitted the limitations of their review:
"First, we did not consider certification by other entities other than ABMS boards; these results may not generalize to other certification bodies. Second, we did not use a formal system to judge the quality of the methodology used in the studies. Third, a meta-analysis to compared effect sizes across different data types was not done; designs were extremely diverse, and it may not be possible with the information available."Given these limitations, the "value" of the MOC process, based on the data, is totally subjective. Despite these glaring limitations, the article concludes:
The main goal of certification is physician accountability to the public (editor: note that the "patient" and "doctor" are not mentioned). We have shown that a substantial body of evidence supports the value of certification and MOC in meeting that goal but the evidence is not unequivocal. In response, the ABMS have begun to enhance their programs to be more authentic and relevant to practice while maintaining their rigor and continuing to study the program's validity."If the way the ABMS "enhances" the value of its proprietary MOC process is to pay for peer-reviewed publications that ignore the serious limitations mentioned by the authors themselves, then those directly impacted by the MOC process (like myself) have an obligation to question the validity and ethics of the ABMS's self-promotional practice.
I welcome the ABMS's response regarding their practice of paying for publications in support of the MOC process in the comment section of this blog.
-Wes
Subscribe to:
Posts (Atom)