Sunday, December 31, 2017

ABMS/ABIM MOC Controversy: 2017 Year-in-Review

As we say goodbye to 2017, we say goodbye to a year of unprecedented exposure of the interconnected workings of the Accreditation Council for Graduate Medical Education and its member organizations, the American Board of Medical Specialties (ABMS), the American Medical Association (ABMS), the American Hospital Association (AHA), the Association of American Medical Colleges (AAMC), and the Council of Medical Subspecialty Societies (CMSS)  that continue to ignore the corruption inside their walls.

Money does that to people. We should not be surprised.

In keeping with the reviews from 2015 and 2016, here is the wrap-up of some of  key events concerning Maintenance of Certification® (MOC®) for 2017:

4 January 2017 - Richard Baron, MD and Clarence H. Braddock,  III, MD publish a promotional article for ABIM in the New England Journal of Medicine and given the comments, probably wish they hadn't.

20 January 2017 - Stationary sidebars can be revealing: The interconnected conflicts of interest with University of California, San Francisco, MOC®, the New England Journal of Medicine, and the ABIM/ABIM Foundation are disclosed.

6 February 2017 - Practicing Physicians of America, Inc is born and requests IRS investigation of the ABIM at the Library of Congress in Washington, DC.

6 February 2017 - TeamHealth eats the Department of Justice's $60 million judgment for Medicare fraud, but is swallowed quietly by Blackstone Group.

17 March 2017 - Federal judge dismissed ABIM's copyright infringement suit against Puerto Rican Dr. Salas Rushford. Salas Rushford's countersuit to proceed.

21 March 2017 - Wallstreet lawyer attempts to attack the integrity of the investigative reporting on this blog concerning the ABIM's Director of Test Security. Rebuttal appears in Pennsylvania Medicine Magazine and becomes the most read blog post of 2017 thanks to the Streisand Effect.

31 March 2017 - ABIM announces their much-anticipated "modifications" to their MOC program, gets it wrong again.

3 April 2017 - State legislative anti-MOC® battles continue in Tennessee

12 April 2017 - Elizabeth's Rosenthal's book An American Sickness appears on the New York Times best seller list, includes reference to the ABIM $2.3 million condo story.

29 April 2017 - The state legislative battle continued in Texas.

3 May 2017 - Journal of the American Medical Association devotes an entire issue to conflicts of interests in medicine, but forgets to disclose its own.

26 June 2017 - Antitrust suit against American Osteopathic Association is allowed to proceed to the discovery phase

30 June 2017 - Anti-MOC legislation in Texas passes with some concessions, goes into effect 1 Jan 2018.

3 July 2017 - Practicing Physicians of America, Inc starts fund drive to assist with anti-MOC legislative efforts.

1 August 2017 - Research letter detailing the costs and fees for Maintenance of Certification® appears in JAMA.

6 Aug 2017 - ABMS responds to JAMA article on MOC® costs as "crucial to sustain and evolve."
18 October 2017 - Why the IRS needs to investigate the ABIM and its numerous corporate conflicts of interest.

11 October 2017 - Ohio legislature receive my testimony and an evidence packet on anti-MOC House Bill 273 regarding the corruption of the ABIM before the Health Committee.

31 October 2017 - ABIM joins the Human Diagnosis project

4 December 2017 - A key meeting of State Medical Societies, ABMS and ABIM leadership, and numerous medical specialty societies convenes to discuss problems with MOC®; admits the MOC® process is "problematic."

13 December 2017 - ABMS and "partners" from other ACGME organizations including the AAMC and CCMS, alongside some select medical specialty societies, announce new "Vision Commission" to re-brand MOC®. More coverup seems inevitable.

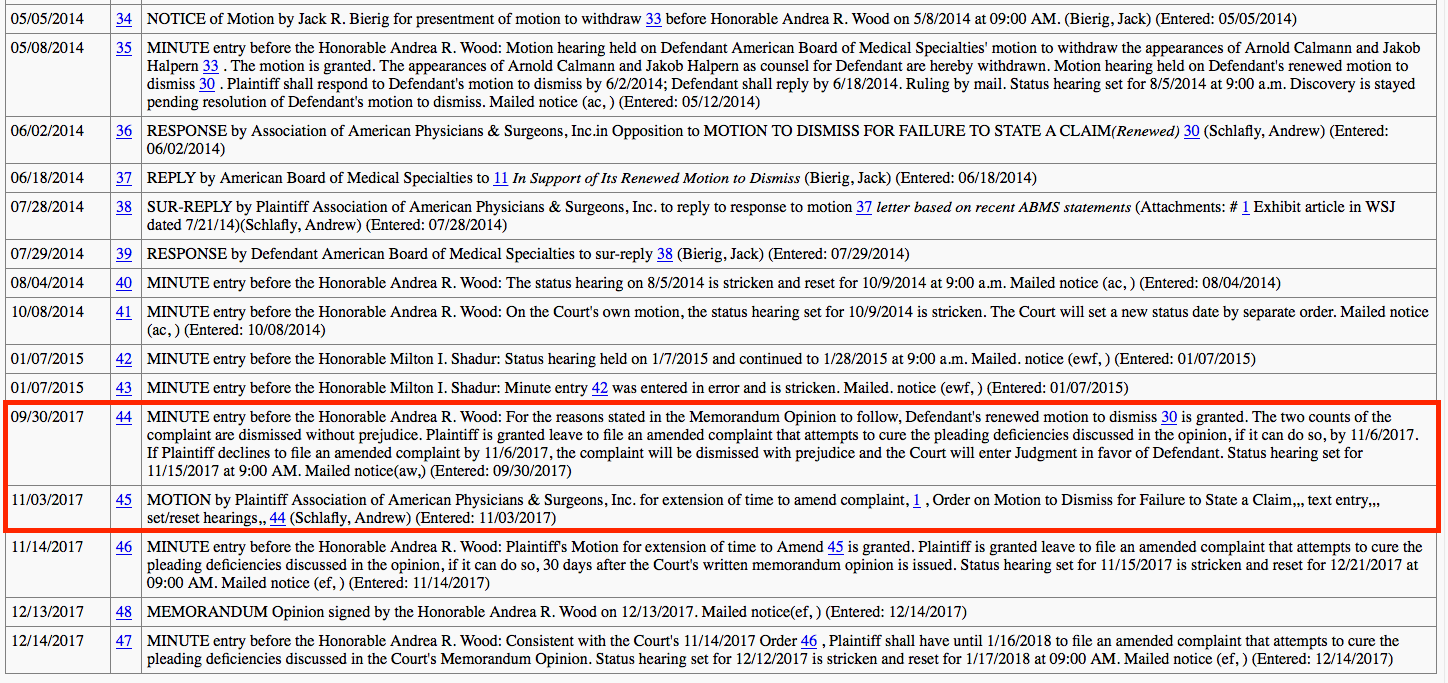
13 December 2017 - Federal judge in the Northern District of Illinois dismisses the antitrust suit by the AAPS against the ABMS using a curious timeline, but leaves a door open to "file an amended complaint that cures the deficiencies discussed in this Memorandum Opinion."

* * *

Today is New Year's Eve. Whether ABIM is solvent or not is uncertain. We will likely have to wait until May of 2018 to know for sure, since 501(c)(3) corporations can file a request to delay publishing of their Form 990 for Fiscal year 2017 until then. But the financial trend toward collapse of the ABIM and ABIM Foundation, legal troubles, and the unannounced closure of divisions within the ABIM, like the Division of Test Security and the Division of Policy in January 2017 give some hints to what is (and has been) going on there.

Bit by bit, real clinic doctors are making a difference in fighting MOC®. I encourage all readers of this blog to consider joining or donating to Practicing Physicians of America or to become certified by the National Board of Physicians and Surgeons to help continue this fight.

Together practicing physicians can make 2018 a successful and prosperous anti-MOC® new year for those of us on the front line of patient care.

-Wes

Thursday, December 28, 2017

AAPS To File Amended AntiTrust Suit Against ABMS

From the January, 2018 AAPS Newsletter:
AAPS Has Leave to Amend ABMS Anti-Trust Suit

The federal court in the Northern District of Illinois has granted leave to AAPS to provide more detail as to how Maintenance of Certification (MOC®) harms patients in AAPS v. American Board of Medical Specialties, 14-cv-2705-ARW (N.D. Ill. Dec. 13, 2017). Because antitrust laws exist to protect consumers, not competitors, the court is requiring further specificity as to the harm to patients that is allegedly inflicted by MOC®.

In addition, the court wonders whether the American Board of Medical Specialties (ABMS) and other MOC-related organizations have any control over insurance companies to require MOC® as a condition of participating in their plans. To the extent anyone is aware of a specific relationship between ABMS and insurance companies, or a mechanism by which ABMS may have some influence with insurers, then please let AAPS know.*

AAPS plans to add to its allegations ways in which representations made by ABMS and board-certifying societies harm physicians who decline to participate in MOC®. (emphasis mine) In the past some board-certifying societies have posted disparaging statements about physicians who do not waste the substantial time and money on remaining current with onerous MOC® requirements. For now, the court considers some of these pro-MOC® statements to be mere opinion, which is not actionable, but AAPS can submit stronger examples of unfair disparagement with its upcoming amended complaint.

This legal struggle is far from over, and AAPS observes that earlier this year a district court in New Jersey held there is a valid claim for an antitrust violation by how membership in the American Osteopathic Association is required as a condition of maintaining certification by D.O.s.

The AAPS case was initially filed in New Jersey in 2013 (https://tinyurl.com/ycndp3rx), and the courts have not acted until now, except to grant an ABMS motion to change the venue to Chicago. In dismissing the case as pled, the Court focused on the “voluntary” nature of MOC®. It had not been demonstrated that ABMS has sufficient market power to restrain trade, decrease output, or raise prices. “Antitrust laws protect competition, not competitors” (https://tinyurl.com/yapc4no5). Patients can supposedly find another doctor, or another hospital — somewhere.
-Wes

* AAPS should look no further than Blue Cross/Blue Shield of Michigan's disenrollment of Meg Edison, MD from several insurance panels and then sending her patients letters about the disenrollment solely on the basis of her failing to pay her Maintenanance of Certification fee. Their near instantaneous electronic collusion with an ABMS member board (American Board of Pediatrics) is damning and is facilitated by the for-profit wholly-owned subsidiary of ABMS, ABMS Solutions, LLC (domiciled in Atlanta, GA) selling Board certification status to third parties. AAPS should also be interested that Margaret O'Kane of the National Committee on Quality Assurance (that sets credentialing standards for insurers) is also a public member of the ABMS Board of Directors.

Tuesday, December 26, 2017

The Curious Timeline of the AAPS vs ABMS AntiTrust Ruling

It was almost Christmas, and you could hear the collective sigh of relief rising from the leadership at the American Board of Medical Specialties (ABMS). The antitrust suit brought against them by the Association of American Physicians and Surgeons (AAPS) was dismissed without prejudice on 13 December 2017 with one small caveat, "AAPS will be permitted an opportunity to file an amended complaint that cures the deficiencies discussed in this Memorandum Opinion."

Whether the legal team of the AAPS will decide to amend the complaint remains to be seen, but much has been learned about the anti-competitive nature of the ABMS Maintenance of Certification (MOC) program since the time that suit was filed. No longer is the coordination of effort of the MOC program limited to an arrangement between the Joint Commission of Accreditation of Hospital Organizations and the ABMS member boards, but its tentacles extend to most of the membership organizations of the Accreditation Council for Graduate Medical Education (ACGME), the huge medical publishing companies (Wolter Kluwer and Reed Elsevier), many of the state medical societies like the Massachusetts Medical Society and their NEJM Group, the IPC Hospitalist Company (later purchased by TeamHealth, that was later bought by the mysterious Blackstone Group after the DOJ found them guilty of Medicare fraud), the international medical community in far-away places like Qatar and Venice, Italy (which have separate "standards" for Board certification), and even influence on our own local state legislatures.

This is because we now understand that nearly 20% of our nation's economy (and much of our current academic medical system, each with their lucrative medical subspecialty societies) depends on ABMS MOC program succeeding. MOC is one of the critical keys to unlocking the data mine of physician behavior, purchasing, and influence via a HIPAA Business Associate Agreement that supplies the digital data fuel for the economic engine of health care today. An alternative to MOC without such an agreement would hurt this digital gravy train.

But working physicians subject to the demands of MOC saw the program for what it was: a sickening power play using threats and intimidation to fund the ACGME monopoly and the ABMS Member Board largess at their expense.

So those same working physicians took it upon themselves to start their own competing board, the National Board of Physicians and Surgeons. They took their concerns to state legislators and won a few key battles. By doing so, they exposed how insurance companies and hospital systems didn't really like that competition. They especially didn't like how physicians were coordinating their efforts. And somehow, along the way, those efforts have now piqued the interest of a few lawyers from the Federal Trade Commission.

But the inner political workings of our court system need scrutiny, too.

Recall that the 2013 AAPS suit was moved from New Jersey to the Northern District of Illinois (the AMA's back yard) in 2014 at request of lawyers from the AMA. Once there, the case docket had plenty of activity until January 2015, but then laid dormant for years.

This did not stop the ABMS from declaring victory in the case on their website October 2, 2017. How did they know? More than two months before the Memorandum Opinion was issued by Judge Andrea R. Wood, it seems the ABMS knew something the AAPS lawyers did not. The court docket also revealed how the court dismissed the case before the Memorandum Opinion could be reviewed by AAPS attorneys. Perhaps this is usual and customary behavior by the courts, but given the gravity of the ruling and its implications to working physicians nationwide, working doctors want to know how the ABMS leadership knew of the case's outcome before the ruling was even issued. Do the tentacles of MOC extend to the courts, too?

While the ruling is disappointing to most working US physicians, all is not lost. Not by a long shot.

Thanks to the work of a committed group of working physicians who have raised the interest of federal regulators, MOC suddenly appears "problematic" for the ACGME. A new "Vision Commission" for "Continuous Board Certification" is being organized by the ABMS comprised of the same cohort of conflicted medical bureaucrats that created MOC in the first place.

Look at that "planning group's" membership:
Nowhere in this list of "planners" are real frontline working physicians. And given this, nowhere is there likely to be any real change to the MOC system going forward.

Lipstick on a pig by another name is still a pig. And no matter what this commission has planned as they delay and distract from the corruption that has occurred with MOC for the past 30 years when they issue their "findings" in 2019,  MOC will remain a corrupt, broken educational product with serious conflicts of interest that needs to end now, not later.

-Wes

Friday, December 15, 2017

ABIM Promotes Nurse Practitioner As Quality Physician

Things must be really bad for the American Board of Internal Medicine (ABIM).


Since the organization has completely lost the trust of frontline working physicians, they are now now turning to nurse practitioners to promote their certification products - all at real working physician expense!


Spend a moment and watch the good "doctor and nurse practitioner" Susan Apold, PhD, ANP promote nurse practitioners as equals to physicians on national TV:


Caveat emptor.

-Wes

Wednesday, December 13, 2017

It's Official: MOC® is Dead. Let the Cover-up Begin

It's official: MOC is dead.

You heard that correctly doctors, the American Board of Medical Specialties' Maintenance of Certification® (MOC®) program is over, finished, kaput.

The one thing that resonated loud and clear from the December 4th meeting in Chicago of the multiple specialty societies and state medical societies that were in attendance was "the current MOC® process is problematic."

But don't get too excited.

In a remarkably Orwellian twist of fate, a new "vision initiative" to reinvent "Continuing Board Certification" was just announced by the original MOC® creators serving as the "Planning Committee."
The Planning Committee is comprised of representatives from the Accreditation Council for Continuing Medical Education (ACCME), Accreditation Council for Graduate Medical Education (ACGME), Coalition for Physician Accountability, Council of Medical Specialty Societies (CMSS), Council on Medical Education (CME) of the American Medical Association (AMA), the public, and the American Board of Medical Specialties (ABMS).

Jo Buyske, MD, ABMS/ABS
Sandra Carson, MD, CMSS/ACOG
Joyce Dubow, Public Member
Jack Evans, Public Member
Larry Green, MD, ABMS/ABFM
Thomas Hess, JD, ABMS
Lynne Kirk, MD, AMA CME
Graham McMahon, MD, ACCME
Thomas Nasca, MD, ACGME
John Prescott, MD, AAMC & Coalition
Stephen Wasserman, MD, ABMS/ABAI
Steven Weinberger, MD, CMSS/ACP
Norman B. Kahn, Jr., MD, CMSS, ex-officio
Lois Margaret Nora, MD, ABMS, ex-officio
You just can't make this stuff up.

We now see the ABMS and their sycophants at the ACGME, AMA, American College of Physicians, CMSS, and American College of Surgeons taking nominations for 21 to 25 individuals to serve on the planning Commission. This Commission will "bring together multiple stakeholders to assess the current state of continuing board certification and vision its framework for the future. ... Specialty societies, state medical societies, academic medical centers, hospitals and health systems, other health care systems, consumer organizations, patient advocacy organizations, ABMS member boards, and other groups are encouraged to submit nominations."

This is not rebranding.

This is not just a "pivot" to a new model.

This is an attempted cover-up.

Unless and until there is a full investigation of wrongdoing of these institutions regarding MOC®, including, but not limited to, potential tax fraud, misuse of physician testing fees for personal use, civil liberties violations, strongman tactics, and even possible racketeering, the current "vision initiative" should not be allowed to go forward, lest it happen again.

After all, medical professionalism demands accountability and many, many doctors want to see justice served.

-Wes

Addendum: Nice to see at least one medical society voiced concerns regarding MOC at the December meeting.

Tuesday, December 12, 2017

We Believe the Working Physicians

Lately, it seems we can't go another day and not hear about another individual, once held high as an icon by their adoring followers, falling from their elitist pedestal in shame when revelations of their lewd and morally reprehensible behavior are ultimately exposed. As Elizabeth Nolan Brown of the New York Times astutely observed in response to the prevailing zeitgeist:
Social media takes a lot of punches for enabling sexual harassment. But the past two months have shown that it has also provided consumers with an unprecedented power to make their market preferences heard loud and clear. And right now, the market is demanding that companies do something about sexual predators and pests in their midsts.
I believe a similar movement extends to the regulatory world of academic medicine, too. The anti-MOC (Maintenance of Certification) movement, facilitated in large part by social media unconstrained by medical journals owned by self-adoring academic medical societies, is unlocking the self-locking doors of the Accreditation Council for Graduate Medical Education (ACGME).

This is not to say that all academic physicians are bad people. On the contrary, just like not all journalists and actors are sexual predators, not all individuals in positions of power within the ACGME construct or medical societies are bad people. But power and money do things to even nice people. Some people see how easy it is to take advantage of those less prominent, yet no less important, than they are. The blinding influences of money and power permit morally reprehensible behavior to be ignored by others who also benefit from that behavior but don't say anything. Soon, given an inch, a few influential people in positions of power take a mile and before long, they quietly become pests in US medicine's midst too.

Such has been the story of the ABMS and their member boards since the introduction of time-limited board certification. Using highly respected members of the medical community as their work-a-day pawns, these leaders stroked the egos of their revered physician educator colleagues by providing them first class air fare, accommodations at five-star hotels with dinners at the fanciest restaurants with exquisite wine samplings for test writing junkets as their network of carefully-chosen collaborators grew. In return, the leadership of these organizations were held high as moral icons above reproach as plans were hatched for the next test-writing retreat in Costa Rica. Black tie events at the Four Seasons (or similar venue) reinforcing their behavior for the "common good" of medicine become commonplace. Using these respected adademics as self-adoring apostles of the ABMS  leadership, more like-minded individuals were recruited using this simple formula based on avarice, narcissism, and greed: give economically disadvantaged academic physicians a glimpse of what they could have if they worshipped the materialistic world of the ACGME and these riches could be theirs, too. The host of corporate interests like testing companies, publishers, single payer advocates, pharmaceutical and insurance companies, and every medical supply chain company wanting the selling/purchasing power of physicians in their back pocket would make sure of it.

Soon, ABMS Board certification went from a lifetime credential to a time-limited one quite easily: by the threat of "uncertain consequences" by the boards and their medical society sychophants. Dazed and confused, unsuspecting working physicians were dragged into the PearsonVue testing back offices for "recertification" testing using threats to their character and intellect. Those threats became real as practicing doctors realized their "voluntary" board certification process was no longer voluntary, lest they lose their job if their once specialty certification expired and was no longer considered valid by their employer.

And so it has been for years until a few brave souls came forward and questioned the status quo. Thanks to social media, scores of hardworking physicians are waking to their own #MeToo moment as subjects of extortion, strongman tactics, civil liberty violations, and being used as research subjects without their consent. None of this was done to benefit patients they now realize thanks to social media, but to line the pockets and fund the political agendas of a few influential members of the untouchable medical credentialing cartel.

This new movement has even shown that intimidation of a vulnerable physician work force won't hold back the truth.

It's a new time in corporate America, just like it's a new time for the ACGME.

Not only do we believe the women, we believe the frontline working physicians, too.

-Wes


Wednesday, December 06, 2017

On the December 4 Meeting of the Untouchables

From the invitation-only December 4, 2017 meeting on Maintenance of Certification (MOC®) practicing physicians were not allowed to attend, came this synopsis from Ohio:
Fellow Council members,

The following are my thoughts following the long-anticipated MOC® meeting in Chicago. An official report that will be distributed to the general membership will follow.

The meeting was hosted by the American Society of Anesthesiologists in Schaumburg, IL. The auditorium designed to hold 150 people, was filled to standing room only.

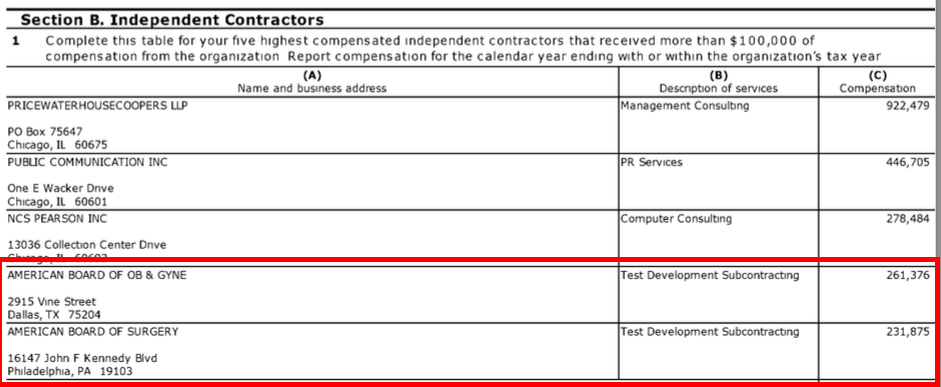
A bit of background, this meeting was the brainchild of Donald Palmisano, Jr., CEO Medical Society of Georgia, and Hal Lawrence III, MD (Executive Vice President and CEO) ACOG. (Editor's note: The American College of Obstetrics and Gynnecology (ABOG) are subcontractors for "Test Development" with the ABMS.) During the interim and annual meetings at the AMA, the state and specialty societies meet. It was during this meeting in Chicago that the idea for today's meeting was formed.

Dr. Lois Nora, current President and CEO of the American Board of Medical Specialties spoke first. In her 20-min remarks, she acknowledged each of the points raised in the letter penned by the state and specialty societies. Dr. Nora's term ends on December 30, 2017. Her successor is Richard E. Hawkins MD, who is leaving his position as Vice-President of Medical Education at the AMA to take this position.

Her Key Points:
  1. Committed to improving continuing certification
  2. Add state society representation to the Committee on Continuing Certification
  3. Admits that the current MOC® process is problematic
  4. MOC® should not be used as the only criteria for state licensure, credentialing, or employment
  5. Agrees that professional self-regulation is valuable
  6. Asked that the states not support anti-MOC® legislation (citing possible unintended consequences)
Summary of the comments from state and specialty society representatives:


  1. Physicians insist on trust, input, transparency, and improved communication from the boards
  2. Create a process that is developed with us not forced upon us
  3. Process should not be punitive. Use the carrot and not the stick
  4. MOC is an irrevocably tarnished brand
  5. Following initial certification, the high stakes exam should be only one of several options
  6. Create a process that is fair to physicians holding more than one certification
  7. Several specialties have already implemented processes that offer ongoing demonstrations of competency as an alternative to the high stakes exam.
  8. Two specialty societies (Family Medicine and Psychiatry) stated that they were considering up thir own boards as a solution
  9. Anesthesia was the only specialty that admitted that reducing the burden on physicians had a negative effect on their bottom line
  10. Multiple states vowed to continue legislative efforts until tangible efforts in the MOC® process can be seen
  11. Need for dur process for physicians whose ability to work has been adversely affected by inappropriate use of MOC®
  12. The hospitals (AHA) and insurers (AHIP) should be invited to the discussion as they are the entities most likely to use MOC® inappropriately.

Please note that I spoke personally to the organizers of this meeting to request that Ohio be included in future discussions regarding MOC.

Respectfully submitted,

RF Chatman MD, MPH
President, Ohio State Medical Association
It appears the thrust of this "meeting" was to try and get states to NOT pass anti-MOC legislation. It didn't take long for an analysis of the Ohio synopsis to appear in my inbox from one observant physician (printed here with permission):
It seems to me as though this debate has now been quietly and cleverly re-framed in terms of retaining and "improving" (compulsory) MOC®.

Remember, it is only made "compulsory" through collusive "enforcement" by those twin paragons of virtue, the insurance and hospital corporations.

"No more high stakes exams we promise" they cried. The implied subtext being that the obligatory ABMS MOC parasite will remain Ebola-like, in some mutated and quiescent form, and continue to infect us all.

Debating the "character" of MOC® was four years ago. Pretty please. That didn't work. Now the issue is not MOC® but the utter and complete repudiation of ABMS lock, stock, and barrel. (Editor's note: Recall the AMA House of Delegates already voted to do so in June, 2016. We now see the AMA's answer to that resolution: to place physician puppets in position of power at the ABMS to assure their lucrative international medical data mining project grows ever stronger and more valuable.)

MOC® should be in reality just another innocuous and palatable Continuing Medical Education (CME) option, but has become a forced and toxic one. A most profitable and poisonous bubbling brew concocted and fed to us by our "peers in leadership positions." The ABMS have become the very caricature of witches on MacBeth's "blasted heath."
The ABMS and their 24 specialty lackeys should now go off and hawk their wares like any tawdry CME street vendor in the chaotic for-profit "medical education" bazaar. Through their grotesque avarice the ABMS have irreparably tarnished their brand. No physician will ever respect them again. Ever. They are done.

Why on earth does anyone even stoop to converse with the ABMS anymore? It is too late for that. As Texas Medical Association President Carlos J. Cardenas, MD said "Physicians in Texas and across the country... do not see the certifying boards as 'self.' They are, instead, profit-driven organizations beholden to their own financial interests. In fact, they are now one of the outsiders intruding into the practice of medicine."

States should pass their anti-MOC laws, the ABMS and its apologists should be disregarded, and we all should move on.

Why did the state medical societies, which (with very few exceptions) also lack any standing amongst rank and file doctors, even bother to meet with the ABMS?

It is a total charade, a Jersey boardwalk puppet show populated by unrepresentative and self-aggrandizing narcissists lobbying each other. What on earth were they doing, imploring the ABMS on a bended knee to change their wicked ways?

"My" state medical society (sadly not one of the exceptional ones and one having less than 5% of state physicians as members) has no right to negotiate the character of MOC® on my behalf. It is too late for that. The state medical societies have become little more than the mini me's of the hated and corrupt AMA.

The single demand going forward should be to break up the ABMS monopoly and open up the market to competing boards like the NBPAS, recently delineated in an article by an FTC member. Let the physician marketplace decide which boards truly represent their interests. Period.

The hospital and insurer enforcers should be met head on now. Forget the disgraced ABMS. The MOC® debacle has catalyzed the onset of a transformative phase in medicine, one we physicians must be the first to recognize and guide.
Somehow, I didn't think I could improve on this cogent analysis.

-Wes

Sunday, December 03, 2017

When Medical Subspecialty Societies Do Harm

Pediatrician Meg Edison, MD gives her take on her "MOC failure:"
I am a diplomate of the American Board of Pediatrics against my will. I find it morally reprehensible to financially support an organization that harms fellow physicians. I find it demoralizing to know my money supports their lobbying efforts against our state MOC legislation. Yet I paid in order to see my patients. I paid so I could still be a doctor. The American Board of Pediatrics could ask for another $1500 next year, and I’d have to pay again. There is no choice.

Is it possible I was targeted for being so outspoken on MOC? Possibly. My initial letter to the ABP has over 100,000 views. My medical society has used me on the cover of their magazine and their website dedicated to fighting forced MOC. The ABMS Senior Vice President knows me by sight, and has watched me testify against forced MOC in our state capitol on multiple occasions.

But I’ve been contacted by countless quiet Michigan physicians threatened and decredentialed for simply refusing to pay for MOC. It doesn’t matter who you are, an outspoken physician with a state medical society behind you…or a solo practitioner quietly trying to stay afloat…you must comply.

I don’t know the solution to this problem. It seems like every legal, logical, and ethical boundary that should prevent a certifying company from gaining such absolute unchecked power has been ignored, and every professional organization that should help us is impotent.

My state medical society has held clear policy opposing board certification, let alone MOC, for insurance plan participation for 20 years. They’ve been negotiating for 20 years, yet aggressive MOC discrimination continues. The AMA has strong policy opposing MOC abuse, but refuses to do anything. The FTC should see this monopoly as a clear anti-trust violation. They are waking up, but still not acting. I am baffled the IRS doesn’t question the million dollar salaries raked in by these “non-profit” organizations. It seems like this would be a slam-dunk class action lawsuit for some smart law firm, but no one is interested in the case. State legislation is likely our best bet, but the lobbying power of insurers, hospitals, the billion dollar ABMS certification industry and their codependent specialty societies is nearly impossible to fight.

If nothing is done, ABMS will win, because their entire coercive business model relies upon our professionalism. As physicians, we take an Oath to “Do No Harm”. We promise this to our patients.

My first emotion when I heard my patients were forced to receive care in the ER was not anger at ABMS. It was gut-wrenching guilt. I dared to speak. I dared to fight. I underestimated their power. I was stupid enough to think MOC was a physician issue. It never crossed my mind that my patients would be harmed. I know better now. The next time they ask for another check, I will comply, and they know that. I just hope something is done before then. Primum non nicer.
Read the whole thing.

-Wes

Tuesday, November 28, 2017

Despite Known Conflicts, ACC/HRS Endorse MOC

The Heart Rhythm Society (HRS) and American College of Cardiology (ACC), two organizations who stand to gain handsomely from their NCDR procedural registries, published a carefully-worded combined statement on "Lifelong Learning Requirements for Clinical Cardiac Electrophysiology (CCEP) Specialists" in their respective journals this week.

In a glaring ommision, the publication concerned itself with how Relationships With Industry (RWI's) were handled by the authors, but failed to address the many known RWI's of the bodies that "approved" their statement, including the ACCME, ABMS and ABIM. These relationships include the known collusion of the ABIM with CECity, Inc (held by Premier, Inc, the largest hospital purchasing consortium), the Massachusetts Medical Society and its NEJM Group, the multibillion dollar Netherlands publisher and owner of UptoDate, Wolters Kluwer, PearsonVue, and the myriad of test security companies who benefit from the unproven MOC mandate.

These are not minor conflicts.  They strike to the very core of the integrity of our profession and physicians who must place the interests of our patients before all else. Setting the "rules" for lifelong learning is not required, integrity and honesty in dealing with patients is what is needed instead. Those internal principles cannot be simply articulated in the form of a published "guideline."

This blog has carefully articulated the many civil liberties violations and ethical breaches perfomed by the ABIM (all sanctioned by the ABMS and perpetuated by the AMA) for the past four years. Financial cover-ups, tax fraud, HIPAA Business Associate Agreements that are not optional, and the use of a team comprised of a felonious "Director of Investigation", ABIM staff members, and members of the ABIM legal team to obtain physician emails covertly, so they could use that information to discredit and intimidate physicians, are our reality.  Yet the ACC and HRS have decided to turn a blind eye to the corruption because it might disturb their business model.

Using hugely conflicted certifying bodies to certify a professional position statement document is a problem the ACC and HRS have chosen to ignore to their detriment and the detriment of our professional integrity.

-Wes

Monday, November 27, 2017

Thanksgiving 2017 and the Grooming of Physicians

"Fun, flexible, and refreshing way to earn your credit! Take a break from the bird and have your hand at a few."

So said the American Board of Pediatrics' (ABP) Thanksgiving 2017 tweet seen here (now deleted).

As if family time and the true meaning of Thanksgiving mean nothing to the American Board of Pediatrics (ABP). Rather, David G. Nichols, MD, the President and CEO of the ABP, must need to assure his Christmas bonus.

Boasting that "20,000 physicians enrolled in Question of the Week" (QOW), as if there was another option for pediatricians caught in the regulatory capture vice-grip of MOC®, speaks volumes about the motivation of this organization. In fact, the real world reality is that not signing up and paying for "QOW" risks a practicing pediatrician's ability to participate in insurance panels or to maintain their hospital privileges.

The Thanksgiving message from Richard Baron, MD, President and CEO of the American Board of
Internal Medicine, was equally troublesome given the reglatory capture realities of the ABIM's MOC® program, too:
"Thank you for all you do every day."
You're welcome, Rich.

Now tell us, given the spending, financial shenanigans, and legal fees incurred by the ABIM and ABIM Foundation lately, are the ABIM and ABIM Foundation insolvent as at least one accountant suggests?

Given the realities of the ABMS MOC® program that both organizations promote, placating physicians with such messages at Thanksgiving is akin to a child molester grooming his victims to earn their trust; it's about as ethically moribund as it gets.

-Wes

American Academy of Pediatrics "Sets Sail" to Track All US Children

The American Academy of Pediatrics, (aka, "Big Brother") wants to track your children. Physicians who support the program can earn MOC® credits, too:
The Academy has set sail to be the first entity to collect, store and analyze health data on all U.S. children. The board agreed to commit $583,000 in resources from the Tomorrow’s Children Endowment to begin development of a child health clinical data registry, which is expected to unfold over five years. This unprecedented initiative, called Clinical Health Information and Longitudinal Data Registry (CHILD), is the outgrowth of two strategic plan objectives:

Use data and metrics to develop and priori­tize areas of need for child health policies. Provide state-of-the-art pediatric practice information in the context of a changing industry and professional landscape. Data would be captured through electronic health records, integrated health care systems, payers and existing pediatric disease registries. Data elements would include well-child and sick visits, chronic disease diagnosis and management, specialty care, and developmental and behavioral care. The registry also would include a patient portal to allow parents and patients to input data, while alleviating complications surrounding privacy laws.

Christoph U. Lehmann, M.D., FAAP, medical director of the AAP Child Health Informatics Center, and professor of pediatrics and biomedical informatics, Department of Medicine, Vanderbilt University School of Medicine, presented project details to the board, including the following primary goals:

Create substantial improvements in child health and well-being. Accelerate advances in child health. Improve outcomes for children using data. Demonstrate the trajectory of child health through adulthood. Among the benefits of this registry, Dr. Lehmann said, are tracking childhood health and illness trends, which would help draw conclusions on a number of areas, including gaps in care, treatment options and regional variations in care. The data also will help inform the creation of AAP guidelines and policies, and provide guidance to payers.

Members could use the data to help create reports for quality improvement projects, as well as for meaningful use and Maintenance of Certification, Dr. Lehmann said.
What could possibly go wrong?

-Wes

Friday, November 10, 2017

The History of the ABIM Art Collection U.S. Physicians Have Never Seen

They were the glory days; a time when the ABIM was still respected; a time before the World Wide Web and moving diplomate testing fees from the ABIM to a secretly-created shadow "Foundation" could occur below the radar.

John A. Benson Jr., MD and Harry R Kimball, MD were the first two Presidents of the ABIM appointed after the bylaws were changed to pay officers salaries. Dr. Benson was the first President of the ABIM from 1975 through 1991 and ran the organization from his home in Portland, OR, leaving his academic and clinical practice for the administrative world of the ABIM save for one long-time physician-patient he kept while serving in that capacity.* Dr. Kimball, his all-too-willing successor from 1991 through 2003, understood the number of doctors being trained was finite and paying executives would be difficult without a new business model. It was Dr. Kimball who conceived of "maintaining" one's board certification through ABIM's Continuing Professional Development (CPD) program to keep the money flowing. But the initially voluntary program flopped as doctors saw the program for what it was: an unnecessary distraction from their busy practices. So CPD would have to become mandatory. His like-minded colleagues at the American College of Physicians (who would also financially benefit) could see to that, and soon money flowed like honey. So much, in fact, that something had to be done with all that money earned by a so-called "non-profit."

It was under Dr. Kimball's direction as ABIM's Chairman of the board from 1989-1990, the ABIM Foundation was secretly created in 1989. Multiple money transfers from the ABIM to the Foundation were made to facilitate lucrative investments with (the now-defunct) 1838 Investment Advisors. For a while, it was a win-win for both corporations. So many trades were made that ABIM paid nearly a quarter of a million dollars annually for their services.

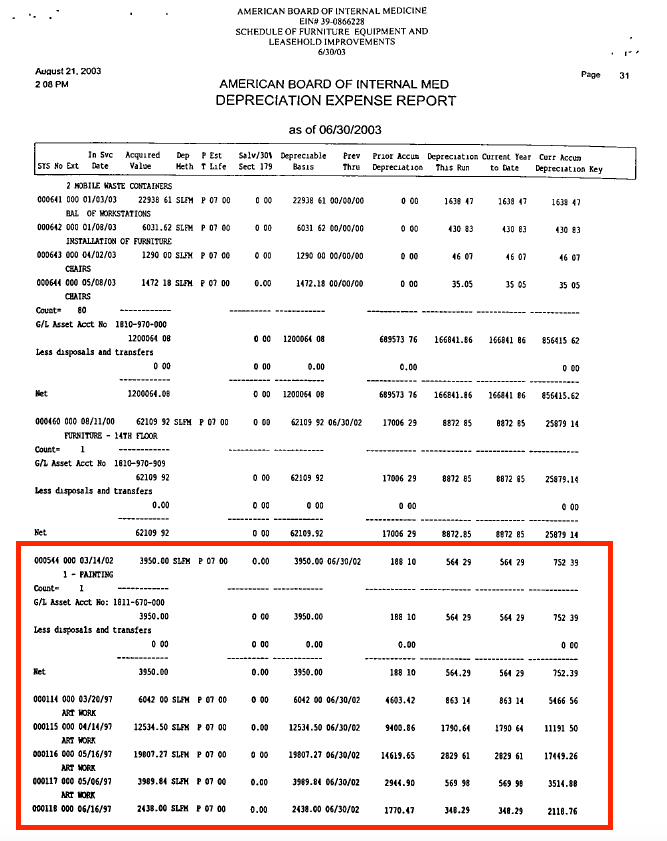
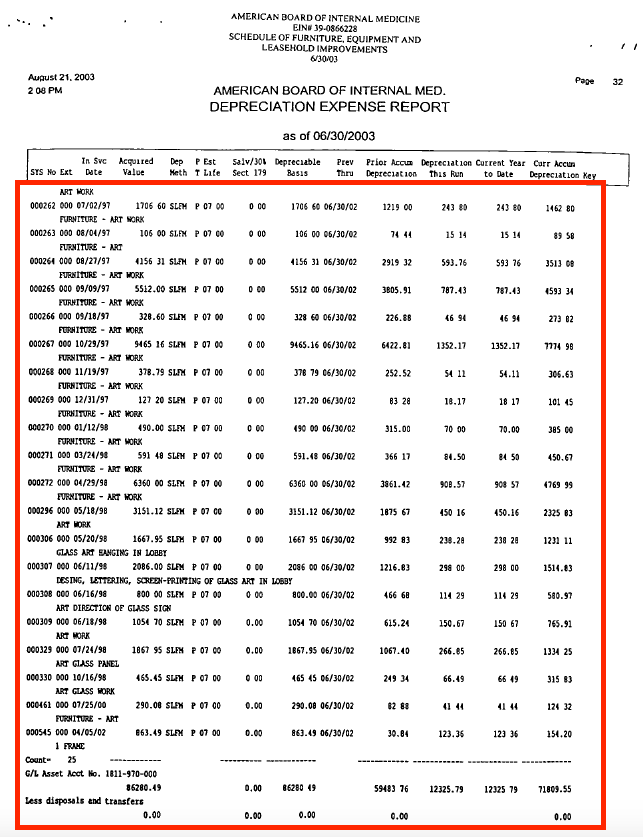
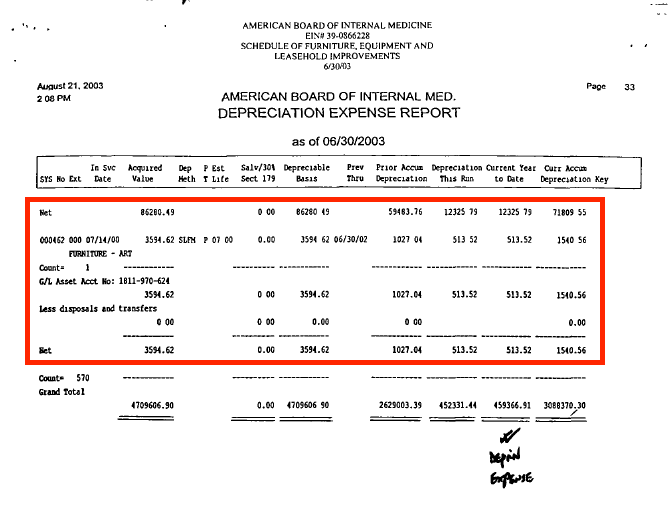
With that money flowing to the ABIM, nearly $90,000 of artwork was purchased for their Walnut Street offices in Philadelphia in 1997 and 1998. We know this because the ABIM offices were later renovated in fiscal year 2003 as the computerized testing age came to Philadelphia. At that time, the value of that art work was disclosed on ABIM's IRS tax forms (see here, here, and here).

In total, it appears $89,874 dollars worth of some kind of art adorns ABIM office walls, thanks to ABIM diplomates. No wonder they "surprised" Dr. Kimball with a black tie event and had the first "Kimball Lecture" in honor of him in August, 2004!

But then 2005 came.

The gravy train ended when 1838 Investment Advisors' fund lost 74% if its value and mysteriously disappeared:
"The silence has been deafening," said one money management executive in the region, who declined to be named. It's as if they "fell off the face of the earth," said a pension consultant, who asked to remain unidentified. One private equity veteran, who declined to be named, said it's unusual for a firm with such a long history to simply disappear. The firm traced its lineage back to Drexel and Co., a banking and investment management firm founded by Francis Drexel in Philadelphia in 1838.
Principles from 1838 Investment Advisors were holdovers from the Drexel Burham Lambert that came under investigation for illegal activities in the junk bond market for stock manipulation. Since that gravy train collapsed, another hopeful investment was made in real estate: a condominum puchase in December 2007.

The ABIM Foundation was never about "medical professionalism" or "Choosing Wisely®." It was a "get-rich-quick" scheme using diplomates' testing fees for the organization's own corporate benefit.

That is, until it wasn't.

-Wes

* Interview with Dr John A Benson, Jr, MD, conducted April 27, 1999, page 18.

Thursday, November 09, 2017

Combating MOC Abuses

Thanks to the Orlando Medical News for their comprehensive coverage Tuesday on the American Board of Medical Specialties' (ABMS) Maintenance of Certification (MOC) scandal.

Physicians' best approach to collapse the current ABMS monopoly on credentialing standards remains mass non-compliance.

Employed physicians (like myself) are finding noncompliance impossible without jeopardizing their employment, since many hospitals require their physicians to be "board certified" in their specialty. Since ABMS no longer "recognizes" lifetime certification as a valid credential (except for older "grandfathered" physicians who obtained their board certification before 1990), younger (more economically vulnerable) physicians risk the loss of employment if they do not participate in MOC and agree to the ABMS's "HIPAA Business Associate Agreement," becoming little more than data entry clerks for the lucrative insurance, pharmaceutical, and hospital industries.

Is this really what our patient's want?

I don't think so. Most patients I know would like to see their doctor look them in the eye rather than at a computer screen. Most want to be viewed as humans rather than a data profit center. And all of them want to spend more than 8 minutes with their physician.

So how do physicians combat MOC? How do we preserve our ability to work without having to make extortion payments to the ABMS and their member boards just for their political and personal benefit?

The fight against MOC continues on many levels, but it is a long, difficult, and expensive David-vs.-Goliath battle:
  1. The development of an alternate certification board that is affordable and does not require physicians to comply with the ABMS/ABIM HIPAA Business Associate Agreement and comprised of highly-respected unpaid members of the physician community who understad the conflicts of interest inherent to the ABMS member board construct and is gaining acceptance hy hospitals accross the country.

  2. State-by-state legislation efforts outlawing the use of MOC as a condition of insurance panel participation, hospital privileges, or state licensure.

  3. Persuing other legal avenues, including anti-trust and class action suits against members organizations of the Accreditation Council for Graduate Medical Education, among others.

I would encourage employed physicians who are given a professional stipend from their hosptial systems for professional society memberships to seriously consider using some of those fees to join Practicing Physicians of America in lieu of other conflicted professional and subspecialty organizations as we continue to push back against the MOC mandate (an example of to testimony and evidence provided the Ohio Health Committee here). Other areas to contribute include becoming certified by NBPAS or contributing to their advocacy efforts. It costs nothing to join the Facebook group Physicians Working Together, too. That group offers lots of productive ideas on how we can work collectively to restore the integrity of our profession.

It is only through a corrodinated effort from a large portion of the working physician community that our freedom to truly work in our patient's best interest without unnecessary and unproven third party interference can be restored.

-Wes

Wednesday, November 01, 2017

The Hidden Message Coming From the AMA

This morning I received a press release from the American Medical Association (AMA) that said "New AMA Research Finds One in Five Physicians Ready to Reduce Clinical Work Hours." The press release pointed to "new research" (sorry, it's behind a pay wall) that appeared in the Mayo Clinic Proceedings from "experts" from the AMA, Mayo Clinic and Stanford University. The lead author of the research was Christine A. Sinsky, MD of the AMA.

But what Dr. Sinsky fails to disclose in her article in the Mayo Clinic Proceedings, is she is also a Director of the American Board of Internal Medicine (ABIM) and a member of the Board of Trustees of the ABIM Foundation, serving as the Vice Chair. This is not a minor lapse in disclosure, since the ABIM Foundation and the entire national Maintenance of Certification debacle may become one of the largest medical education corruption stories in modern medical history. Funneling over $78 million dollars for ABIM testing fees behind physicians' backs to fund the ABIM Foundation appears of little importance to Dr. Sinsky. She is more concerned about our psychologic well-being rather than the behavior of the Foundation she runs with our Maintenance of Certification (MOC) cash. This corruption renders Dr. Sinsky's arguments why physician burnout is at an all-time high mute moot. Turning a blind eye to the facts only deepens physician frustration with our current bureaucratic leadership.

If Dr. Sinsky is so concerned about physician burnout, why isn't she the leading spokesperson at the AMA insisting the leadership there end MOC as it was resolved by the AMA House of Delegates in 2016?

Perhaps it's because she's too conflicted to understand the problem.

-Wes

Tuesday, October 31, 2017

ABIM and the Human Diagnosis Project

Just when you thought it couldn't get worse, look what your ever-increasing American Board of Internal Medicine test fees are paying for now:
Fostering broader access to affordable, trustworthy, and meaningful artificial intelligence is a key goal for many in the industry, including an international group of stakeholders working on the Human Diagnosis (Human DX) Project.

Spearheaded by prominent organizations including the American Medical Association, American College of Physicians, and American Board of Internal Medicine, the initiative plans to bring quality specialty care, backed by artificial intelligence, to underserved patients around the globe.
... yet another unproven political agenda.

-Wes

Monday, October 30, 2017

ABIM Foundation - Five Years Later

A new public relations push for the ABIM Foundation and its Choosing Wisely campaign recently circulated in the press and MedPageToday. This quote from Richard Baron, MD, president of the American Board of Internal Medicine (ABIM) and the ABIM Foundation (which created and promoted the "Choosing Wisely" campaign) caught my eye:
"Here we are 5 years later; today, 80 [medical] societies have lent their intellectual capital to thinking about this," Baron said. "How do we judge success? We go back to the idea that this is about supporting people having difficult conversations ... [and] health systems around the country are using this as a structure to have these conversations."
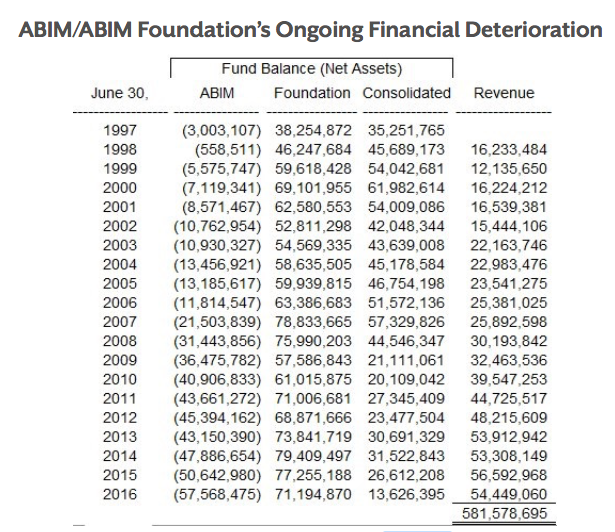
Health care organizations ARE using this as a structure to have these conversations. In fact, as has been systematically uncovered in this blog and elsewhere, the ABIM Foundation has spend the last five years spending our secretly funneled testing fees for themselves. Look at the data, pulled from IRS tax forms by Mr. Charles P. Kroll, to understand the magnitude of what has occurred:
While few can argue with the well-meaning effort to limit procedural overuse in medicine, but using physicians' testing fees to promote this program and to line its supporter's pockets without earning any program revenue could be one of the largest white-collar medical education Ponzi schemes (as Elizabeth Rosenthal, formerly from the New York Times, suggested) in the history of US medicine.

-Wes

Sunday, October 29, 2017

Kroll: How the War Against MOC® is Being Won

The war against Maintenance of Certification® (MOC®) is being won through social media and "memetic warfare." Spend 23 minutes to fully comprehend what's happening to the ABIM, the ABMS, and their member boards, including the American Board of Surgery, and the American Board of Pediatrics.

Forensic accountant, Mr. Charles P. Kroll, explains:


-Wes

Saturday, October 28, 2017

ABIM Tax Filings Show More Important Discrepancies

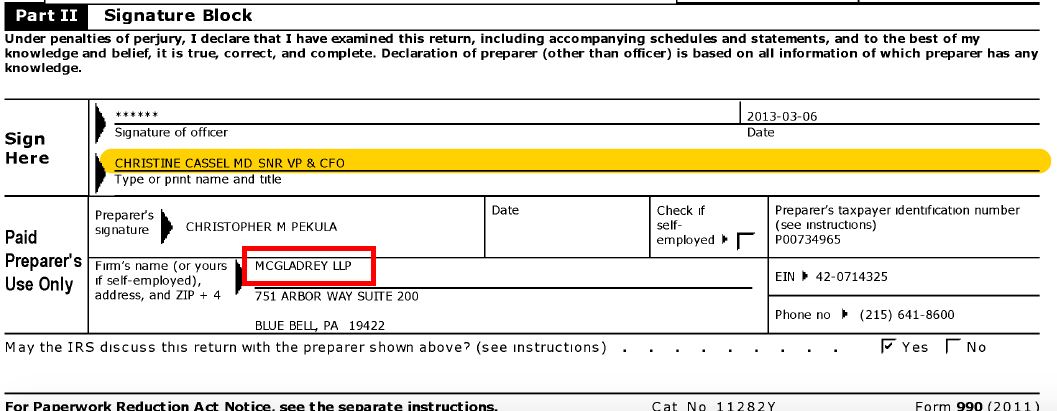
When was Christine Cassel, MD ever the Senior Vice President and Chief Financial Officer of the American Board of Internal Medicine?

ABIM 2011 Form 990, Page 1 - Signature Line

McGladrey LLC has a long history of accounting deficiencies, but this one might take the cake. ABIM's paid McGladrey LLC a whopping $361,753 for "accounting/consulting" services in fiscal year 2011. This amount is over three times the usual accounting fees ABIM historically paid. 

Why? 

Was there such significant cover-up that ABIM's true Chief Financial Officer at the time, Vincent Mandes, wouldn't sign the tax form?

-Wes

PS: Recall that the AMA House of Delegates requested a formal independent audit of the ABIM. The AMA asked Richard Baron, the President of CEO to respond to that request. An independent audit was never granted. Instead, Richard Baron, MD issued this statement.

Sunday, October 22, 2017

What ABIM and Theranos Have In Common

Mr. Chris Jennings
(photo from their company website)
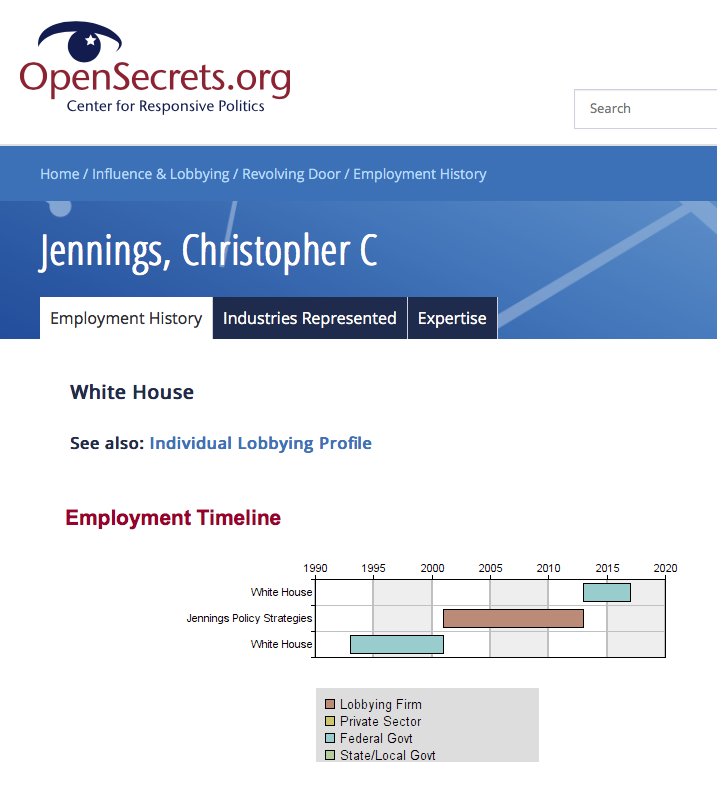
Meet Mr. Chris Jennings, a "consultant" to American Board of Internal Medicine (ABIM) in fiscal year 2010. Mr. Jennings has also served as an advisor to Theranos, the health care technology company recently labeled as a fraud.

Mr. Jennings is the founder and President of Jennings Policy Strategies, Inc., a company with whom, according to their 2010 Form 990, the ABIM "consulted" for a cool $120,000 for fiscal year 2010. (Here's documentation of a portion of that amount).

There's only one problem.

According to the Center for Responsive Politics, Jennings Policy Strategies, Inc was not really a "consultant," but rather a registered lobbying firm in Washington DC in 2010. Just as before, it appears the ABIM has failed to disclose lobbying activity with this firm on their 2010 Form 990 disclosures, choosing instead to label the activity as "consulting." Given this, it appears fraud may involve more than Theranos.

This begs the question: where's the IRS?

-Wes

References:
"Clinton Aide Joins Obama on Health Care," New York Times July 7, 2013.
"Clinton Campaign Advisor Also Advised Fast Faltering Health Care Company," Free Beacon 11/12/2015.
Health Care Affairs blog bio.
ABIM IRS Form 990 - 2010

Friday, October 20, 2017

What is MOC®? Why Is This Important?

What is Maintenance of Certification® (MOC®)?

Is it an educational program for physicians? If you think so, you are wrong.

MOC® has almost nothing to do with physician education, but according to the contract we must sign, involves "certain health care service operations, including practice assessment and evaluations." Most importantly, it allows physicians' personal and practice data to be shared with an unlimited number of third parties through a HIPAA Business Agreement.

Let me be clear. MOC® is not really about physician education. Instead, MOC® allows a physician's personal data to be shared with data registries and large corporations who profit from those data. For instance,  our MOC® and survey data are shared with (sold to?) Premier, Inc. (PINC, the $4.3 billion owners of CECity, Inc.), the largest healthcare performance improvement company that serves 3,900 hospitals and health systems and approximately 150,000 other providers and organizations." (Remember, Christine Cassel, MD, former President and CEO of the American Board of Internal Medicine, served on the board of Premier, Inc at one time and earned plenty of money and stocks in that capacity while at the ABIM.)

It also allows physician data to be sold to ABMS Solutions, LLC, a for-profit wholly-owned subsidiary of the American Board of Medical Specialties that is based in Atlanta, Georgia, who then sells your MOC® status, updated every 24-hours, to others, and a company never mentioned in disclosures published in our major medical journals. They will also plan to share these data with the Disciplinary Action Notification System database owned by the privately-held non-profit Federation of State Medical Boards that solicits "Affiliate Members, Official Observers, and Courtesy Members."

Again, MOC® is not about physician education. It is about collusion with multi-billion dollar companies, including Wolters Kluwer, and Pearson, LLC, and even our own politically-powerful American College of Cardiology that who owns the NCDR procedural registries and sells access to them to hospitals with MOC® as its demographics supplier (a full explanation of how this works is available here).

Why is the understanding of this "definition" of MOC® so important?

Multiple states are enacting legislation to prevent MOC® as a cudgel to limit a physician's ability to hold hospital credentials, be on insurance panels, or obtain state licensure. Our physician data are that important to these companies they will stop at nothing to be sure we sign that MOC® agreement.

What if the ABMS re-brands MOC® to some other "product" at their December 4th meeting with all of those state medical societies frustrated with what MOC® has become? Might the American Board of Medical Specialties and their collaborators skirt existing "anti-MOC®" legislation? Current anti-MOC® legislation must anticipate this and not include "MOC®" but "MOC® or any other health care serve operation that may include practice assessment or evaluations that requires a physician to sign a HIPAA Business Agreement to which they are not parties" in their language.

Physicians enacting anti-MOC® legislation need to understand the legal definition of MOC®. That way they can write legislation that is lasting, meaningful and enforceable, irrespective of how MOC® is ultimately re-branded.

MOC® is broken and must end. Not because it's a failed physician education experiment. It's broken because of its threats to physician civil liberties and threatens the doctor-patient relationship at it's most intimate level, thanks to the age old business motivators, money, power, and greed.

-Wes